Related Experiment Video
Updated: Jan 27, 2026


Implantation of Total Artificial Heart in Congenital Heart Disease
Published on: July 18, 2014
Evaluating the response to cardiac resynchronization therapy performed with a new ventricular morphology-based
Aya Miyazaki1,2, Jun Negishi3, Yosuke Hayama3
1Congenital Heart Disease Center, Tenri Hospital, 200 Mishima-cho, Tenri, Nara, 631-8552, Japan. ayamiya@pc4.so-net.ne.jp.

Insights
This study introduces a new cardiac resynchronization therapy (CRT) strategy for congenital heart disease (CHD) patients, improving outcomes in those with ventricular conduction delays and heart failure.
Area of Science:
- Cardiology
- Medical Devices
- Congenital Heart Disease
Background:
- Cardiac resynchronization therapy (CRT) in congenital heart disease (CHD) requires tailored pacing strategies based on ventricular morphology.
- Previous methods for systemic left ventricle (LV) pacing are not optimal for other ventricular morphologies.
Purpose of the Study:
- To evaluate the effectiveness of a novel ventricular morphology-based CRT strategy in CHD patients.
- To assess responder rates and identify reasons for non-response to CRT.
Main Methods:
- Retrospective analysis of 27 CRT procedures in 24 CHD patients.
- Implementation of a new CRT strategy based on ventricular morphology and dyssynchrony type (short-axis, long-axis, interventricular).
- Lead placement guided by specific criteria for different ventricular morphologies and dyssynchrony patterns.
Main Results:
- An overall responder rate of 63% (17/27) was observed.
- Excluding cases with no baseline ventricular conduction delay/heart failure or non-optimal lead placement, the responder rate increased to 88% (14/16).
- Identified reasons for non-response included non-optimal lead positions, absence of baseline conduction delay or heart failure symptoms, short follow-up, and extremely dilated systemic right ventricle (RV).
Conclusions:
- The proposed ventricular morphology-based CRT strategy shows promise for CHD patients with systemic ventricular conduction delay and heart failure.
- Optimized lead placement and patient selection (presence of conduction delay/heart failure) are crucial for successful CRT outcomes in CHD.
- This tailored approach can improve CRT effectiveness in complex congenital heart conditions.
Background:
In cardiac resynchronization therapy (CRT) for patients with congenital heart disease (CHD) and a ventricular morphology other than a systemic left ventricle (LV), we previously proposed pacing sites that are different from those used for a systemic LV. The leads should be placed laterally on opposite sides of both ventricles in patients with short-axis dyssynchrony and a single ventricular physiology with two ventricles, whereas they should be placed at the farthest sites along the longitudinal direction in the right ventricle (RV) in patients with long-axis dyssynchrony of the RV. Moreover, in patients with interventricular dyssynchrony and a biventricular physiology with a systemic RV, they should be placed at sites that both ventricles can contract simultaneously. We retrospectively investigated 27 consecutive procedures in 24 patients with CHD who underwent CRT to evaluate the effectiveness of a new ventricular morphology-based CRT strategy. The responder rate was 63% (17/27). The reasons for a non-response to CRT in 10 cases were as follows: non-optimal lead positions during CRT, 4; no systemic ventricular conduction delay or heart failure symptoms before the CRT, 5; short follow-up periods after the CRT, 2; and an extremely dilated systemic RV, 1. The responder rate became 88% (14/16), after excluding the procedures without a ventricular conduction delay or heart failure symptoms and those with non-optimal lead positions. This new strategy for CRT can provide favorable results for CHD patients with a systemic ventricular conduction delay and heart failure.
More Related Videos
 12:45
Benefits of Cardiac Resynchronization Therapy in an Asynchronous Heart Failure Model Induced by Left Bundle Branch Ablation and Rapid Pacing
Published on: December 11, 2017
 06:56
Author Spotlight: Enhancing Donor Heart Preservation Through Isolated Rat Heart Perfusion Studies
Published on: October 4, 2024
Related Concept Videos
 01:29
Pathophysiology of Cardiac Performance
 01:27
Anatomy of the Heart
 01:18
Physiology of the Heart: The Cardiac Cycle
Diastole: The Relaxation Phase
During diastole, all four heart chambers relax. The atrioventricular (AV) valves open, and the semilunar valves close. This phase sees the lowest chamber pressures, promoting ventricular filling. Venous blood enters the heart through the...
 01:22
Heart Failure VI: Adjunct Therapies
 01:19
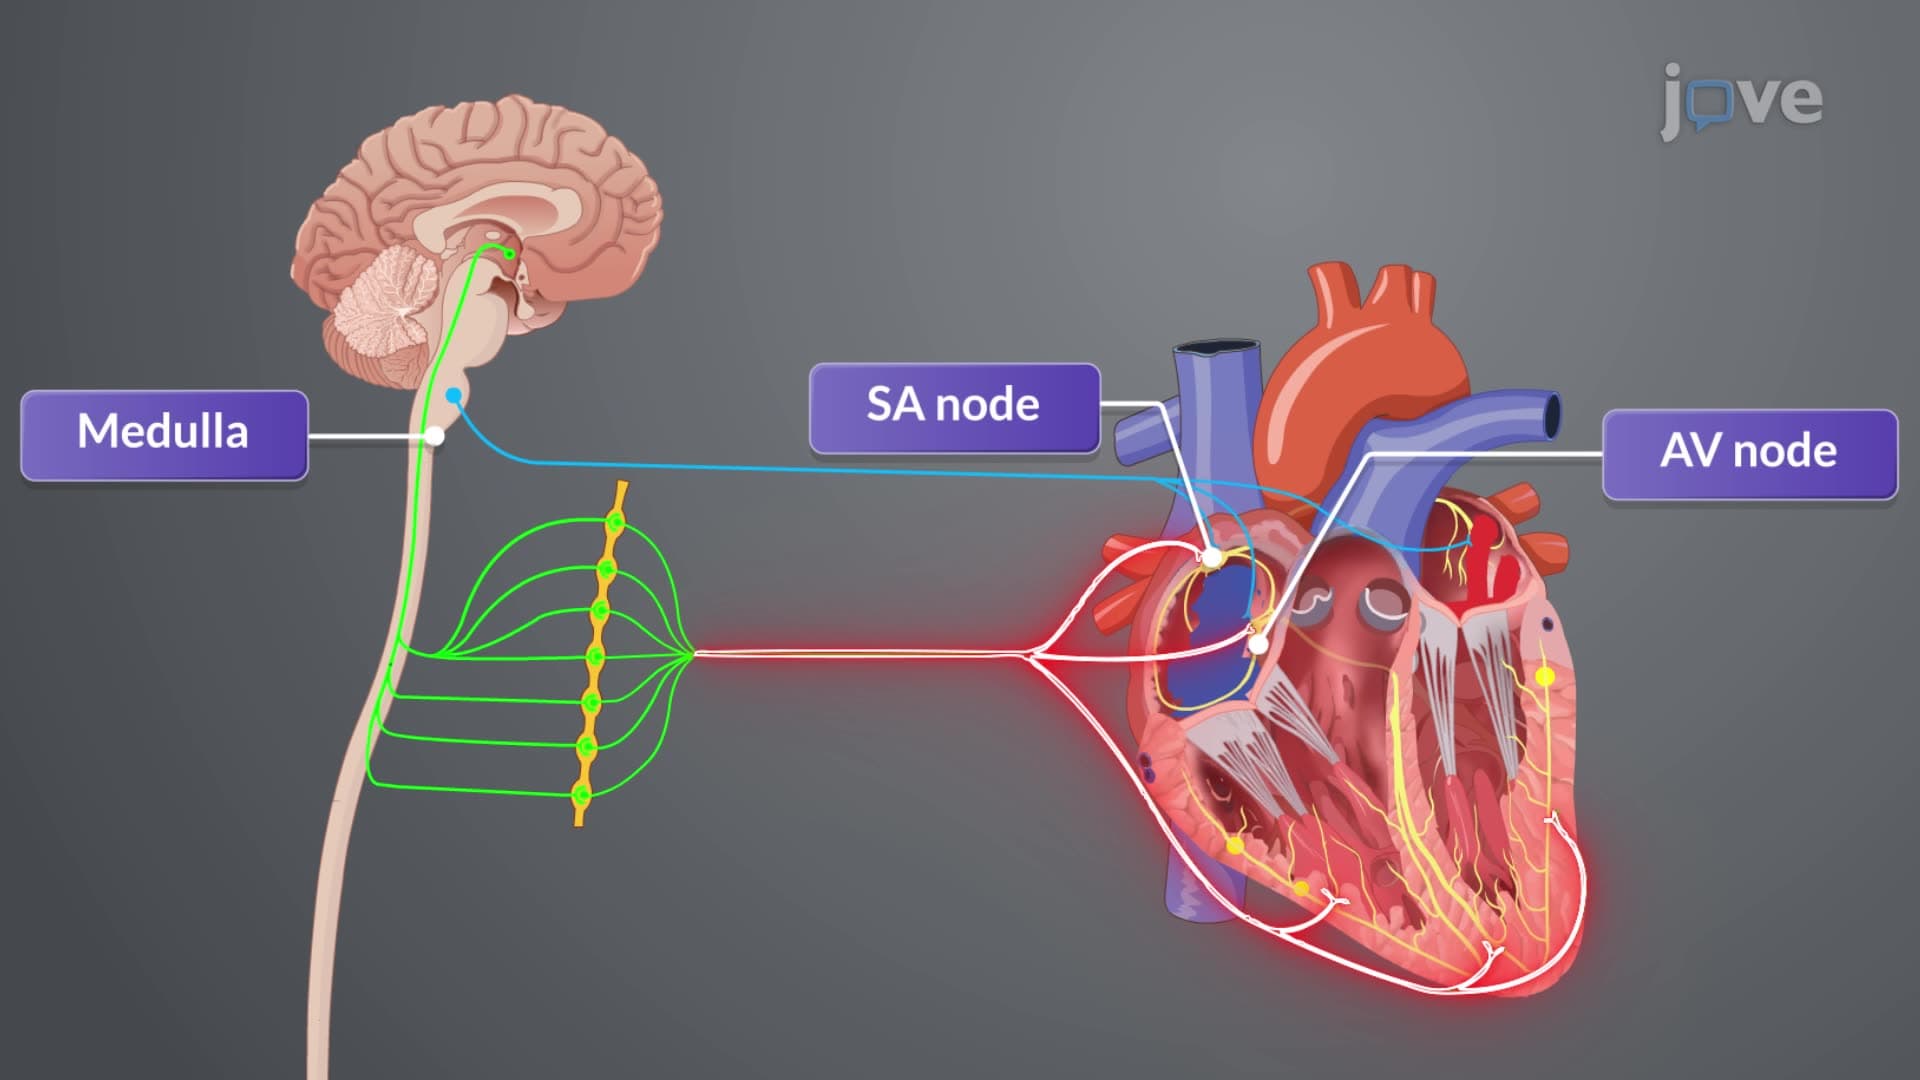
Cardiac Output I:Effect of Heart Rate on Cardiac Output
Cardiac output (CO) refers to the total amount of blood ejected by one of the ventricles in liters per minute (L/min). In a resting adult, CO ranges from 5 to 6 L/min, adjusting according to the body's metabolic requirements.
Effect of Heart Rate on Cardiac Output
Cardiac output adapts to metabolic demands during stress, physical activity, or illness. The autonomic nervous system regulates heart rate via the sinoatrial node. The parasympathetic nervous system decreases heart...
 01:21
Cardiac Catheterization II: Right Heart Catheterization