Related Experiment Video
Updated: Jan 27, 2026

A Teleoperated Robotic System-Assisted Percutaneous Transiliac-Transsacral Screw Fixation Technique
Published on: January 6, 2023
Computational simulation of sacral-alar-iliac (S2AI) screw fixation of pelvis and implications for fluoroscopic
Soon-Taek Jeong1, Young-Seop Park2, Gu-Hee Jung3
11 Department of Orthopaedic Surgery, College of Medicine, Gyeongsang National University, Gyeongsang National University Hospital, Jinju-si, Republic of Korea.

Purpose:
To determine an easy and convenient method of sacral-alar-iliac (S2AI) screw fixation and introduce the surgical landmarks for fluoroscopic procedure by analyzing 3-D models of pelvis and virtual implantation in a 3-D model.
Materials And Methods:
Eighty-two cadavers underwent computed tomography scans and the images imported into Mimics® software to make the 3-D pelvis model. The pedicle screw (Ø 8.5 mm/length 115 mm) was processed into a 3-D model using a 3-D-sensor (Comet5®) at the actual size and virtually placed as the S2AI screw. The ideal screw position was defined as the maximal intraosseous length without cortical perforation along the entire path. The ideal entry point and screw trajectory were verified and assessed to introduce the surgical landmark for fluoroscopic procedure.
Results:
There was no cortical violation around nerve root canal and greater sciatic notch through the entry point between first and second dorsal sacral foramen. There was no impossible model of S2AI screws. The average screw length was 99.8 mm (range, 59.8-115 mm; standard deviation, 16.1) and just one model had shorter than 65 mm S2AI screw. The factors limiting the intra-iliac screw length were sex ( p = 0.000) and the iliac groove around the sacroiliac joint ( p = 0.000). A free 360° rotation with magnification revealed that the screw trajectory was consistently directed toward the anteroinferior iliac spine (AIIS) in any plane.
Conclusion:
The ideal entry point of S2AI screw showed a wide range of tolerance between the first and second dorsal sacral foramen; and thus, there was no need for deep dissection to identify the first dorsal sacral foramen. Considering the tendency to shift the pilot hole laterally and the ideal screw trajectory was consistently directed toward AIIS, the entry point is better to be located with a medial shift.
More Related Videos
 12:25
C-arm-Free Simultaneous OLIF51 and Percutaneous Pedicle Screw Fixation in a Single Lateral Position
Published on: September 16, 2022
 08:11
Surgical Training for the Implantation of Neocortical Microelectrode Arrays Using a Formaldehyde-fixed Human Cadaver Model
Published on: November 19, 2017
Related Concept Videos
 01:16
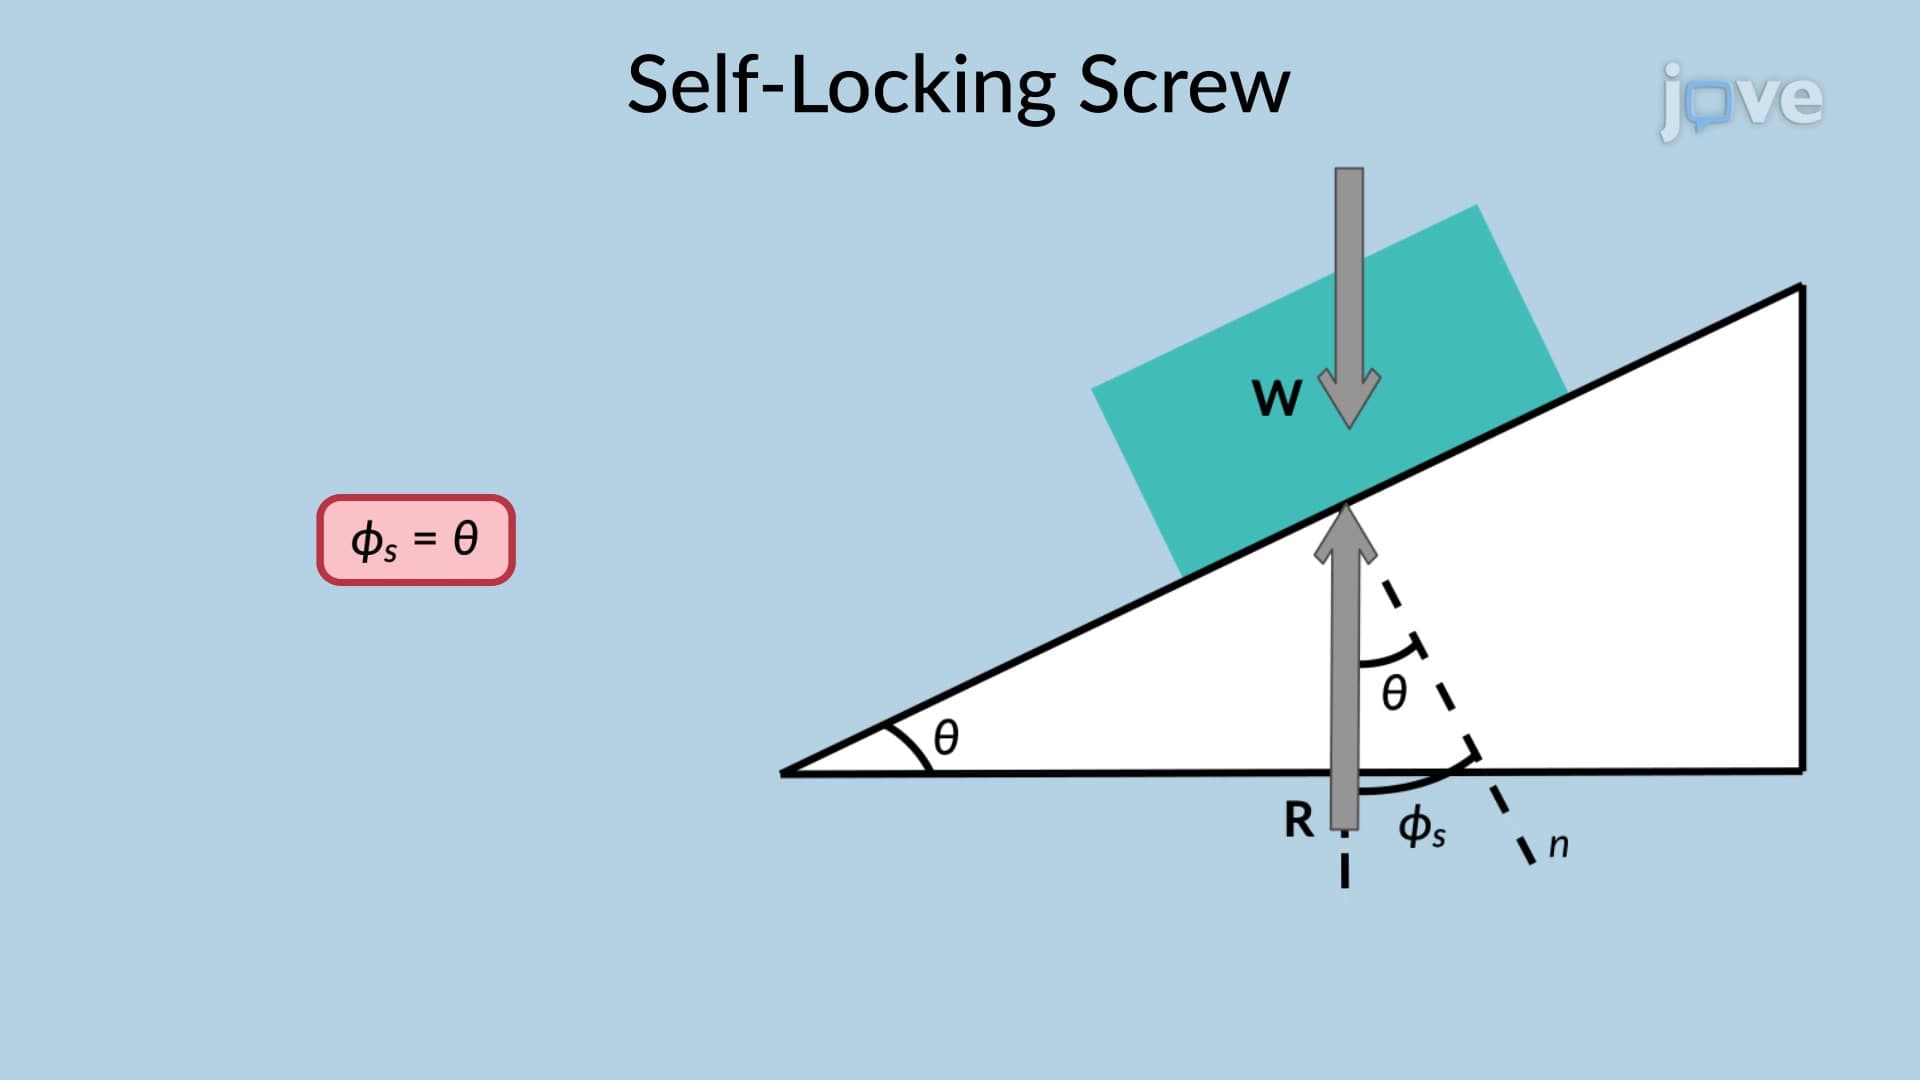
Self-Locking Screw
A square-threaded screw jack carrying a load is considered self-locking if the screw retains its position even after the moment applied to it is removed.
 01:18
Veins of the Abdomen and Pelvis
The inferior vena cava is fed by numerous smaller veins. The lumbar veins, for instance, drain the posterior abdominal wall, emptying both directly into the inferior vena cava and into the...
 01:21
Screw: Problem Solving
To evaluate the...
 01:27
Imaging Studies III: Computed Tomography
 01:17
Frictional Forces on Screws
A jack with a square-threaded screw is a mechanical device used to lift heavy loads by applying a force at its handle. When the force is applied, the screw turns, raising the load. The screw can...
 01:03
Fixation and Sectioning
The simplest type of preparation is the wet mount, in which the specimen is placed in a drop of liquid on the slide. A liquid specimen can be directly deposited on the slide using a dropper. Solid specimens, such as skin scraping, can be placed on the slide before adding a drop of liquid to prepare the wet mount. Sometimes the liquid is simply water, but stains are often added...