Related Experiment Video
Updated: Jan 26, 2026
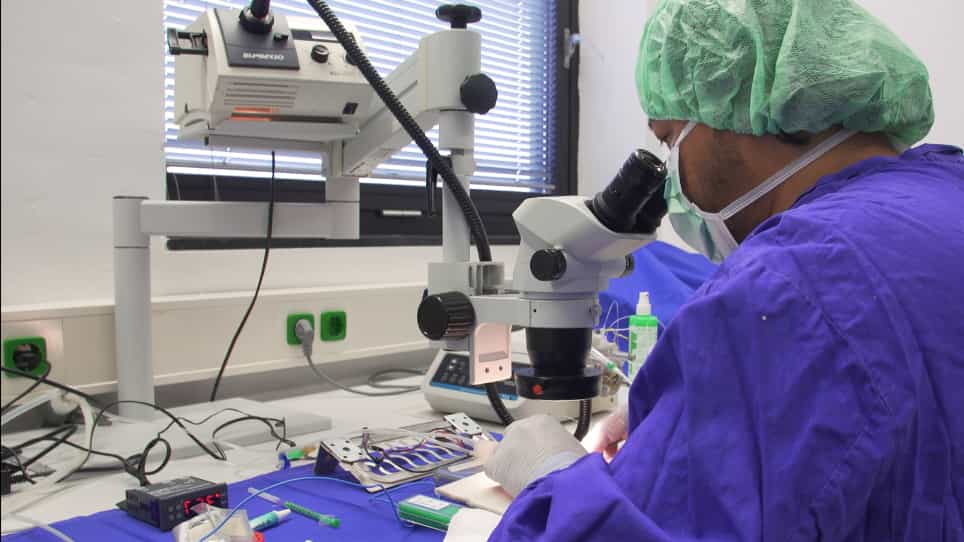

Veno-Venous Extracorporeal Membrane Oxygenation in a Mouse
Published on: October 24, 2018
Management of accidental hypothermia: an established extracorporeal membrane oxygenation centre experience
Martin Balik1, Michal Porizka1, Vojtech Matousek1
11 Department of Anaesthesiology and Intensive Care, 1st Faculty of Medicine, Charles University and General University Hospital, Prague, Czech Republic.

Introduction:
Data on management of severe accidental hypothermia published from an established high-volume extracorporeal membrane oxygenation centre are scarce.
Methods:
A total of 28 patients with intravesical temperature lower than 28°C on admission were either treated with veno-arterial extracorporeal membrane oxygenation or rewarmed conservatively.
Results:
A total of 10 patients rewarmed on veno-arterial extracorporeal membrane oxygenation (age: 37 ± 12.6 years) and 18 conservatively (age: 55.2 ± 11.2 years) were collected over a course of 5 years. The dominant cause was alcohol intoxication with exposure to cold (39%), 12 patients were resuscitated prior to admission. The admission temperature in the extracorporeal membrane oxygenation group (23.8 ± 2.6°C) was lower than in the non-extracorporeal membrane oxygenation group (26.0 ± 1.5°C, p = 0.01). The peripheral percutaneous veno-arterial extracorporeal membrane oxygenation was always cannulated in malignant arrhythmias causing refractory cardiac arrest. The typical extracorporeal membrane oxygenation blood flow was 3-4 L/minute and sweep gas flow 2 L/minute, the median extracorporeal membrane oxygenation duration was 48.3 (28.1-86.7) hours. The median rates of rewarming did not differ (0.41 (0.35-0.7)°C/hour in extracorporeal membrane oxygenation and 0.77 (0.54-0.98)°C/hour in non-extracorporeal membrane oxygenation, p = 0.46) as well as the admission arterial lactate, pH and potassium. Their development was not different between the groups except for higher pH between the third and ninth hour of rewarming in the extracorporeal membrane oxygenation group. The hospital mortality was 10% in the extracorporeal membrane oxygenation group and 11.1% in the non-extracorporeal membrane oxygenation group with the median last Glasgow Coma Scale 15 and Cerebral Performance Score 1.
Conclusion:
Veno-arterial extracorporeal membrane oxygenation for severe hypothermia shows promising outcome data collected in an extracorporeal membrane oxygenation/extracorporeal cardiopulmonary resuscitation centre located in a European urban area. Except for presence of refractory cardiac arrest, the established hypothermia-related prognostic indicators did not differ between patients in need for extracorporeal membrane oxygenation and those rewarmed without extracorporeal membrane oxygenation.

Related Concept Videos
 01:25
Extracorporeal Removal of Drugs: Hemoperfusion and Hemofiltration
 01:12
What is an Experiment?
 01:30
Extracorporeal Removal of Drugs: Peritoneal Dialysis and Hemodialysis
 01:16
Oxygen Delivering System II: Venturi Mask and Transtracheal Oxygen
Venturi Mask
The Venturi mask, named after the Venturi effect, is designed to deliver precise oxygen concentrations. It consists of a large tube with an oxygen inlet that narrows down, causing a pressure drop that pulls air in through adjustable side ports. The mask is a lightweight,...
 01:27
Oxygen Transport in the Blood
 01:26
Oxygenic Photosynthesis