Related Experiment Video
Updated: Jan 26, 2026

Cardiac Response to β-Adrenergic Stimulation Determined by Pressure-Volume Loop Analysis
Published on: May 19, 2021
Cardiomyocyte PKA Ablation Enhances Basal Contractility While Eliminates Cardiac β-Adrenergic Response Without
Ying Zhang1,2,3, Wei Eric Wang1,3, Xiaoying Zhang3
1Cardiology, Daping Hospital, Third Military Medical University, Chongqing (Y.Z., W.E.W., C. Zeng, L.Z.).

Rationale:
PKA (Protein Kinase A) is a major mediator of β-AR (β-adrenergic) regulation of cardiac function, but other mediators have also been suggested. Reduced PKA basal activity and activation are linked to cardiac diseases. However, how complete loss of PKA activity impacts on cardiac physiology and if it causes cardiac dysfunction have never been determined.
Objectives:
We set to determine how the heart adapts to the loss of cardiomyocyte PKA activity and if it elicits cardiac abnormalities.
Methods And Results:
(1) Cardiac PKA activity was almost completely inhibited by expressing a PKA inhibitor peptide in cardiomyocytes (cPKAi) in mice; (2) cPKAi reduced basal phosphorylation of 2 myofilament proteins (TnI [troponin I] and cardiac myosin binding protein C), and one longitudinal SR (sarcoplasmic reticulum) protein (PLB [phospholamban]) but not of the sarcolemmal proteins (Cav1.2 α1c and PLM [phospholemman]), dyadic protein RyR2, and nuclear protein CREB (cAMP response element binding protein) at their PKA phosphorylation sites; (3) cPKAi increased the expression of CaMKII (Ca2+/calmodulin-dependent kinase II), the Cav1.2 β subunits and current, but decreased CaMKII phosphorylation and CaMKII-mediated phosphorylation of PLB and RyR2; (4) These changes resulted in significantly enhanced myofilament Ca2+ sensitivity, prolonged contraction, slowed relaxation but increased myocyte Ca2+ transient and contraction amplitudes; (5) Isoproterenol-induced PKA and CaMKII activation and their phosphorylation of proteins were prevented by cPKAi; (6) cPKAi abolished the increases of heart rate, and cardiac and myocyte contractility by a β-AR agonist (isoproterenol), showing an important role of PKA and a minimal role of PKA-independent β-AR signaling in acute cardiac regulation; (7) cPKAi mice have partial exercise capability probably by enhancing vascular constriction and ventricular filling during β-AR stimulation; and (8) cPKAi mice did not show any cardiac functional or structural abnormalities during the 1-year study period.
Conclusions:
PKA activity suppression induces a unique Ca2+ handling phenotype, eliminates β-AR regulation of heart rates and cardiac contractility but does not cause cardiac abnormalities.


Related Concept Videos
 01:26
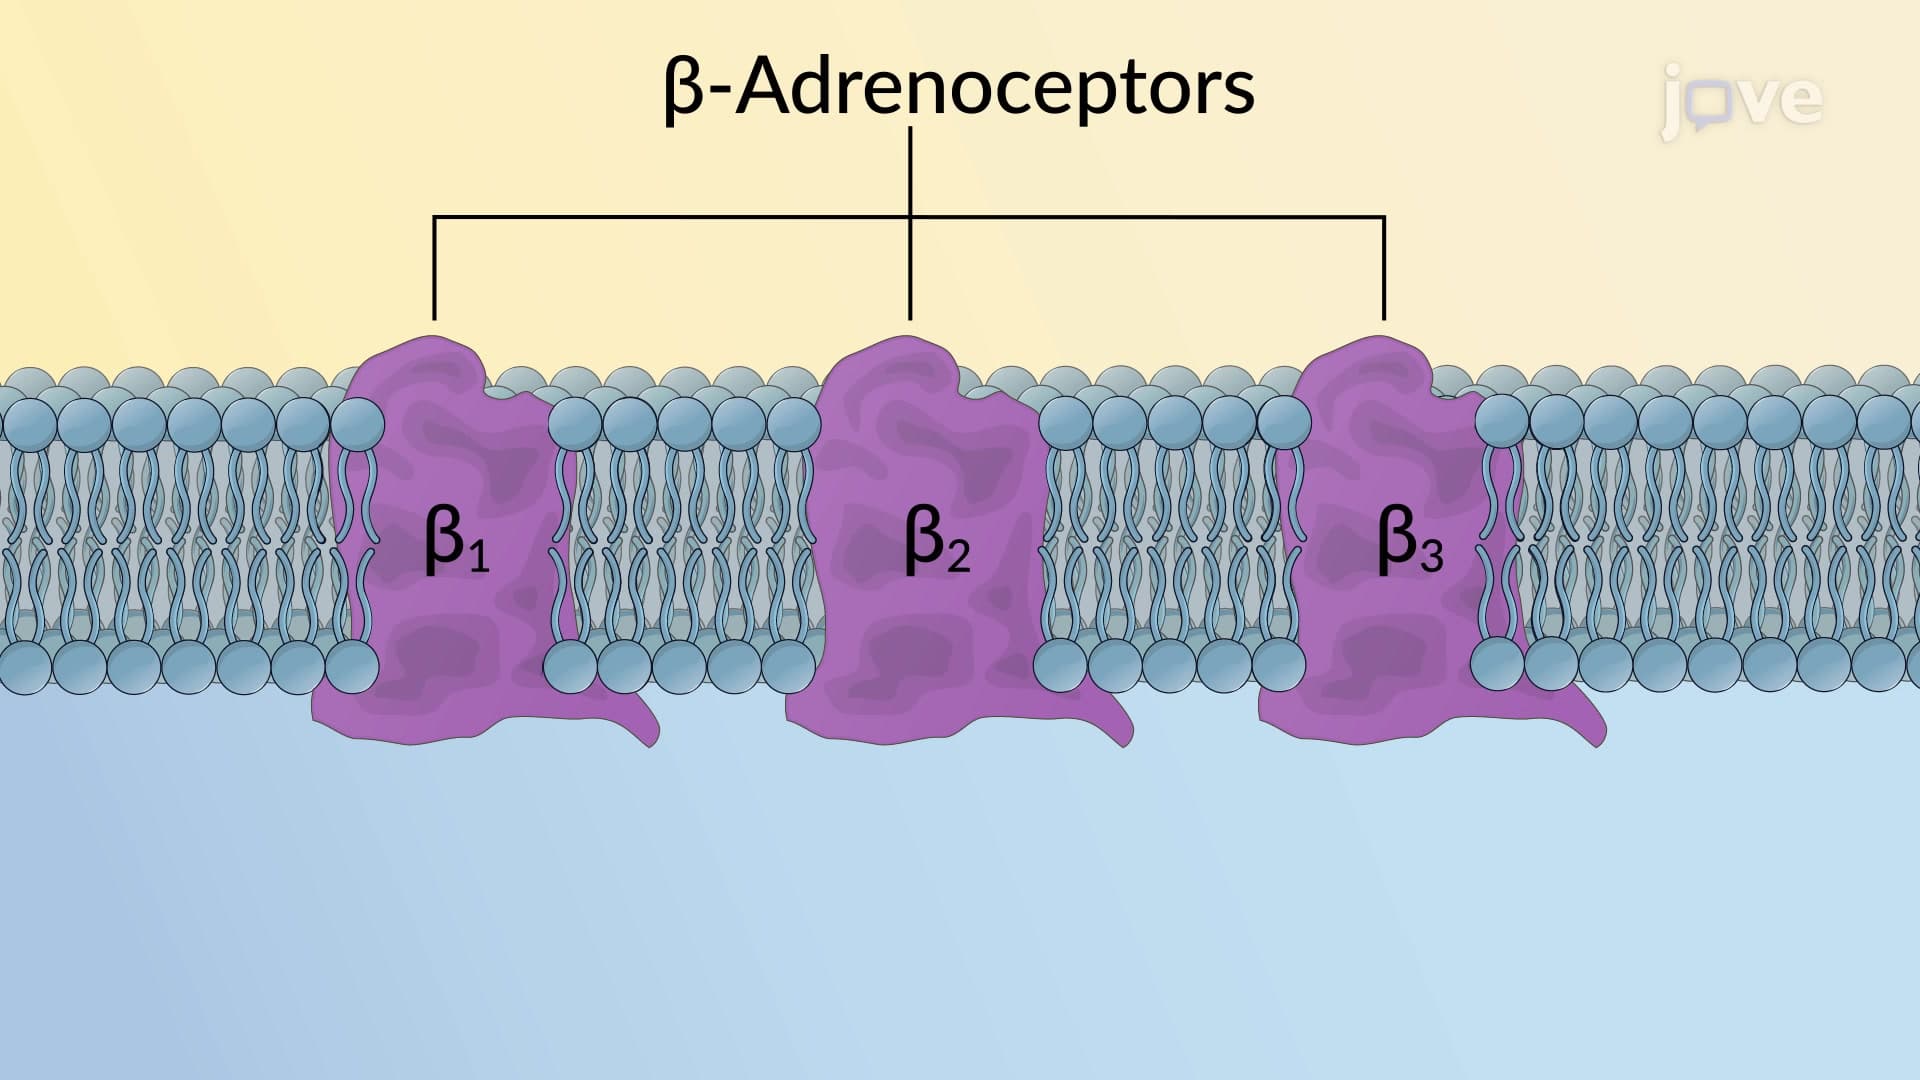
Adrenergic Receptors: β Subtype
Isoprenaline > Adrenaline > Noradrenaline
Neurotransmitter binding to these receptors causes activation of adenylyl cyclase resulting in increased concentrations of cAMP and modulation of calcium ion channels within the cell. They are further classified into β1, β2, and β3 subtypes.
β1-adrenoceptors: β1-adrenoceptors...
 01:26
Enhanced Elimination of Poison
Antidotes serve a crucial role in counteracting the effects of poison by inhibiting enzymes responsible for producing harmful drug metabolites. In some cases, these toxic metabolites can be neutralized by endogenous cosubstrates, which are maintained at specific concentrations to prevent interaction with cellular macromolecules and subsequent cell death.
Renal excretion is the...
 01:12
Local Anesthetics: Adverse Effects
Once absorbed into the systemic circulation, local anesthetics can affect the organs that depend on the functioning of sodium...
 01:31
Adrenergic Antagonists: ɑ and β-Receptor Blockers
 01:21
Skeletal Muscle Relaxants: Adverse Effects
Unlike...
 01:16
Insulin: Dosing Regimen and Adverse Effects
The basal dose constitutes about 40%-50% of the total daily dose, with the rest as premeal insulin. The mealtime insulin dose should mirror...