Related Experiment Video
Updated: Jan 26, 2026

Oral Health Assessment by Lay Personnel for Older Adults
Published on: February 2, 2020
Standardising practice in cardiology: reducing clinical variation and cost at Ochsner Health System
Phil Oravetz1, Christopher J White1, David Carmouche1
1Ochsner Health System, New Orleans, Louisiana, USA.

Insights
Utilizing simulated patient cases to provide cardiology feedback significantly improved care quality and reduced costs. This approach lowered practice variation and saved $4.34 million annually without impacting patient outcomes.
Area of Science:
- Cardiology
- Health Economics
- Medical Education
Background:
- Unwarranted clinical variation leads to poor patient outcomes and increased healthcare expenses.
- Developing effective strategies to enhance clinical quality and economic value in cardiology has been challenging.
- Ochsner Health System aimed to improve cardiology care quality and reduce costs through active measurement and tailored feedback.
Purpose of the Study:
- To assess the impact of serial measurement and individualized feedback using simulated cardiology cases on clinical practice.
- To evaluate changes in quality of care, practice variation, patient outcomes, and costs within a cardiology department.
Main Methods:
- Fifty cardiologists participated in six rounds of assessments over 16 months, managing simulated patients with conditions like heart failure, coronary artery disease, and supraventricular tachyarrhythmia.
- Online simulated cases were used to capture clinical decision-making, providing individualized feedback to participants.
- Real-world pre-post analyses of physician practice changes, patient outcomes, and costs were conducted using Ochsner's patient-level data.
Main Results:
- Simulated quality-of-care scores improved by 14.1% (p<0.001) from baseline to the final round.
- Cost-of-care variation decreased, with significant reductions in per-patient direct costs for supraventricular tachyarrhythmia ($493) and heart failure ($305).
- Readmission rates significantly decreased for heart failure (20.0% to 11.9%) and supraventricular tachyarrhythmia (14.5% to 7.8%), contributing to an estimated annual savings of $4.34 million.
Conclusions:
- Serial measurement and individualized feedback via simulated patients effectively enhance clinical quality in cardiology.
- This intervention demonstrably reduces practice variation and healthcare costs without adversely affecting patient outcomes.
- The findings support the use of simulated patient scenarios as a valuable tool for continuous quality improvement in medical practice.
Objective:
Low quality and unwarranted clinical variation harm patients and increase unnecessary costs. Effective approaches to improve clinical and economic value have been difficult. The Ochsner Health System looked to improve clinical care quality and reduce unnecessary costs in cardiology using active measurement and customised feedback.
Methods:
We serially measured care decisions using online, simulated cases to capture clinical details of cardiology practice and provide individual feedback. Fifty cardiologists cared for two simulated patients in each of six assessment rounds occurring 4 months apart. Simulated patients presented with heart failure (HF), coronary artery disease (CAD), supraventricular tachyarrhythmia (SVT) or valvular heart disease. Using Ochsner's patient-level data, we performed real-world pre-post analyses of physician practice changes, patient outcomes and costs.
Results:
Between baseline and final rounds, overall simulated quality-of-care scores improved 14.1% (p<0.001). In the same period, we found cost-of-care variation decreased in patient-level data, with larger decreases for more severely ill patients. The total per-patient direct costs decreased $493 in SVT, $305 in HF and $55 in CAD (p<0.05 for SVT and HF). Readmission rates fell significantly for HF (from 20.0% to 11.9%) and SVT (from 14.5% to 7.8%) (both p<0.001) and non-significantly for CAD (from 13.7% to 11.3%, p=0.112). The cost avoidance/revenue generation opportunity from reduced readmissions and direct costs amounted to annual savings of $4.34 million, with no significant changes to in-hospital mortality rates (p>0.05).
Conclusions:
Using simulated patients to serially measure and provide individual feedback on clinical practice significantly raises quality and reduces practice variation and costs without negatively impacting outcomes.
More Related Videos
 11:50
Clinical Practice Protocol of Creative Music Therapy for Preterm Infants and Their Parents in the Neonatal Intensive Care Unit
Published on: January 7, 2020
 10:28
Interventional Diagnostic Procedure: A Practical Guide for the Assessment of Coronary Vascular Function
Published on: March 15, 2022
Related Concept Videos
 01:14
What is Variation?
The range, standard deviation, standard error, and variance are the different measures of variation.
Range: The range is the difference between its maximum and...
 01:19
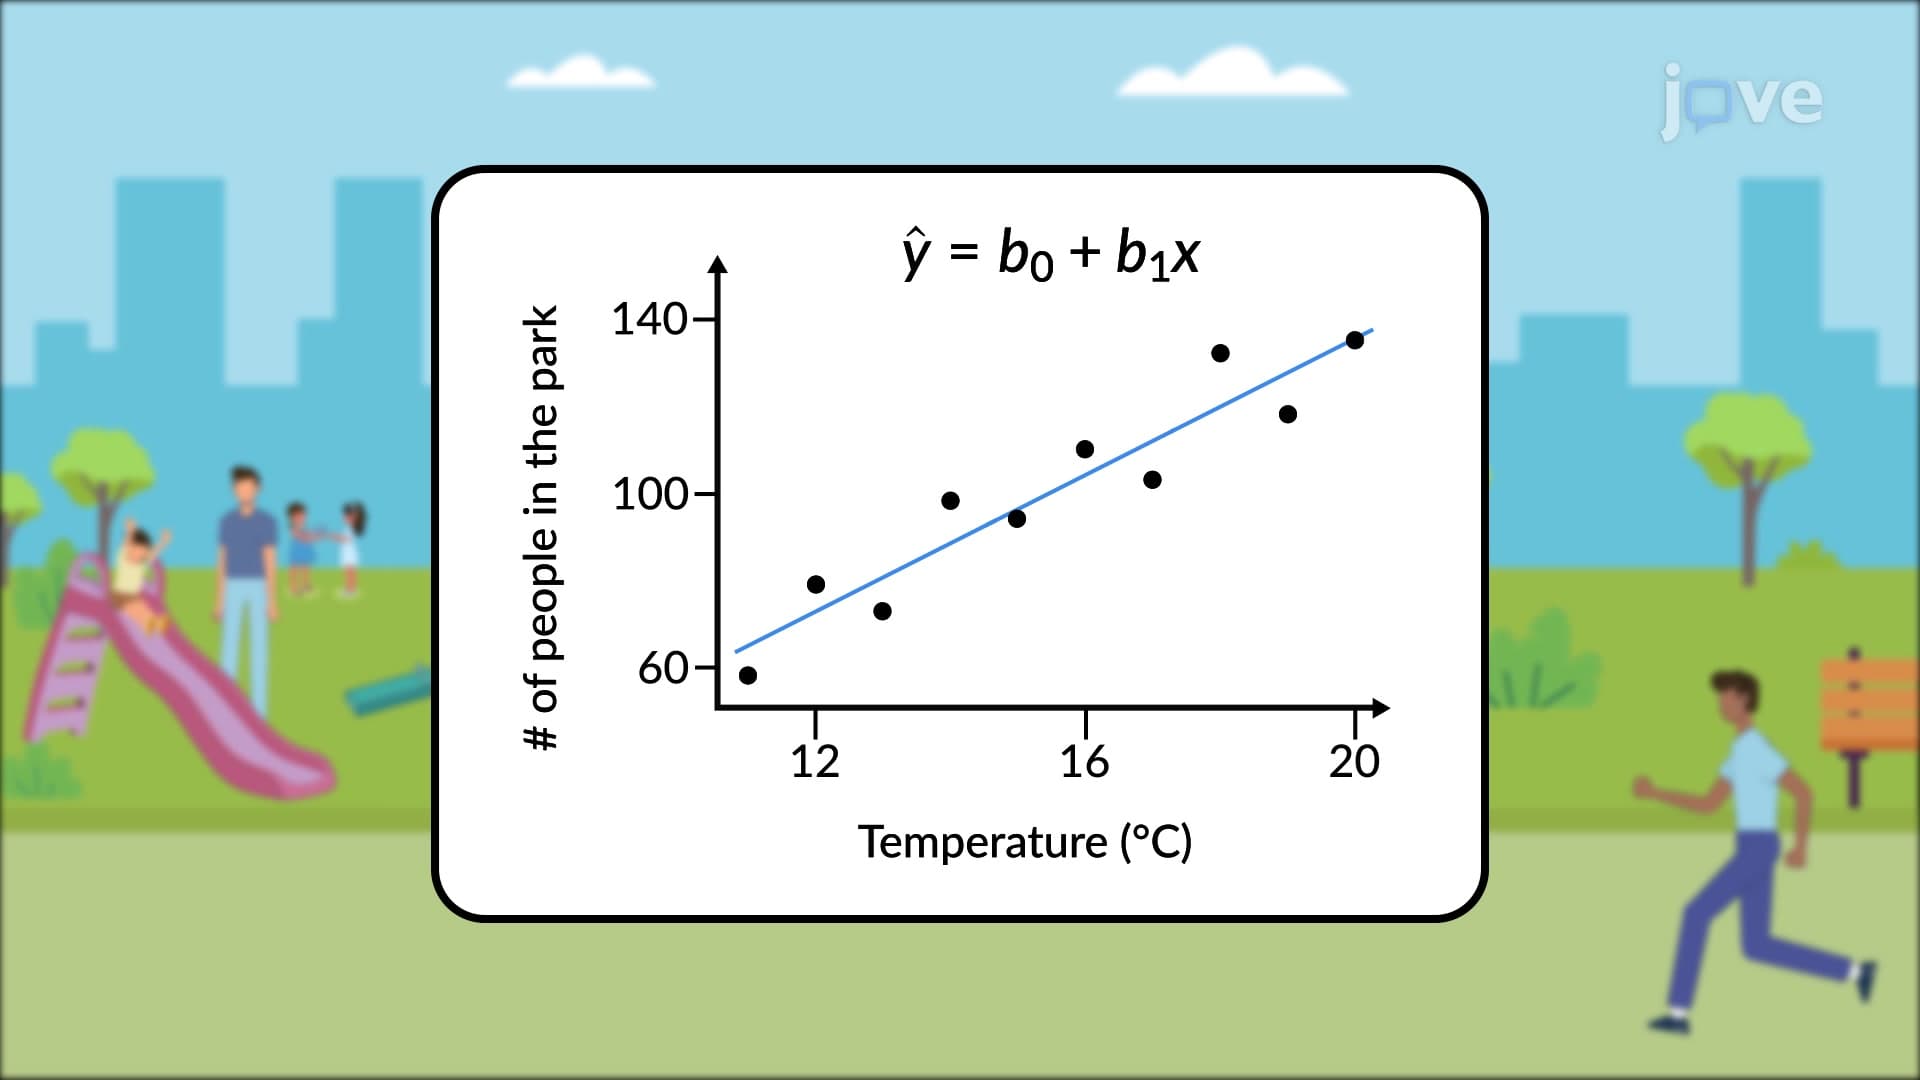
Variation
When independent and dependent variables are plotted on a scatter plot, the slope of a line is a value that describes the rate of change between the two...
 02:53
Conservative Site-specific Recombination and Phase Variation
The recognition sites for Cre recombinase called LoxP...
 01:18
Variation of Atmospheric Pressure
Assuming the air temperature is constant at a given altitude and that the ideal gas law of thermodynamics describes the atmosphere to a good approximation, one can find the variation of atmospheric pressure with height.
Let p(y) be the atmospheric pressure at...
 02:26
Comparing Copy Number Variations and SNPs
Copy number variations or CNVs are the structural variations that cover more than 1kb of DNA sequence. The single nucleotide polymorphism (SNP), on the other hand, is a single nucleotide change or a point mutation that is found in more than 1%...
 01:10
Coefficient of Variation
The coefficient of variation is a practical statistical tool in finance. It allows investors to assess the volatility or...