Related Experiment Video
Updated: Jan 25, 2026


Design and Construction of an Urban Runoff Research Facility
Published on: August 8, 2014
Quantifying geographic barriers to trauma care: Urban-rural variation in prehospital mortality
Molly P Jarman1, Zain Hashmi, Yasmin Zerhouni
1From the Center for Surgery and Public Health, Department of Surgery (M.P.J., Z.H., Y.Z., R.U., A.S., A.H.H.), Department of Surgery (Z.H.), Sinai Hospital, Baltimore, Maryland; Brigham and Women's Hospital, Harvard Medical School, Boston, Massachusetts; Department of Surgery (Y.Z.), University of California San Francisco East-Bay, Oakland, California; and Department of Emergency Medicine (C.N.), Oregon Health Sciences University, Portland, Oregon; Division of Trauma, Burn, and Surgical Critical Care, Department of Surgery (A.S.), Brigham and Women's Hospital, Boston, Massachusetts.

Background:
Few studies of trauma care access and quality account for prehospital injury mortality. Little is known about geographic variation in prehospital mortality or the impact of prehospital care on injury disparities.
Methods:
Using the Centers for Disease Control Wide-ranging Online Data for Epidemiologic Research database, we queried county-level incidence of prehospital injury mortality from 1999 to 2016. We linked mortality incidence with county-level urban-rural classifications from the National Center for Health Statistics and population data from the US Census Bureau. We used negative binomial regression to estimate the relationship between rurality and prehospital injury mortality, adjusting for county-level distribution of race, sex, age, income, and insurance coverage. Models were then stratified by injury mechanism (motor vehicle traffic [MVT] vs. penetrating) to determine if prehospital mortality rates varied by type of injury.
Results:
Prehospital injury mortality rates were elevated for all urban-rural county classes, relative to large central metro counties, with incidence rate ratios (IRR) ranging from 1.25 (95% confidence interval [CI], 1.16-1.35) for fringe metro counties to 1.69 (95% CI, 1.58-1.82) for noncore counties. For MVT injury, IRRs for urban-rural classes compared with large central metro counties ranged from 2.02 (95% CI, 1.85-2.21) for fringe metro counties to 3.02 (95% CI, 2.76-3.30) to noncore counties. Incidence of prehospital mortality from penetrating injury was 14% higher for noncore counties compared to large central metro counties (IRR, 1.14; 95% CI, 1.05-1.23).
Conclusion:
There is substantial geographic variation in prehospital injury mortality in the United States, with risk of prehospital death increasing with rurality. Patterns of prehospital death associated with penetrating and MVT injuries suggest that improvements to both trauma center access, prehospital care, and primary injury prevention are essential to reduce preventable injury deaths.
Level Of Evidence:
Retrospective ecological analysis, level III.

Related Concept Videos
 01:14
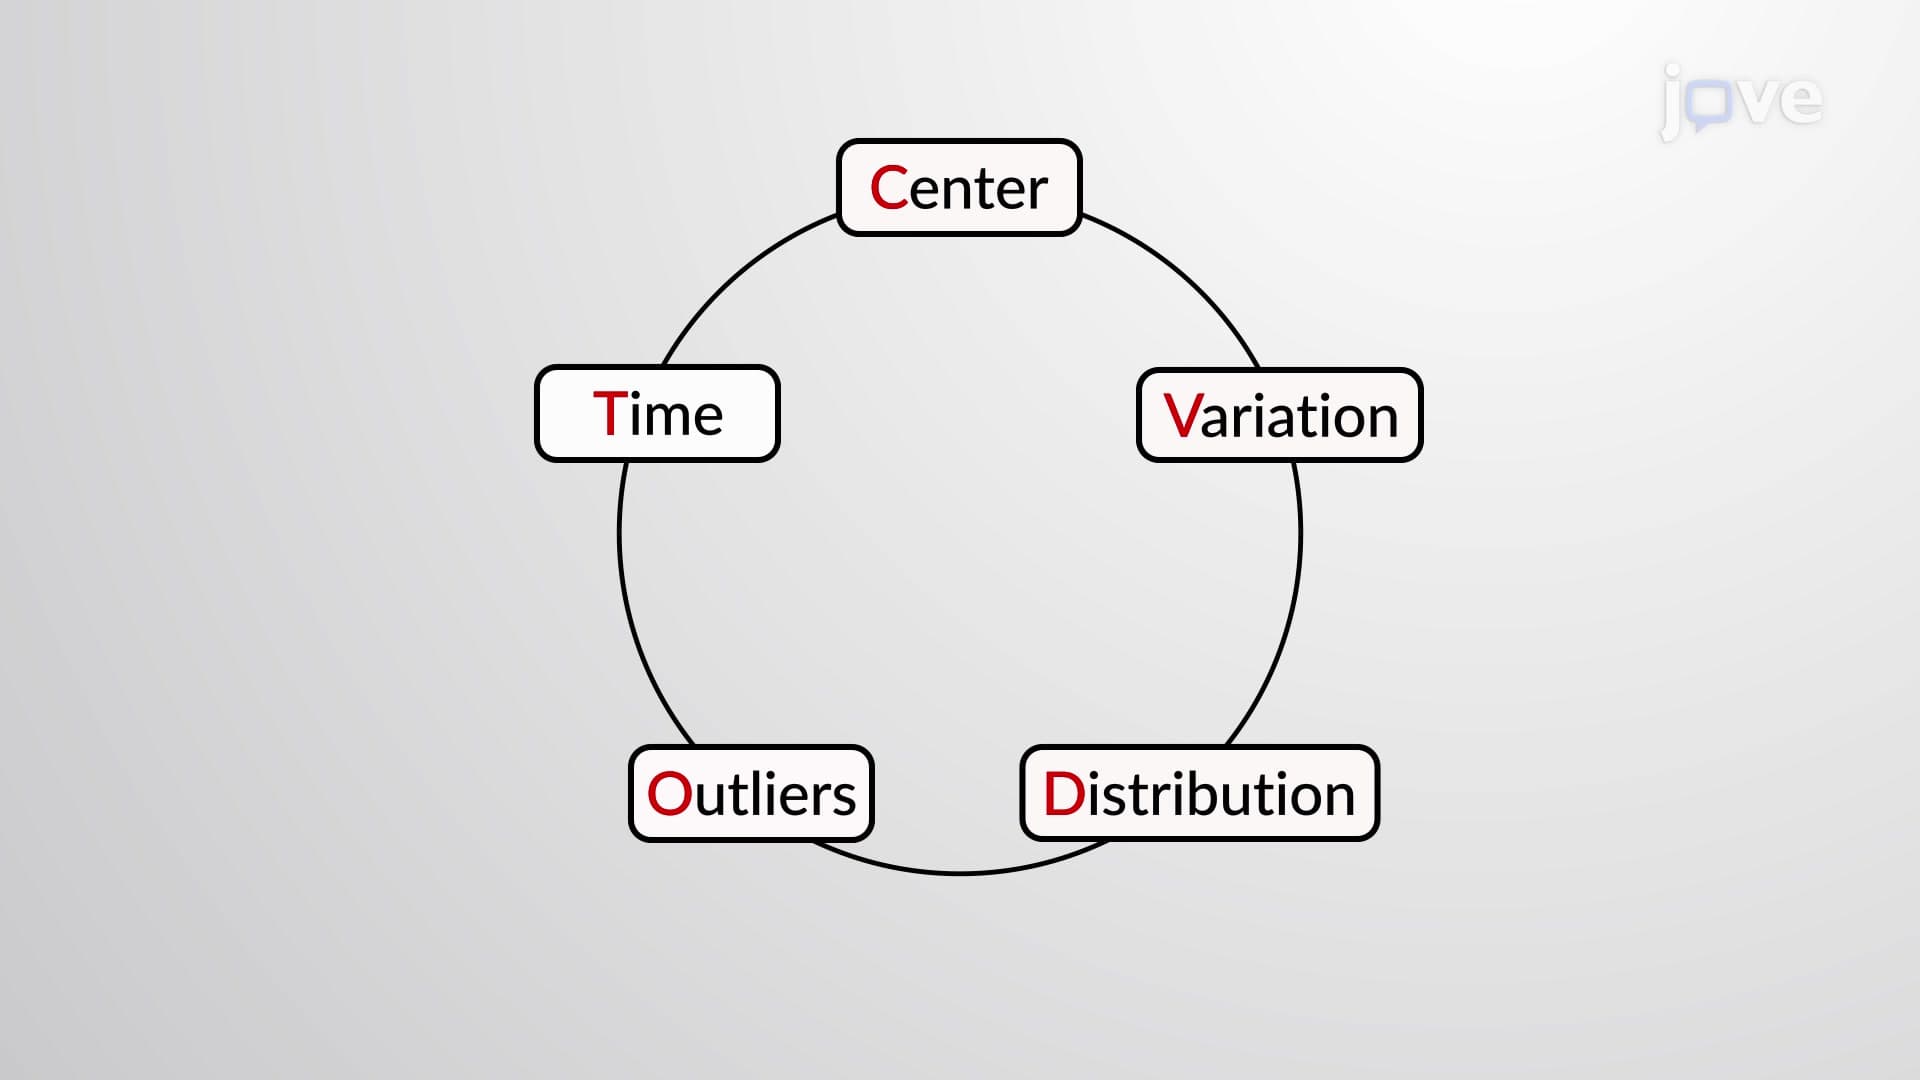
What is Variation?
The range, standard deviation, standard error, and variance are the different measures of variation.
Range: The range is the difference between its maximum and...
 01:25
Selected Data About Geographic Locations
 01:19
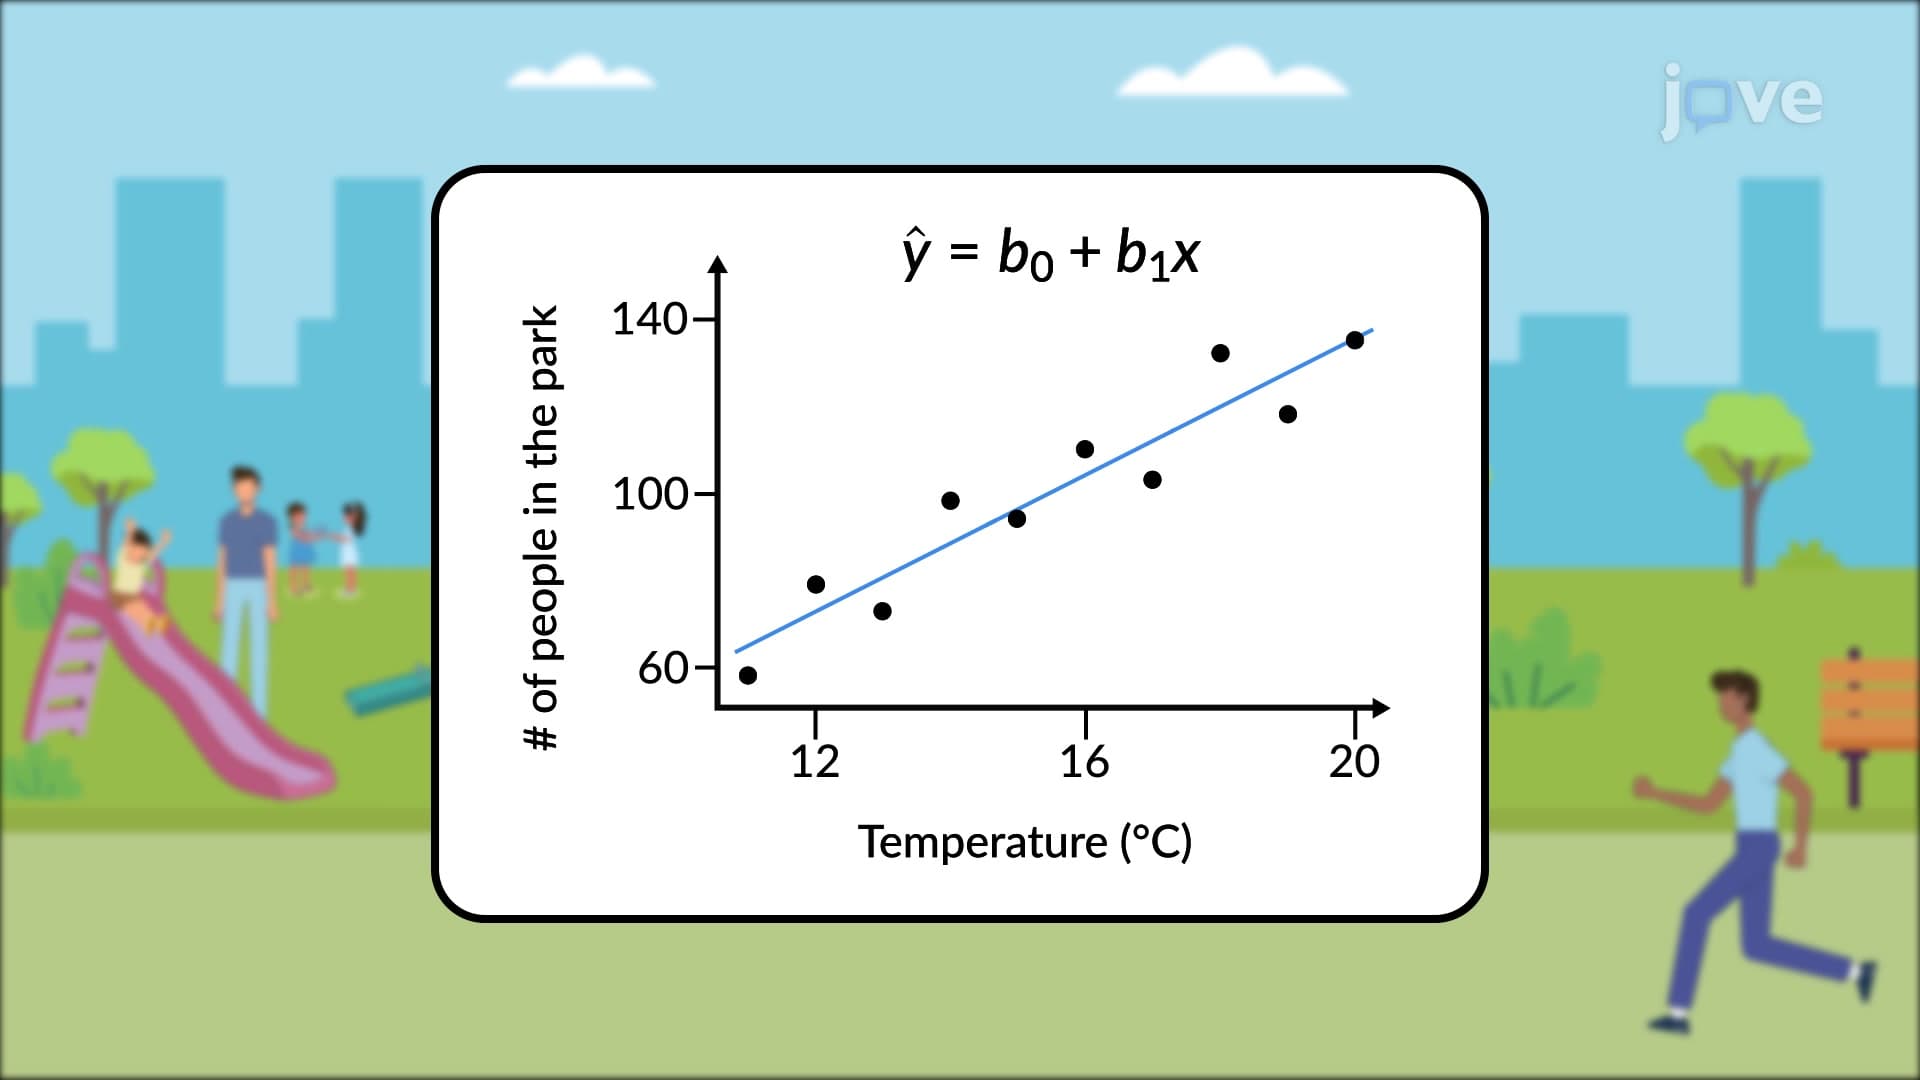
Variation
When independent and dependent variables are plotted on a scatter plot, the slope of a line is a value that describes the rate of change between the two...
 02:53
Conservative Site-specific Recombination and Phase Variation
The recognition sites for Cre recombinase called LoxP...
 01:18
Variation of Atmospheric Pressure
Assuming the air temperature is constant at a given altitude and that the ideal gas law of thermodynamics describes the atmosphere to a good approximation, one can find the variation of atmospheric pressure with height.
Let p(y) be the atmospheric pressure at...
 02:26
Comparing Copy Number Variations and SNPs
Copy number variations or CNVs are the structural variations that cover more than 1kb of DNA sequence. The single nucleotide polymorphism (SNP), on the other hand, is a single nucleotide change or a point mutation that is found in more than 1%...