Crowned dens syndrome: a neurologist's perspective

Lauranne Scheldeman1,2,3, Marijke Van Hoydonck4, Ruben Vanheste5

  • 1Department of Neurosciences, Experimental Neurology, University of Leuven, Leuven, Belgium. Lauranne.scheldeman@uzleuven.be.

Related Concept Videos

Aneurysm II: Clinical Manifestations and Diagnostic Studies01:21

Aneurysm II: Clinical Manifestations and Diagnostic Studies

Thoracic, aortic arch and abdominal aneurysms are significant vascular conditions that can present with various clinical manifestations and lead to serious complications. Understanding these manifestations and the appropriate diagnostic studies is essential for effective management and treatment.Thoracic Aortic AneurysmsThoracic aortic aneurysms often remain asymptomatic until they reach a size that impinges on adjacent structures. They typically cause deep, diffuse chest pain that radiates to...
Cushing Syndrome I: Introduction01:26

Cushing Syndrome I: Introduction

Cushing syndrome refers to the collection of clinical manifestations that arise when tissues are exposed to excessive amounts of cortisol or cortisol-like medications over an extended period. Cortisol, a glucocorticoid produced by the adrenal cortex, regulates metabolism, immune responses, and the body’s adaptation to stress. When its concentration remains chronically elevated, these physiological pathways become dysregulated, resulting in the characteristic features of the syndrome.Exogenous...
Cushing Syndrome II: Pathophysiology01:19

Cushing Syndrome II: Pathophysiology

Cortisol production is normally governed by the hypothalamic–pituitary–adrenal (HPA) axis, which maintains hormonal balance through tightly regulated feedback mechanisms. Disruption of this regulatory system is central to the development of Cushing syndrome, whether the excess cortisol originates from external medications or internal pathology. Persistent cortisol elevation alters metabolism, immune function, and endocrine signaling, producing the characteristic clinical features of the...
Increased Intracranial Pressure ll: Pathophysiology01:29

Increased Intracranial Pressure ll: Pathophysiology

Increased intracranial pressure (ICP) refers to a potentially life-threatening rise in pressure inside the skull. This usually happens when there is a major change in the volume of brain tissue, blood, or cerebrospinal fluid (CSF) — the three components inside the skull. According to the Monro-Kellie doctrine, if the volume of one component increases, the volumes of the other components must decrease to maintain normal pressure. If this does not happen, ICP rises.The process often begins with...
Cerebral Edema ll: Pathophysiology01:22

Cerebral Edema ll: Pathophysiology
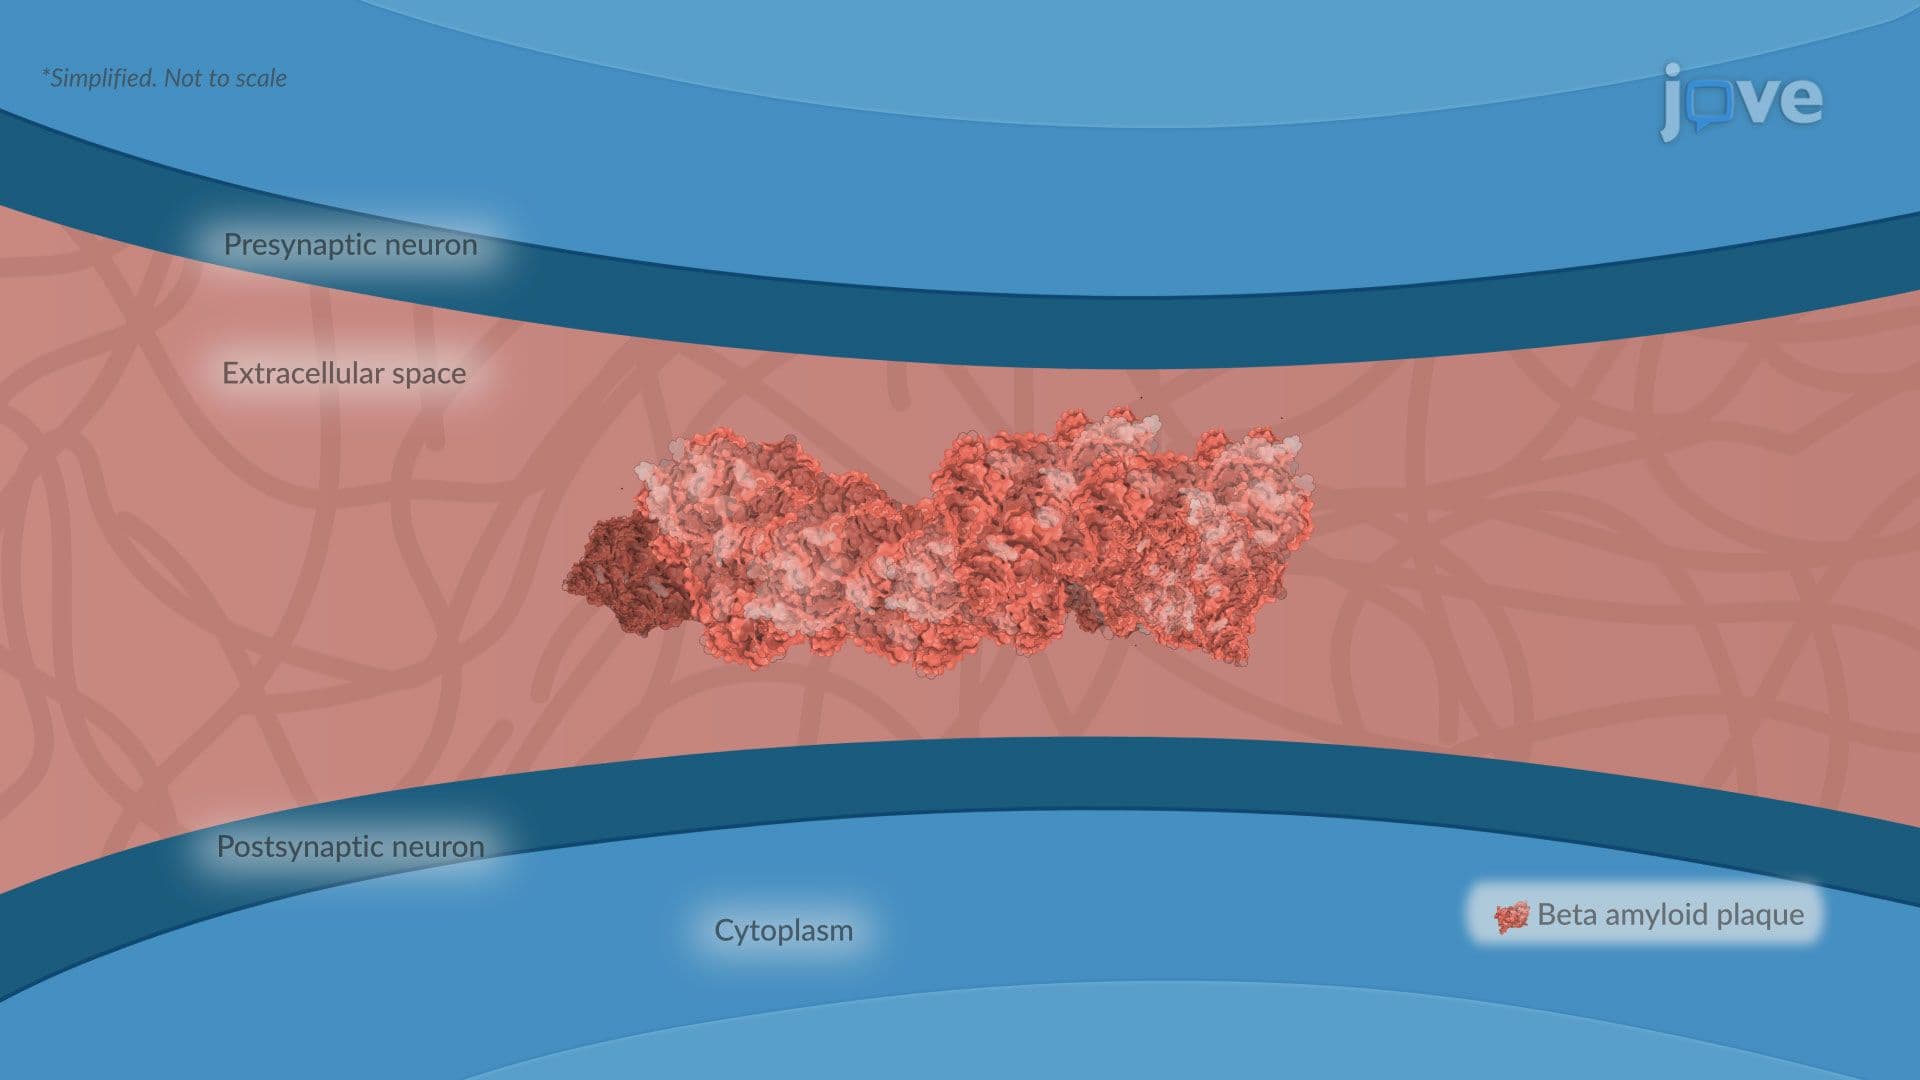
Vasogenic edema is a major form of cerebral edema characterized by abnormal accumulation of fluid in the brain’s extracellular space due to disruption of the blood–brain barrier (BBB). The BBB is a specialized structure composed of endothelial cells connected by tight junctions, supported by astrocytic endfeet and a basement membrane. Under normal conditions, it tightly regulates the movement of ions, proteins, and solutes between the bloodstream and brain parenchyma. When this barrier loses...
Dementia l: Introduction01:22

Dementia l: Introduction

Dementia is an acquired, progressive syndrome characterized by a decline in multiple cognitive domains severe enough to impair daily functioning and reduce independence. Although memory loss is a central feature, the diagnosis requires additional deficits involving language, executive function, visuospatial skills, judgment, calculation, or abstract reasoning. These cognitive impairments reflect underlying neurodegenerative or vascular processes that gradually disrupt neuronal networks...