Related Experiment Video
Updated: Jan 24, 2026


Modeling Brain Metastasis Via Tail-Vein Injection of Inflammatory Breast Cancer Cells
Published on: February 4, 2021
Excellent Locoregional Control in Inflammatory Breast Cancer With a Personalized Radiation Therapy Approach
Shane R Stecklein1, Kelly J Rosso2, Jenny Nuanjing1
1Department of Radiation Oncology, The University of Texas MD Anderson Cancer Center, Houston, Texas.

Purpose:
Inflammatory breast cancer (IBC) has been characterized by high locoregional recurrence (LRR) rates even after trimodality therapy. We recently reported excellent locoregional control among patients treated since formal dedication of an IBC-specific clinic and research program in 2006. Institutionally, a standard twice-daily (BID) dose escalation regimen for all patients with IBC was de-escalated in select cases in 2006 after review demonstrated that young age, incomplete response to neoadjuvant therapy, and positive margins identified subsets with maximal benefit from dose escalation. We report local control and toxicity rates specific to BID versus once-daily (QD) radiation therapy approaches.
Methods And Materials:
From a prospectively collected database, we identified 103 patients with nonmetastatic IBC who received trimodality therapy at our institution from 2007 to 2015. Descriptive statistics were used to describe the study cohort and compare retrospectively extracted rates of radiation therapy-associated toxicity. The actuarial rate of LRR-free survival was analyzed using the Kaplan-Meier method.
Results:
The median follow-up is 3.6 years. Thirty-nine patients (37.9%) received postmastectomy radiation therapy (PMRT) to the chest wall and undissected regional lymphatics in QD fractions (median dose, 50.0 Gy in 25 fractions [fx]; median boost dose, 10.0 Gy in 5 fx) and 64 patients (62.1%) received BID PMRT (median dose, 51.0 Gy in 34 fx; median boost dose, 15.0 Gy in 10 fx). Crude rates of toxicity were not different between patients treated with QD or BID PMRT. Two BID patients (3.1%) and no QD patients (0.0%) experienced LRR (P = .53). The 3- and 5-year LRR-free survival were 95.1% and 100.0% for BID and QD patients, respectively (P = .25).
Conclusions:
Tailoring radiation therapy to clinical risk factors was associated with excellent locoregional control. De-escalation of PMRT from BID to QD was not clearly associated with reduced toxicity compared with BID, although retrospective data collection may limit this comparison.

Related Concept Videos
 02:50
Combination Therapies and Personalized Medicine
The combination of the drug acetazolamide and sulforaphane is a good example of combination therapy to treat cancer. The cells in the interior of a large tumor often die due to the hypoxic and...
 01:28
Maslow's Humanistic Approach on Personality
 02:49
Cancer Therapies
However, cancer treatments can pose several challenges, as therapies used to kill cancer cells are generally also toxic to normal cells. Moreover, cancer cells mutate rapidly and can develop resistance to chemical agents or radiation therapy. Besides, all types of cancer cells may not respond to the same therapy. Some cancer cells respond to one...
 01:18
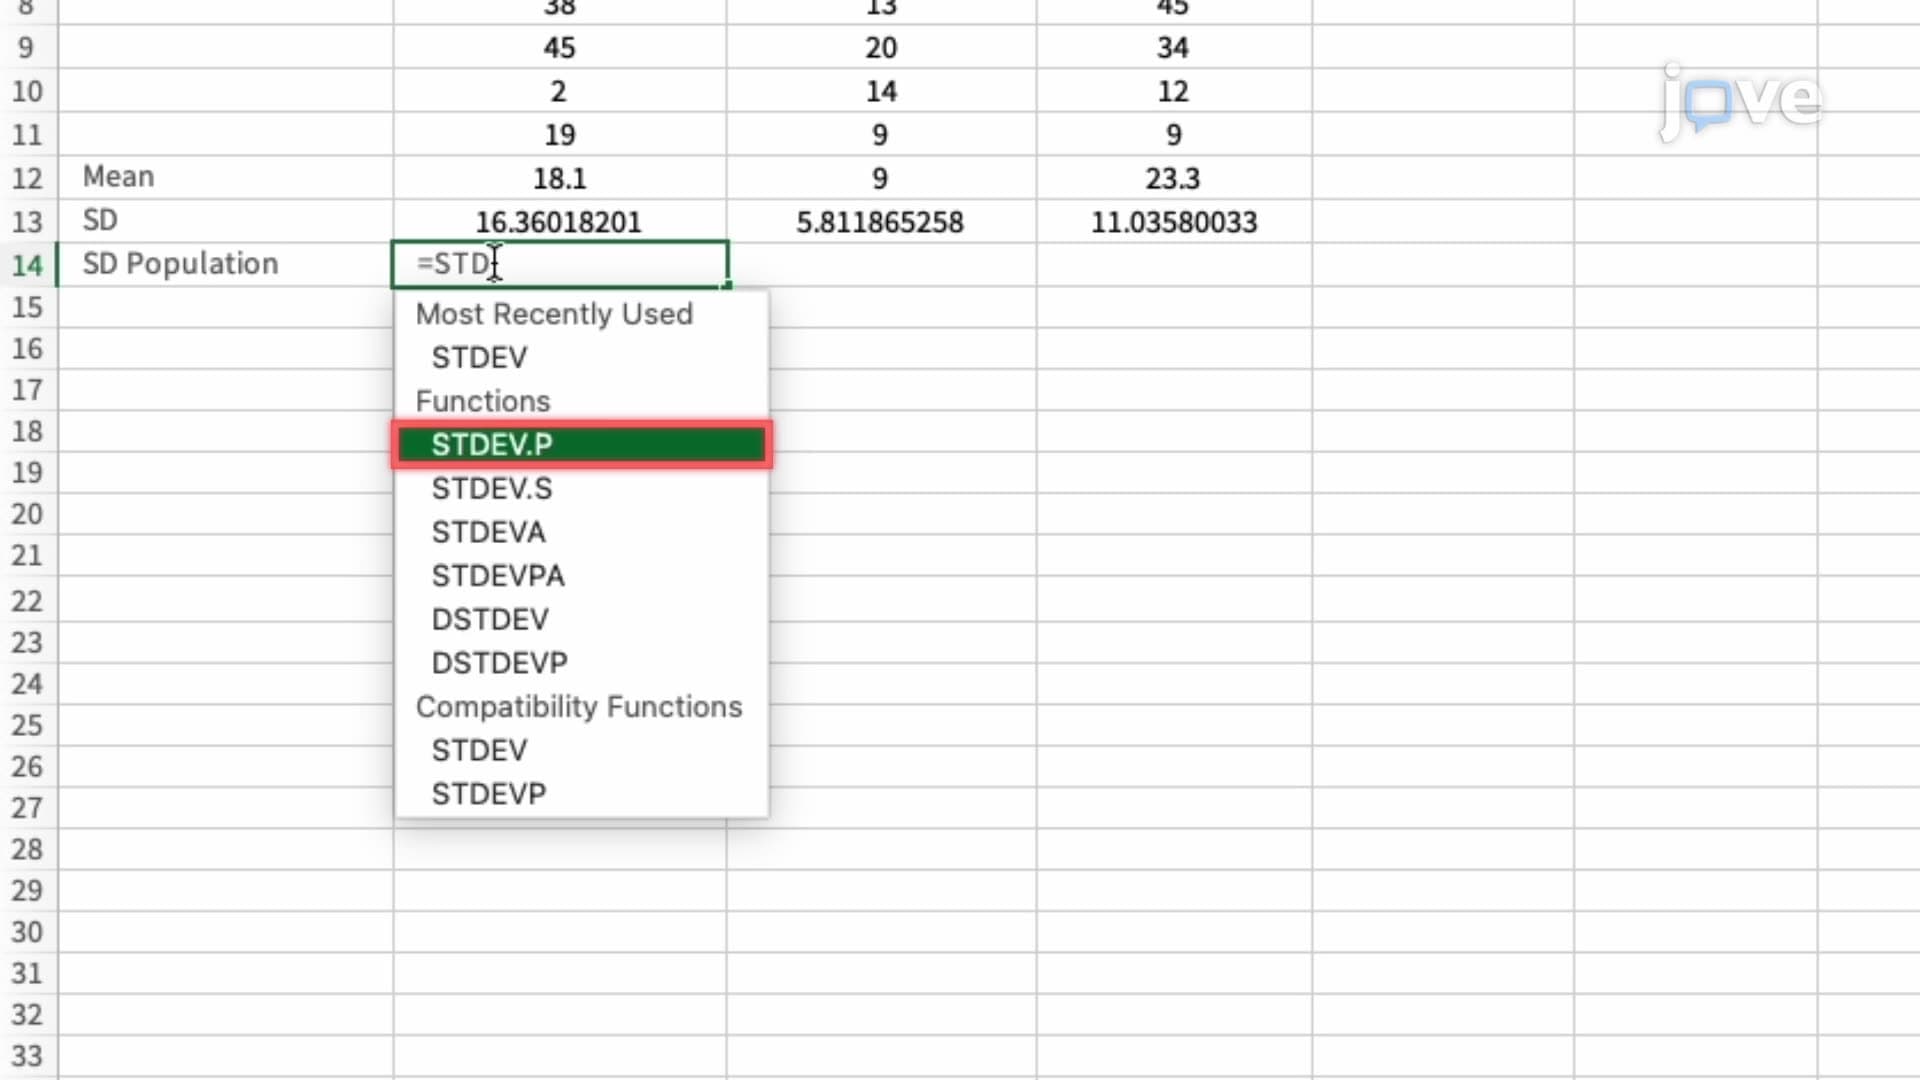
Microsoft Excel: Plotting Mean, SD, and SE
First, calculate the mean, SD, and SE of your data. The mean is obtained using the formula `=AVERAGE(range)`, while SD can be calculated with `=STDEV.P(range)` for a population or `=STDEV.S(range)` for a sample. SE is calculated as `=SD/SQRT(n)`, where `n` is the sample size.
To plot these values, use a bar...
 02:57
Targeted Cancer Therapies
There are several types of targeted therapies against...
 01:23
Types of Biopharmaceutical Studies: Controlled and Non-Controlled Approaches
Non-controlled studies, commonly employed for initial exploration, lack a control group, rendering them susceptible to biases and external influences. In contrast,...