Related Experiment Video
Updated: Jan 24, 2026
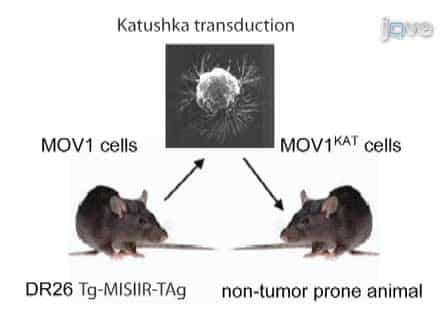
An Orthotopic Model of Serous Ovarian Cancer in Immunocompetent Mice for in vivo Tumor Imaging and Monitoring of Tumor Immune Responses
Published on: November 28, 2010
Potential Consequences of Minimum-Volume Standards for Hospitals Treating Women With Ovarian Cancer
Jason D Wright1, Yongmei Huang, Alexander Melamed
1Columbia University College of Physicians and Surgeons, the Joseph L. Mailman School of Public Health, Columbia University, and the Herbert Irving Comprehensive Cancer Center, New York Presbyterian Hospital, New York, New York; Massachusetts General Hospital, Boston, Massachusetts; and Rutgers Robert Wood Johnson Medical School; and the Environmental and Occupational Health Sciences Institute (EOHSI), Piscataway, New Jersey.

Objective:
To assess the potential effects of implementing minimum hospital volume standards for ovarian cancer on survival and access to care.
Methods:
We used the National Cancer Database to identify hospitals treating women with ovarian cancer from 2005 to 2015. We estimated the number of patients treated by each hospital during the prior year. Multivariable models were used to estimate the ratio of observed/expected 60-day, and 1-, 2- and 5-year mortalities. The mean predicted observed/expected ratio of hospitals was plotted based on prior year volume. The number of hospitals that would be restricted if minimum-volume standards were implemented was modeled.
Results:
A total of 136,196 patients treated at 1,321 hospitals were identified. Increasing hospital volume was associated with decreased 60-day (P=.004), 1-year (P<.001), 2-year (P<.001) and 5-year (P=.008) mortality. In 2015, using a minimum-volume cutpoint of one case in the prior year would eliminate 144 (13.6%) hospitals (treated 2.6% of all patients); a cutpoint of three would eliminate 364 (34.5%) hospitals (treated 7.7% of the patients). The mean observed/expected ratios for hospitals with a prior year volume of 1 was 1.14 for 60-day mortality, 1.06 for 1-year mortality, 1.12 for 2-year mortality, and 1.08 for 5-year mortality. Among hospitals with a prior year volume of one, 49.2% had an observed/expected ratio for 2-year mortality of at least 1 (indicating worse than expected performance), and 50.8% had an observed/expected ratio of less than 1 (indicating better than expected performance). The mean observed/expected ratios for hospitals with a prior year volume of two or less were 1.11 for 60-day mortality, 1.09 for 1-year mortality, 1.08 for 2-year mortality, and 1.07 for 5-year mortality. Implementing a minimum-volume standard of one case in the prior year would result in one fewer death for every 198 patients at 60 days, for every 613 patients at 1 year, and for every 62 patients at 5 years.
Conclusion:
Implementation of minimum hospital volume standards could restrict care at a significant number of hospitals, including many centers with better-than-predicted outcomes.

Related Concept Videos
 03:02
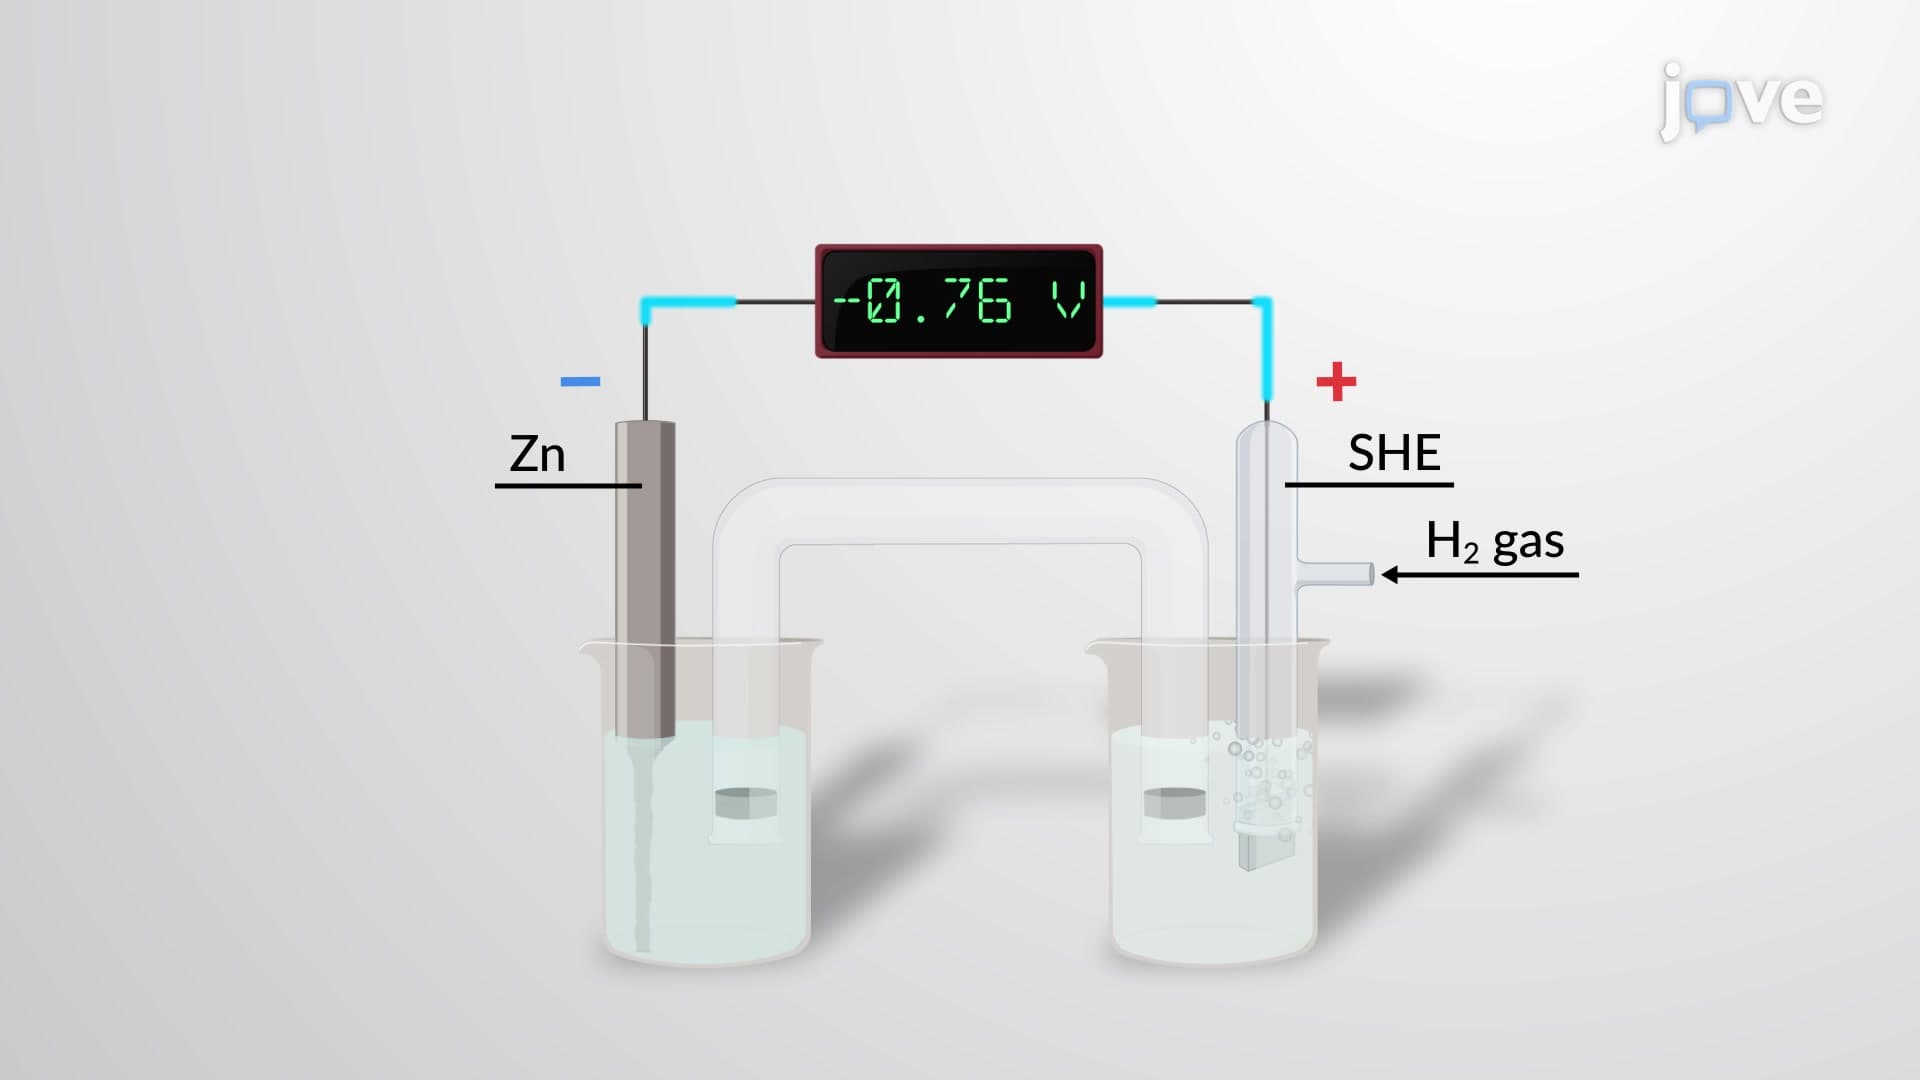
Standard Electrode Potentials
 00:59
Hospitals-II
Nurses that work in...
 01:28
Hospitals-I
 01:08
Timing and Consequences on Behavior
Humans, however, can respond to delayed reinforcers. We often make decisions between immediate small rewards and delayed larger rewards. This ability to delay gratification is a significant...
 02:58
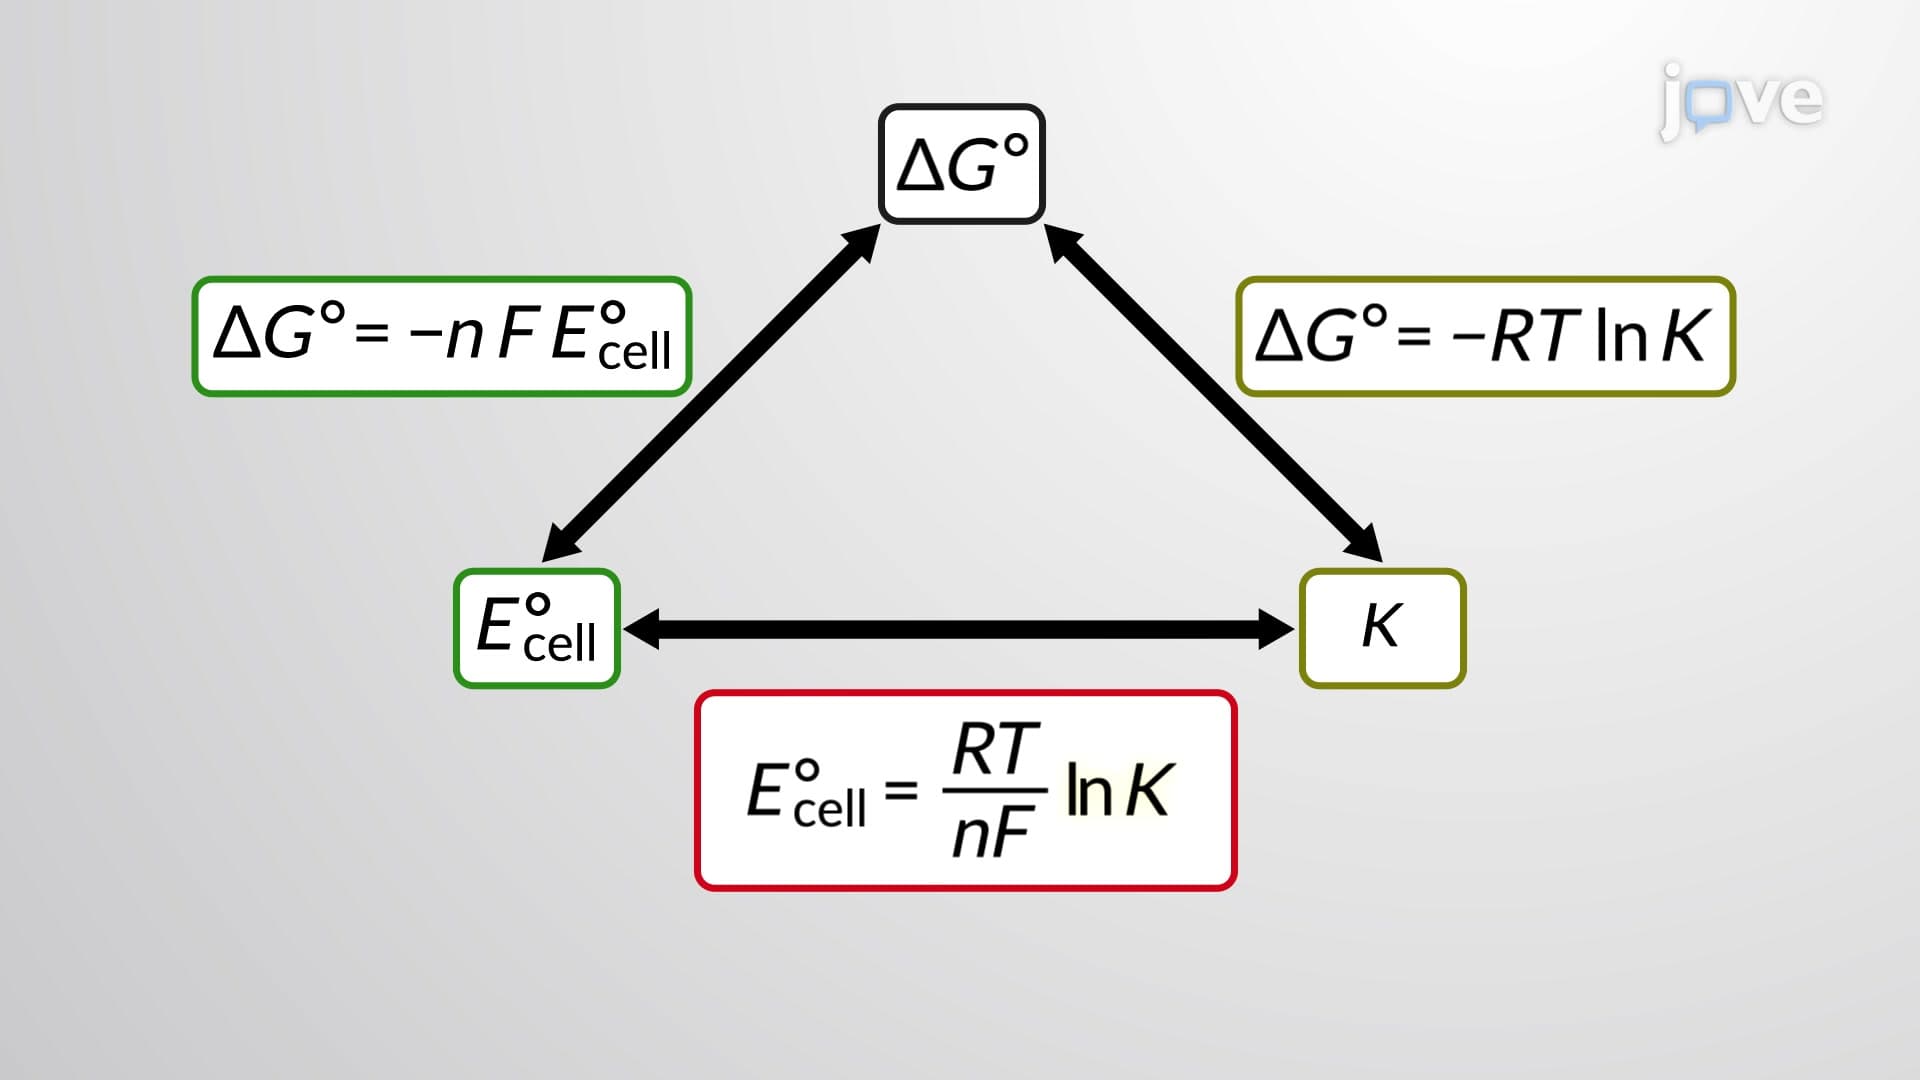
Cell Potential and Free Energy
Thermodynamics is the branch of physics dealing with the relationship between heat and other forms of energy. In an electrochemical cell, chemical energy is converted into electrical energy.
Thus, a link can be predicted between cell potential, free energy change, and the equilibrium constant for the reaction. Cell potential can also be measured as the oxidant or the reducing strength, and similar acid-base strength measures are reflected in equilibrium...
 01:27
Ovarian Cycle