Related Experiment Video
Updated: Jan 23, 2026
Single-Port Robotic-assisted Transaxillary Breast-conserving Surgery: A Prospective, Single-arm, Non-randomized Phase IIa Clinical Trial
Published on: August 19, 2025
The ultrasound-guided proximal intercostal block: anatomical study and clinical correlation to analgesia for breast
Nantthasorn Zinboonyahgoon1, Panya Luksanapruksa2, Sitha Piyaselakul3
1Department of Anesthesiology, Siriraj Hospital, Mahidol University, 2 Phranok road, Bangkoknoi, 10700, Thailand.

Background:
The ultrasound-guided proximal intercostal block (PICB) is performed at the proximal intercostal space (ICS) between the internal intercostal membrane (IIM) and the endothoracic fascia/parietal pleura (EFPP) complex. Injectate spread may follow several routes and allow for multilevel trunk analgesia. The goal of this study was to examine the anatomical spread of large-volume PICB injections and its relevance to breast surgery analgesia.
Methods:
Fifteen two-level PICBs were performed in ten soft-embalmed cadavers. Radiographic contrast mixed with methylene blue was injected at the 2nd(15 ml) and 4th(25 ml) ICS, respectively. Fluoroscopy and dissection were performed to examine the injectate spread. Additionally, the medical records of 12 patients who had PICB for breast surgery were reviewed for documented dermatomal levels of clinical hypoesthesia. The records of twelve matched patients who had the same operations without PICB were reviewed to compare analgesia and opioid consumption.
Results:
Median contrast/dye spread was 4 (2-8) and 3 (2-5) vertebral segments by fluoroscopy and dissection respectively. Dissection revealed injectate spread to the adjacent paravertebral space, T3 (60%) and T5 (27%), and cranio-caudal spread along the endothoracic fascia (80%). Clinically, the median documented area of hypoesthesia was 5 (4-7) dermatomes with 100 and 92% of the injections covering adjacent T3 and T5 dermatomes, respectively. The patients with PICB had significantly lower perioperative opioid consumption and trend towards lower pain scores.
Conclusions:
In this anatomical study, PICB at the 2nd and 4th ICS produced lateral spread along the corresponding intercostal space, medial spread to the adjacent paravertebral/epidural space and cranio-caudal spread along the endothoracic fascial plane. Clinically, combined PICBs at the same levels resulted in consistent segmental chest wall analgesia and reduction in perioperative opioid consumption after breast surgery. The incomplete overlap between paravertebral spread in the anatomical study and area of hypoesthesia in our clinical findings, suggests that additional non-paravertebral routes of injectate distribution, such as the endothoracic fascial plane, may play important clinical role in the multi-level coverage provided by this block technique.
Related Concept Videos
 02:20
Correlations
 01:25
Analgesia and Pain Management
 01:27
Correlation and Causation
Correlation versus Causation
If the dependent variable increases or decreases when the independent variable increases, there is a positive or negative...
 01:30
Local Anesthetics: Clinical Application as Surface, Infiltration, and Conduction Block Anesthesia
 01:09
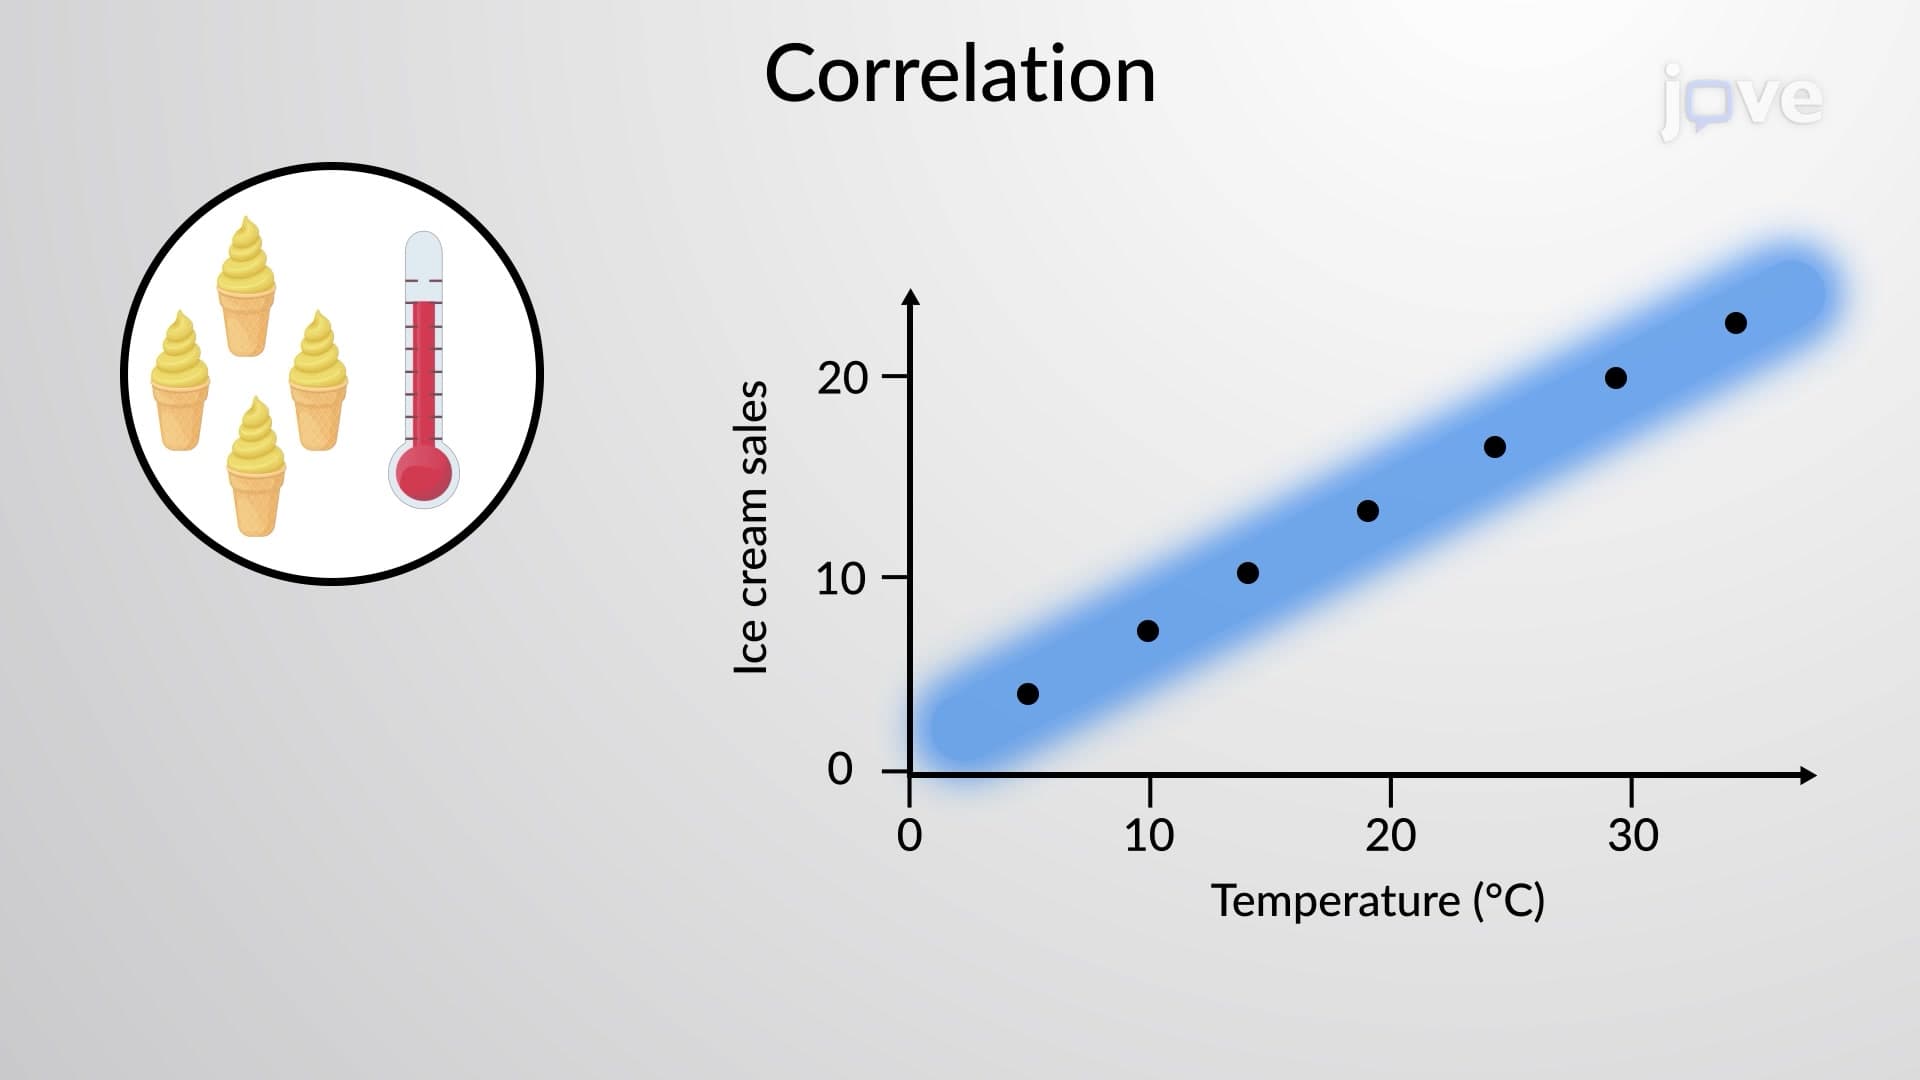
Correlation
Two variables, for example, a and b, are said to be positively correlated if both variables move in the same direction. In other words, a positive correlation exists between two variables, a and b, if:
 01:11
Anatomical Positions
The body is upright, facing forward, and standing erect.
The feet are parallel and flat on the floor.
The arms are hanging by the...