Related Experiment Video
Updated: Jan 23, 2026
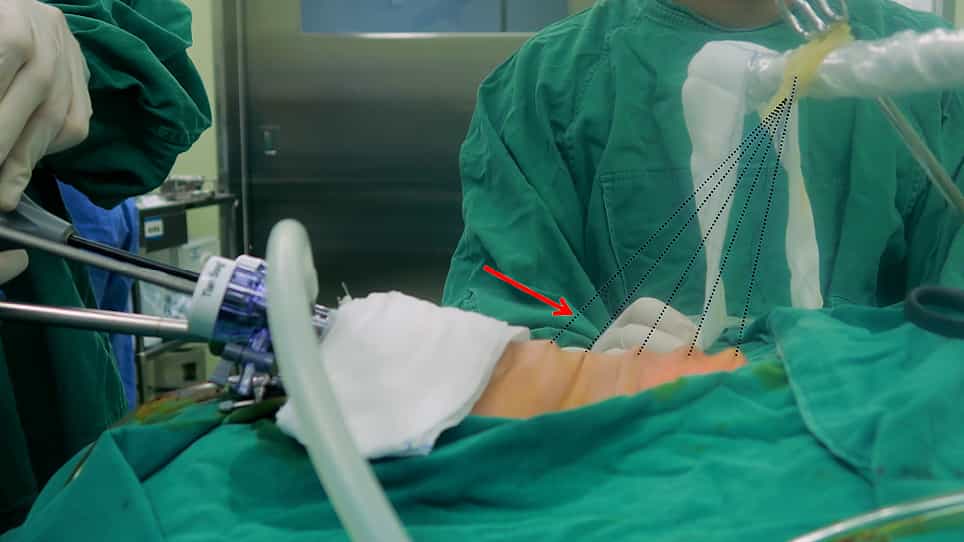

Transoral Endoscopic Thyroidectomy Vestibular Approach for Thyroid Lobectomy
Published on: May 12, 2023
Stimulating and dissecting instrument for transoral endoscopic thyroidectomy: proof of concept investigation
Daqi Zhang1, Shijie Li1, Gianlorenzo Dionigi2
1Division of Thyroid Surgery, Jilin Provincial Key Laboratory Of Surgical Translational Medicine, Jilin Provincial Precision Medicine Laboratory of Molecular Biology and Translational Medicine on Differentiated Thyroid Carcinoma, China-Japan Union Hospital Of Jilin University, 126 Xiantai Blvd, Changchun, Jilin, People's Republic of China.

Objectives/Hypothesis:
Intraoperative neuromonitoring (IONM) is a useful adjunct for recurrent laryngeal nerve (RLN) mapping and identification in transoral endoscopic thyroidectomy vestibular approach (TOETVA). This experimental study aimed to investigate the feasibility, safety, thresholds required of an endoscopic forceps that combine the function of surgical dissection and nerve stimulation.
Study Design:
Prospective experimental research.
Methods:
TOETVA was performed in 12 piglets, i.e., 24 RLNs and 24 vagal nerves (VN). RLNs electromyography (EMG) was recorded via endotracheal surface electrodes. Baseline EMG of VN and RLN were recorded and compared by (a) percutaneously placed monopolar stimulator probe (Group I), (b) adapted Maryland endoscopic dissector applied on nerves at its tip-end (Group II) and (c) endoscopic dissector tip-lateral applied (Group III). EMG profiles, amplitude, latency, waveform, thresholds and supra-maximal stimulation (5 mA) were analyzed.
Results:
Application of the endoscopic device was feasible in all TOETVA and did not result in any morbidity. 24 RLNs and VNs were detected, stimulated and monitored. With increase of stimulation current, the amplitude of EMG increased, showing a dose-response curve. Mean VN stimulation thresholds were: Group I 0.28 mA, Group II 0.56 mA, Group III 0.58 mA (P1 = 0.00, P2 = 0.00, P3 = 0.11). Minimal current to evoked a maximal VN response was: Group I 0.65 mA, Group II 1.07 mA and Group III 1.14 mA (P1 = 0.00, P2 = 0.00, P3 = 0.48). Minimal current to evoke a RLN maximal response was Group I 0.6 mA, Group II 0.95 mA and Group III 1.05 mA (P1 = 0.00, P2 = 0.00, P3 = 0.31). Latency values were similar to each group. Repetitive (> 10 min) supra-maximal (> 5 mA) electrical stimulation was safe.
Conclusions:
The application of endoscopic stimulating dissector is simple, effective and safe way to monitor both VN and RLN function during a TOETVA animal model. It provides surgeons with real-time feedback of EMG response and can be applied as a tool for RLN monitoring. Endoscopic instrument required higher current to evoke EMG response compared to hand probe stimulation. Tip-end required less current to evoke EMG response compared to tip-lateral mode of stimulation.
More Related Videos
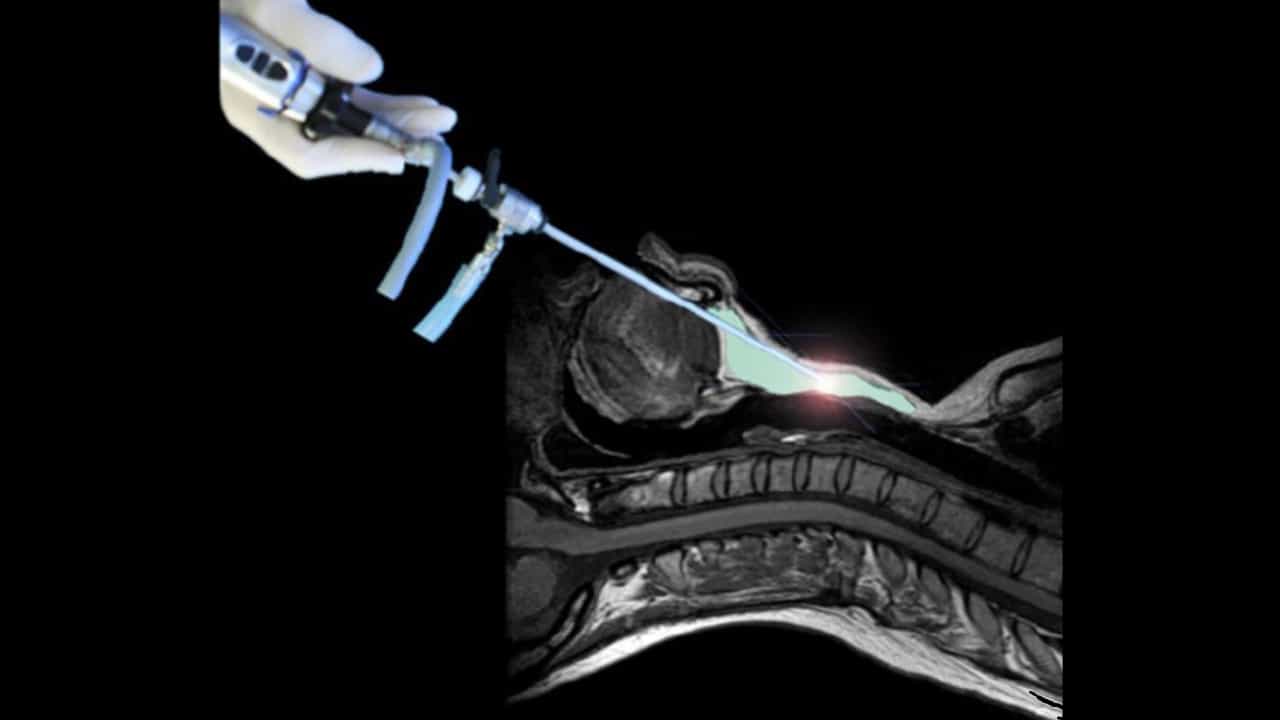 04:01
Transoral Robotic Total Thyroidectomy and Bilateral Central Regional Lymph Node Dissection for Papillary Thyroid Carcinoma
Published on: September 15, 2023
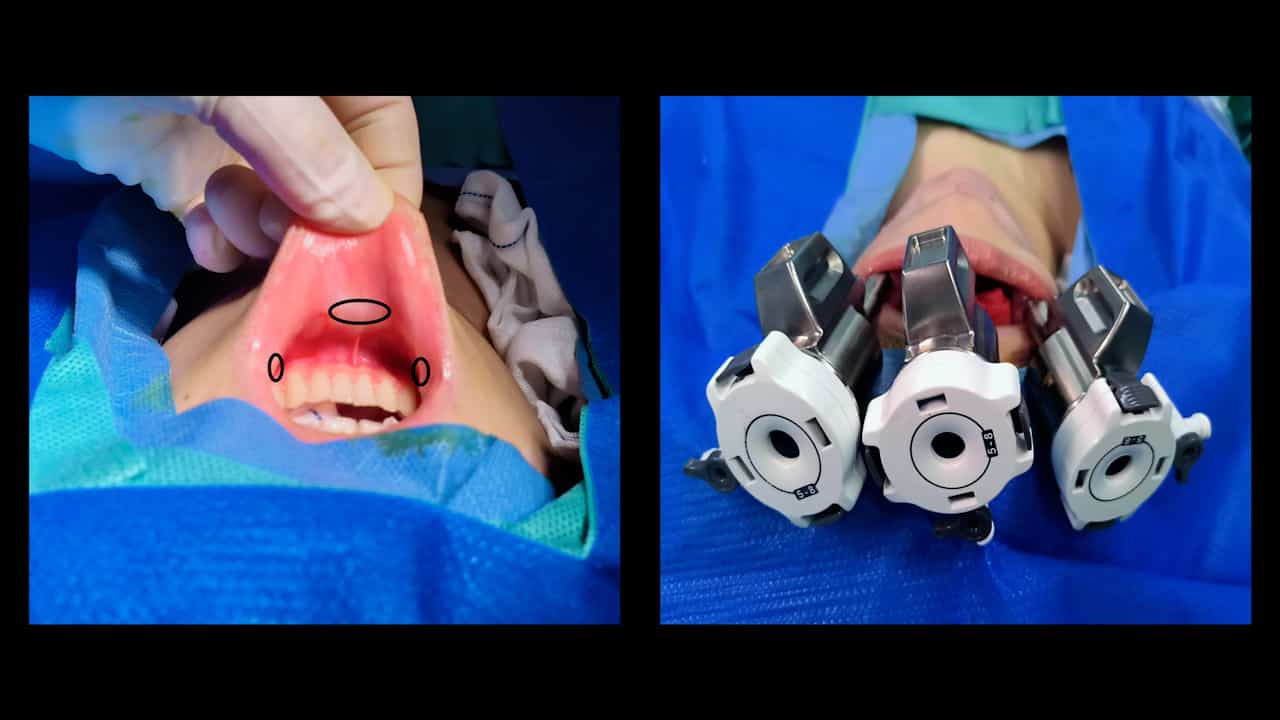 05:25
Identification and Protection of the Recurrent Laryngeal Nerve during Transoral Robotic Thyroidectomy
Published on: October 24, 2025
Related Concept Videos
 00:52
Social Proof
 01:19
Self-Concept
Infancy and Emerging Recognition
During infancy, self-concept is virtually nonexistent. Babies do not distinguish themselves as separate entities and often mistake their...
 01:24
Concepts and Prototypes
The brain organizes this information using concepts, which are mental categories grouping linguistic data,...
 02:56
Formula Mass and Mole Concepts of Compounds
 01:23
Instrument Transformers
 01:12
Instrument Calibration
Analytical Balance Calibration
An analytical balance measures mass and requires regular calibration to...