Related Experiment Video
Updated: Jan 22, 2026


Role of Diffusion MRI Tractography in Endoscopic Endonasal Skull Base Surgery
Published on: July 5, 2021
Endoscopic transorbital approach to anterolateral skull base through inferior orbital fissure: a cadaveric study
Bon-Jour Lin1,2, Da-Tong Ju1, Tzu-Hsien Hsu1,3
1Department of Neurological Surgery, Tri-Service General Hospital, National Defense Medical Center, No. 325, Section 2, Cheng-Kung Road, Neihu, 114, Taipei, Taiwan, Republic of China.

Background:
Endoscopic transorbital approach (eTOA) has been announced as an alternative minimally invasive surgery to skull base. Owing to the inferior orbital fissure (IOF) connecting the orbit with surrounding pterygopalatine fossa (PPF), infratemporal fossa (ITF), and temporal fossa, the idea of eTOA to anterolateral skull base through IOF is postulated. The aim of this study is to access its practical feasibility.
Methods:
Anatomical dissections were performed in five human cadaveric heads (10 sides) using 0-degree and 30-degree endoscopes. A stepwise description of eTOA to anterolateral skull base through IOF was documented. The anterosuperior corner of the maxillary sinus in the horizontal plane of the upper edge of zygomatic arch was defined as reference point (RP). The distances between the RP to the foramen rotundum (FR), foramen ovale (FO), and Gasserian ganglion (GG) were measured. The exposed area of anterolateral skull base in the coronal plane of the posterior wall of the maxillary sinus was quantified.
Results:
The surgical procedure consisted of six steps: (1) lateral canthotomy with cantholysis and preseptal lower eyelid approach with periorbita dissection; (2) drilling of the ocular surface of greater sphenoid wing and lateral orbital rim osteotomy; (3) entry into the maxillary sinus and exposure of PPF and ITF; (4) mobilization of infraorbital nerve with drilling of the infratemporal surface of the greater sphenoid wing and pterygoid process; (5) exposure of middle cranial fossa, Meckel's cave, and lateral wall of cavernous sinus; and (6) reconstruction of orbital floor and lateral orbital rim. The distances measured were as follows: RP-FR = 45.0 ± 1.9 mm, RP-FO = 55.7 ± 0.5 mm, and RP-GG = 61.0 ± 1.6 mm. In comparison with the horizontal portion of greater sphenoid wing, the superior and inferior axes of the exposed area were 22.3 ± 2.1 mm and 20.5 ± 1.8 mm, respectively. With reference to the FR, the medial and lateral axes of the exposed area were 11.6 ± 1.1 mm and 15.8 ± 1.6 mm, respectively.
Conclusions:
The eTOA through IOF can be used as a minimally invasive surgery to access whole anterolateral skull base. It provides a possible resolution to target lesion involving multiple compartments of anterolateral skull base.

Related Concept Videos
 02:44
Atomic Orbitals
 01:26
Endoscopic Studies II: Thoracocentesis
Description
Excess pleural fluid or air may accumulate in some respiratory disorders in the thoracic cavity. To treat pleural effusion, a physician conducts thoracentesis by carefully piercing the chest wall and entering...
 03:51
Molecular Orbital Theory II
 02:35
Molecular Orbital Theory I
 03:35
Hybridization of Atomic Orbitals II
 01:18
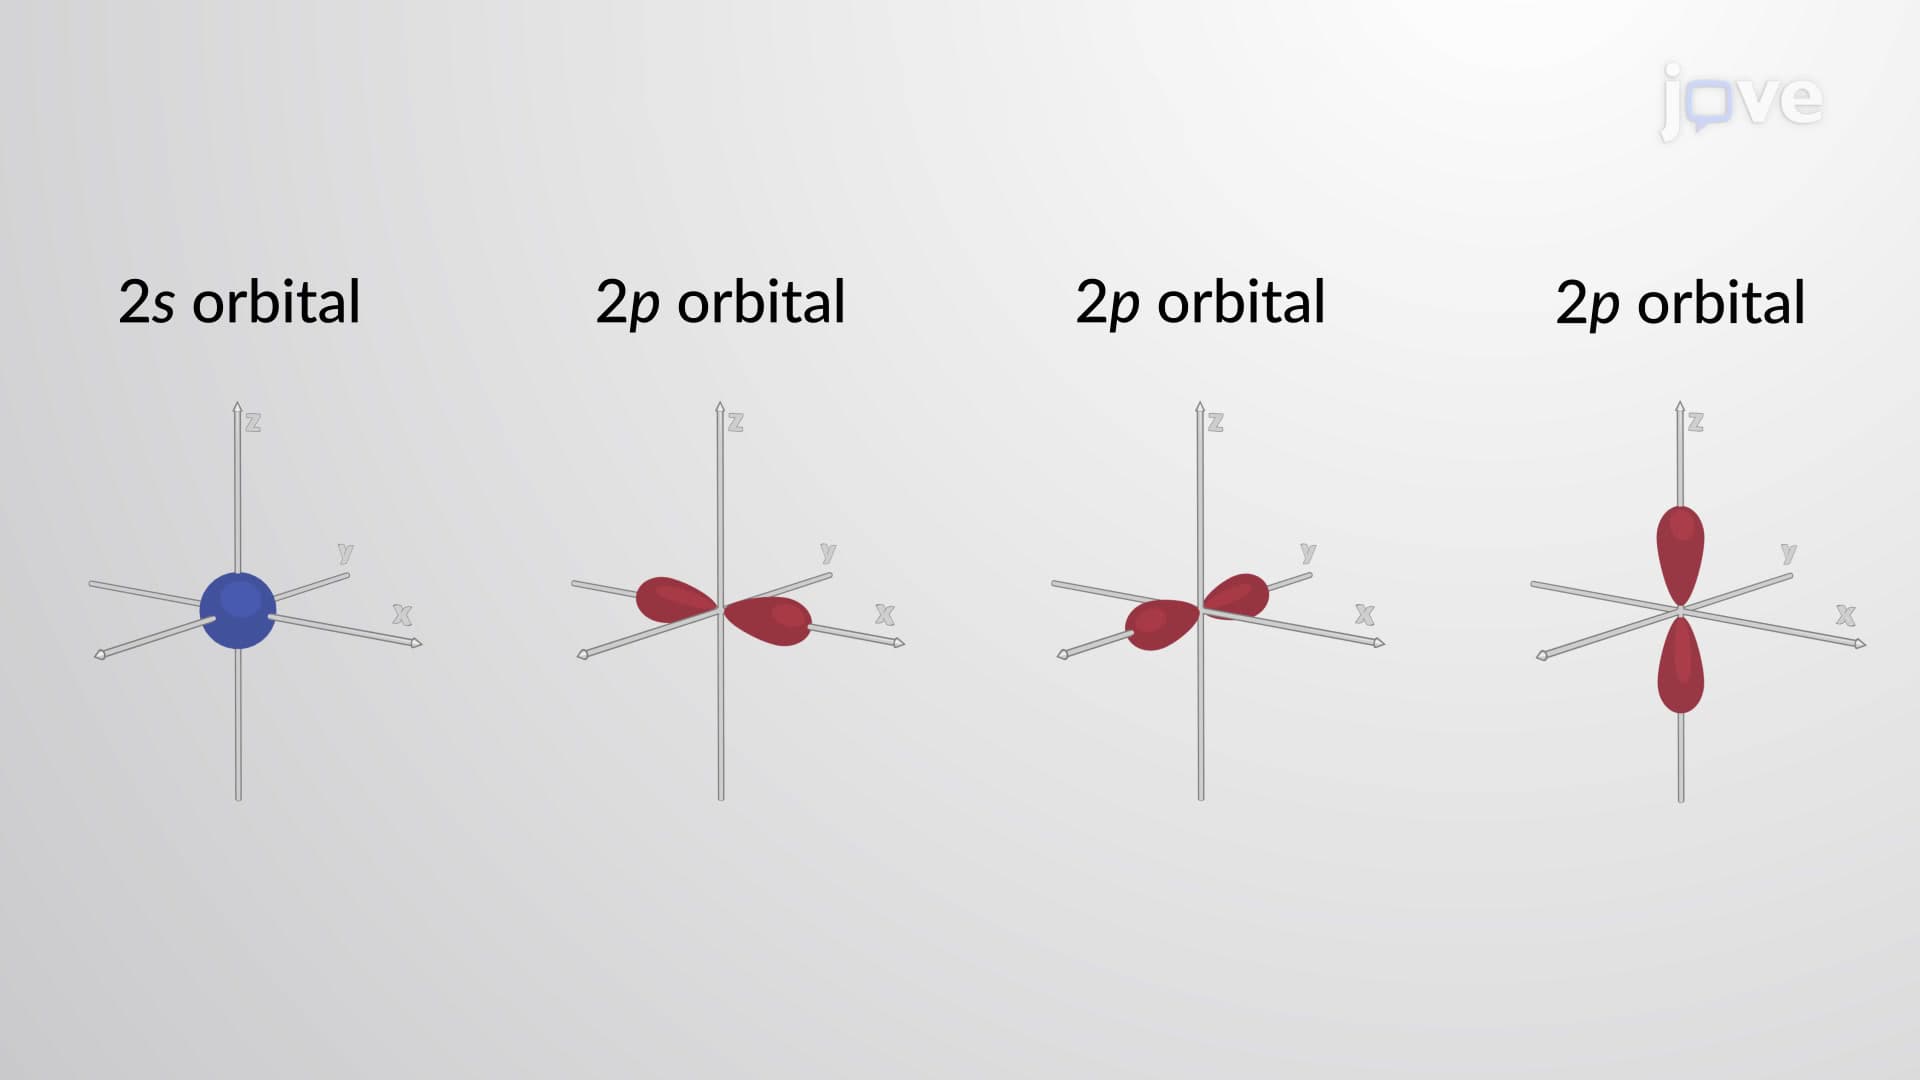
Electron Orbital Model
The first shell is closest to the nucleus, and it has only one subshell with a single spherical orbital called the...