Related Experiment Video
Updated: Jan 22, 2026


Description of a Swine Infant Model of Volume-Controlled Hemorrhagic Shock
Published on: November 3, 2023
The effect of hemorrhage control adjuncts on outcome in severe pelvic fracture: A multi-institutional study
Juan Duchesne1, Todd W Costantini, Mansoor Khan
1From the Department of Surgery, Division of Trauma & Critical Care, Tulane University School of Medicine (J.D.), New Orleans, Louisiana; Department of Surgery, Division of Trauma, Surgical Critical Care, and Acute Care Surgery, University of California San Diego Health (T.W.C.), San Diego, California; Imperial College Healthcare NHS Trust, St. Mary's Hospital, Imperial College Healthcare NHS Trust (M.K., J.G.), London, England; UTHealth, McGovern Medical School, Department of Surgery, Division of Acute Care Surgery, Trauma, & Critical Care, Memorial Hermann Texas Medical Center (E.T.), Houston, Texas; Grady Emory University School of Medicine, Department of Surgery Grady Memorial Hospital (P.R., B.M., N.N.), Atlanta, Georgia; Ryder Trauma Center at Jackson Memorial Hospital and DeWitt Daughtry Family Department of Surgery, Division of Trauma, University of Miami Miller School of Medicine (A.S.), Miami, Florida; Division of Trauma/Acute Care Surgery/Surgical Critical Care, Harbor-UCLA Medical Center (D.Y.K., E.H.), Los Angeles, California; Department of Surgery and Critical Care, University of Pittsburgh Medical Center (J.S., V.A.), Pittsburgh, Pennsylvania; Department of Surgery, Trauma/Critical Care & Acute Surgery Division, University of Kansas Medical Center (R.D.W.), Kansas City, Kansas; Department of Surgery, Division of Trauma, Critical Care, and Acute Care Surgery, Oregon Health & Science University (M.S., B.B.), Portland, Oregon; Trauma Specialist Program, Our Lady of the Lake Regional Medical Center (B.M., D.T.), Baton Rouge, Louisiana; and Perelman School of Medicine, Division of Traumatology, Surgical Critical Care, & Emergency Surgery, University of Pennsylvania Health System (S.R., M.S.), Philadelphia, Pennsylvania.

Background:
Hemodynamically unstable patients with severe pelvic fracture are a significant challenge to trauma surgeons and have high mortality. Significant variability across institutions in hemorrhage control adjuncts used to quell pelvic bleeding has been demonstrated. However, the effect of these methods on time to definitive bleeding control, type of resuscitation given, and outcomes remains unknown. We sought to elucidate those effects.
Methods:
This was a multicenter retrospective review of severe pelvic fracture patients in shock between 2011 and 2016. Shock was defined as systolic blood pressure less than 90 mm Hg, heart rate greater than 120 beats per minute, or base deficit less than -5. Definitive bleeding control was defined as time to surgical control in the operating room or embolization by interventional radiology. Significance level was at p less than 0.05.
Results:
A total of 279 severe pelvic fracture patients with shock on admission from 12 trauma centers were included. The cohort was primarily male (62%) with median (interquartile range) age of 40 years (28-54 years), Injury Severity Score of 38 (29-50), and Glasgow Coma Scale score of 13 (3-15). Overall mortality was 32%. The most common adjunct used was pelvic binder (50%) followed by no adjunct (30.5%); least common was resuscitative balloon occlusion of the aorta (REBOA) (2.5%). Preperitoneal packing alone and REBOA alone/with other adjunct(s) resulted in the fastest times to operating room/interventional radiology but also had the highest blood utilization and mortality rates. Resuscitative balloon occlusion of the aorta was most often used along with pelvic binder (6 of 13; 46%).
Conclusion:
Marked variation in management of severe pelvic fracture patients in shock indicates the need for a standardized approach to maximize outcomes and minimize transfusion requirements. The use of preperitoneal packing and/or REBOA yielded fastest times to definitive bleeding control. However, REBOA continues to be infrequently used. Future prospective analysis of this combination needs further validation in patients with severe pelvic hemorrhage.
Level Of Evidence:
Therapeutic study, level IV.


Related Concept Videos
 01:22
Heart Failure VI: Adjunct Therapies
 01:23
Types of Biopharmaceutical Studies: Controlled and Non-Controlled Approaches
Non-controlled studies, commonly employed for initial exploration, lack a control group, rendering them susceptible to biases and external influences. In contrast,...
 02:24
Predicting Reaction Outcomes
 01:13
Outcomes of Glycolysis
Cellular respiration can occur aerobically (with oxygen) or anaerobically (without oxygen). In the presence of oxygen, cellular respiration starts with glycolysis and continues with pyruvate...
 01:26
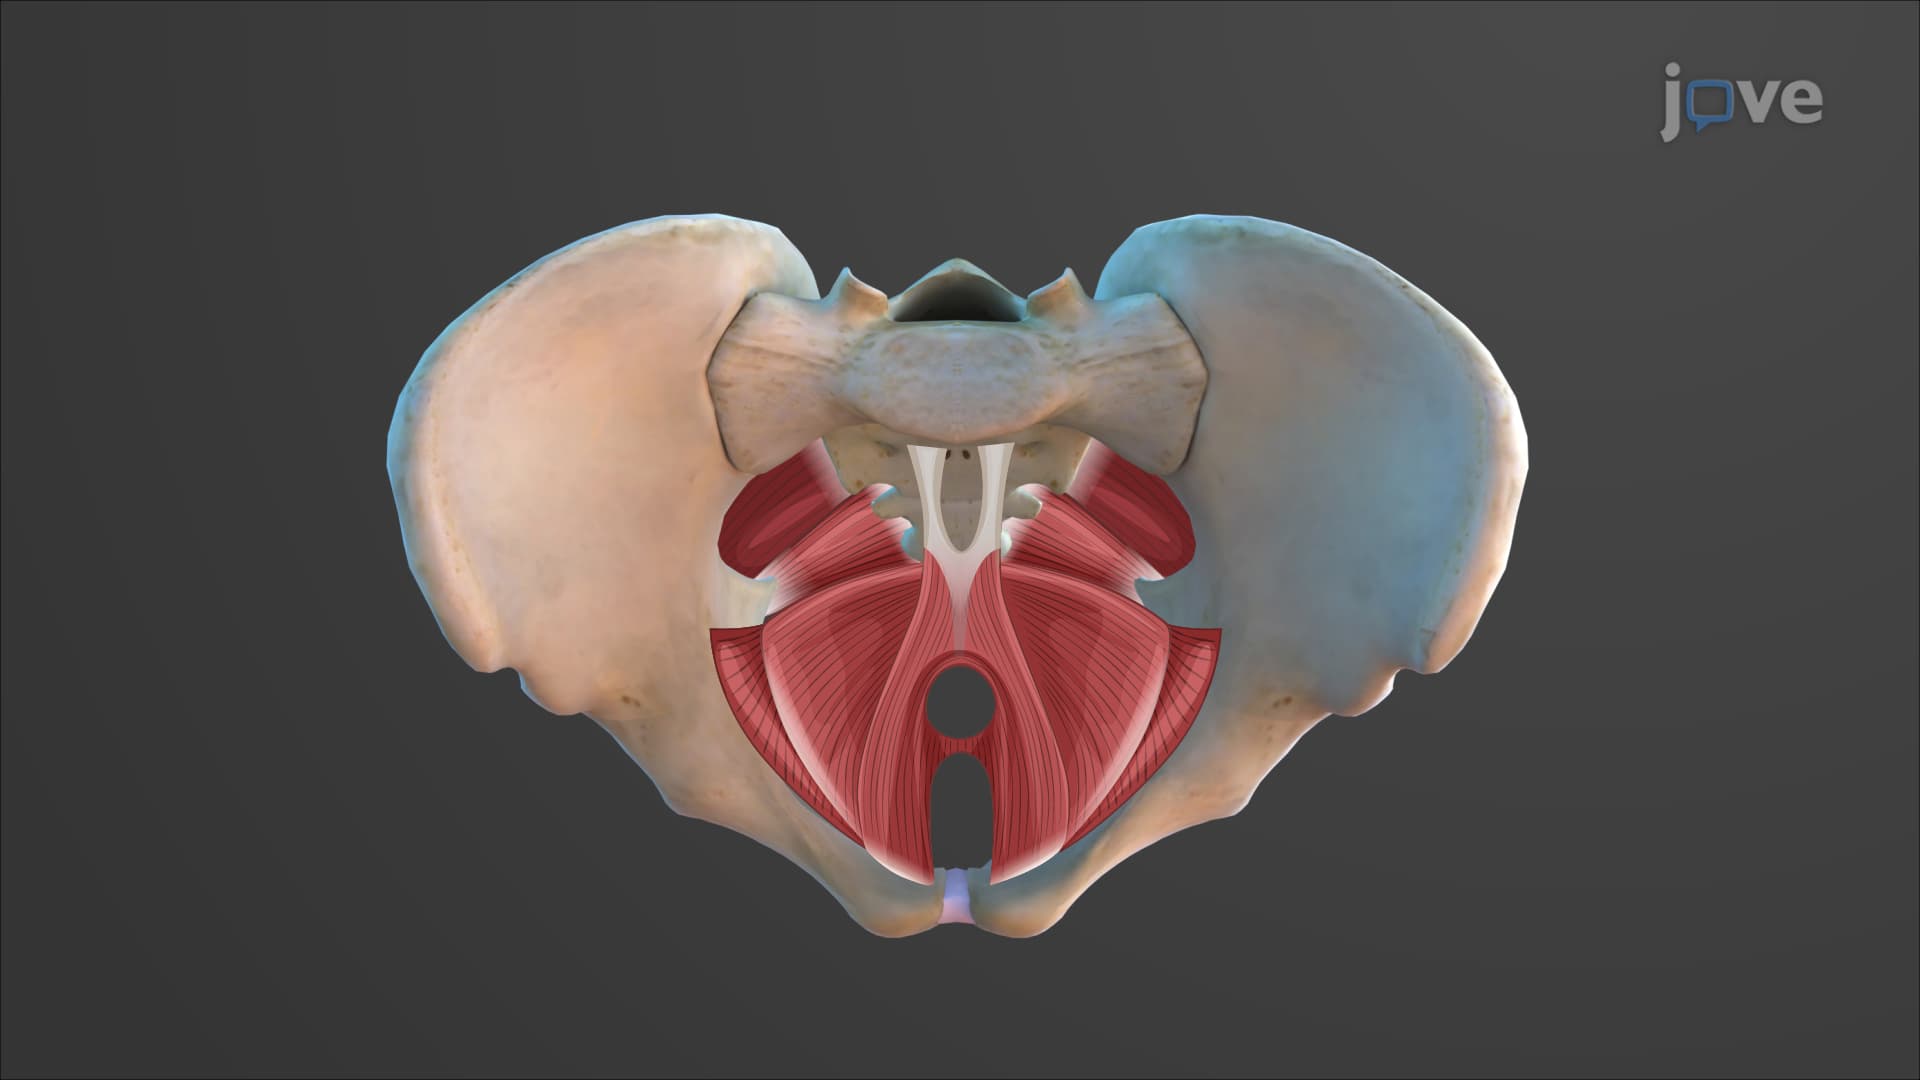
Muscles of the Pelvic Floor and Perineum
Perineal Layer
The perineum is a diamond-shaped area below the pelvic diaphragm, divided into an anterior urogenital triangle that contains the external genitals and a posterior anal triangle housing the anus. The urogenital...
 01:27
Fractures: Bone Repair
Minor fractures with no bone displacement are treated by immobilizing the fractured bone using a cast or splint. However, in the case of fractures with displaced bones, the broken bones are repositioned before immobilization to ensure successful healing without deformation and loss of function. The realignment of fractured bone ends is performed through a process called reduction. If the...