Related Experiment Video
Updated: Jan 22, 2026

Modeling Intracerebral Hemorrhage in Mice: Injection of Autologous Blood or Bacterial Collagenase
Published on: September 22, 2012
Intensive Blood Pressure Reduction and Perihematomal Edema Expansion in Deep Intracerebral Hemorrhage
Audrey C Leasure1, Adnan I Qureshi2, Santosh B Murthy3
1From the Department of Neurology (A.C.L., L.H.S., G.J.F., K.N.S.), Yale School of Medicine, New Haven, CT.

Background and Purpose- It is unknown whether blood pressure (BP) reduction influences secondary brain injury in spontaneous intracerebral hemorrhage (ICH). We tested the hypothesis that intensive BP reduction is associated with decreased perihematomal edema expansion rate (PHER) in deep ICH. Methods- We performed an exploratory analysis of the ATACH-2 randomized trial (Antihypertensive Treatment of Acute Cerebral Hemorrhage-2). Patients with deep, supratentorial ICH were included. PHER was calculated as the difference in perihematomal edema volume between baseline and 24-hour computed tomography scans divided by hours between scans. We used regression analyses to determine whether intensive BP reduction was associated with PHER and if PHER was associated with poor outcome (3-month modified Rankin Scale score 4-6). We then used interaction analyses to test whether specific deep location (basal ganglia versus thalamus) modified these associations. Results- Among 1000 patients enrolled in ATACH-2, 870 (87%) had supratentorial, deep ICH. Of these, 780 (90%) had neuroimaging data (336 thalamic and 444 basal ganglia hemorrhages). Baseline characteristics of the treatment groups remained balanced (P>0.2). Intensive BP reduction was associated with a decrease in PHER in univariable (β= -0.15; 95% CI, -0.26 to -0.05; P=0.007) and multivariable (β=-0.12; 95% CI, -0.21 to -0.02; P=0.03) analyses. PHER was not independently associated with outcome in all deep ICH (odds ratio, 1.14; 95% CI, 0.93-1.41; P=0.20), but this association was modified by the specific deep location involved (multivariable interaction P=0.02); in adjusted analyses, PHER was associated with poor outcome in basal ganglia (odds ratio, 1.42; 1.05-1.97; P=0.03) but not thalamic (odds ratio, 1.02; 95% CI, 0.74-1.40; P=0.89) ICH. Conclusions- Intensive BP reduction was associated with decreased 24-hour PHER in deep ICH. PHER was not independently associated with outcome in all deep ICH but was associated with poor outcome in basal ganglia ICH. PHER may be a clinically relevant end point for clinical trials in basal ganglia ICH.
Background and Purpose- It is unknown whether blood pressure (BP) reduction influences secondary brain injury in spontaneous intracerebral hemorrhage (ICH). We tested the hypothesis that intensive BP reduction is associated with decreased perihematomal edema expansion rate (PHER) in deep ICH. Methods- We performed an exploratory analysis of the ATACH-2 randomized trial (Antihypertensive Treatment of Acute Cerebral Hemorrhage-2). Patients with deep, supratentorial ICH were included. PHER was calculated as the difference in perihematomal edema volume between baseline and 24-hour computed tomography scans divided by hours between scans. We used regression analyses to determine whether intensive BP reduction was associated with PHER and if PHER was associated with poor outcome (3-month modified Rankin Scale score 4-6). We then used interaction analyses to test whether specific deep location (basal ganglia versus thalamus) modified these associations. Results- Among 1000 patients enrolled in ATACH-2, 870 (87%) had supratentorial, deep ICH. Of these, 780 (90%) had neuroimaging data (336 thalamic and 444 basal ganglia hemorrhages). Baseline characteristics of the treatment groups remained balanced (P>0.2). Intensive BP reduction was associated with a decrease in PHER in univariable (β= -0.15; 95% CI, -0.26 to -0.05; P=0.007) and multivariable (β=-0.12; 95% CI, -0.21 to -0.02; P=0.03) analyses. PHER was not independently associated with outcome in all deep ICH (odds ratio, 1.14; 95% CI, 0.93-1.41; P=0.20), but this association was modified by the specific deep location involved (multivariable interaction P=0.02); in adjusted analyses, PHER was associated with poor outcome in basal ganglia (odds ratio, 1.42; 1.05-1.97; P=0.03) but not thalamic (odds ratio, 1.02; 95% CI, 0.74-1.40; P=0.89) ICH. Conclusions- Intensive BP reduction was associated with decreased 24-hour PHER in deep ICH. PHER was not independently associated with outcome in all deep ICH but was associated with poor outcome in basal ganglia ICH. PHER may be a clinically relevant end point for clinical trials in basal ganglia ICH.

Related Concept Videos
 01:05
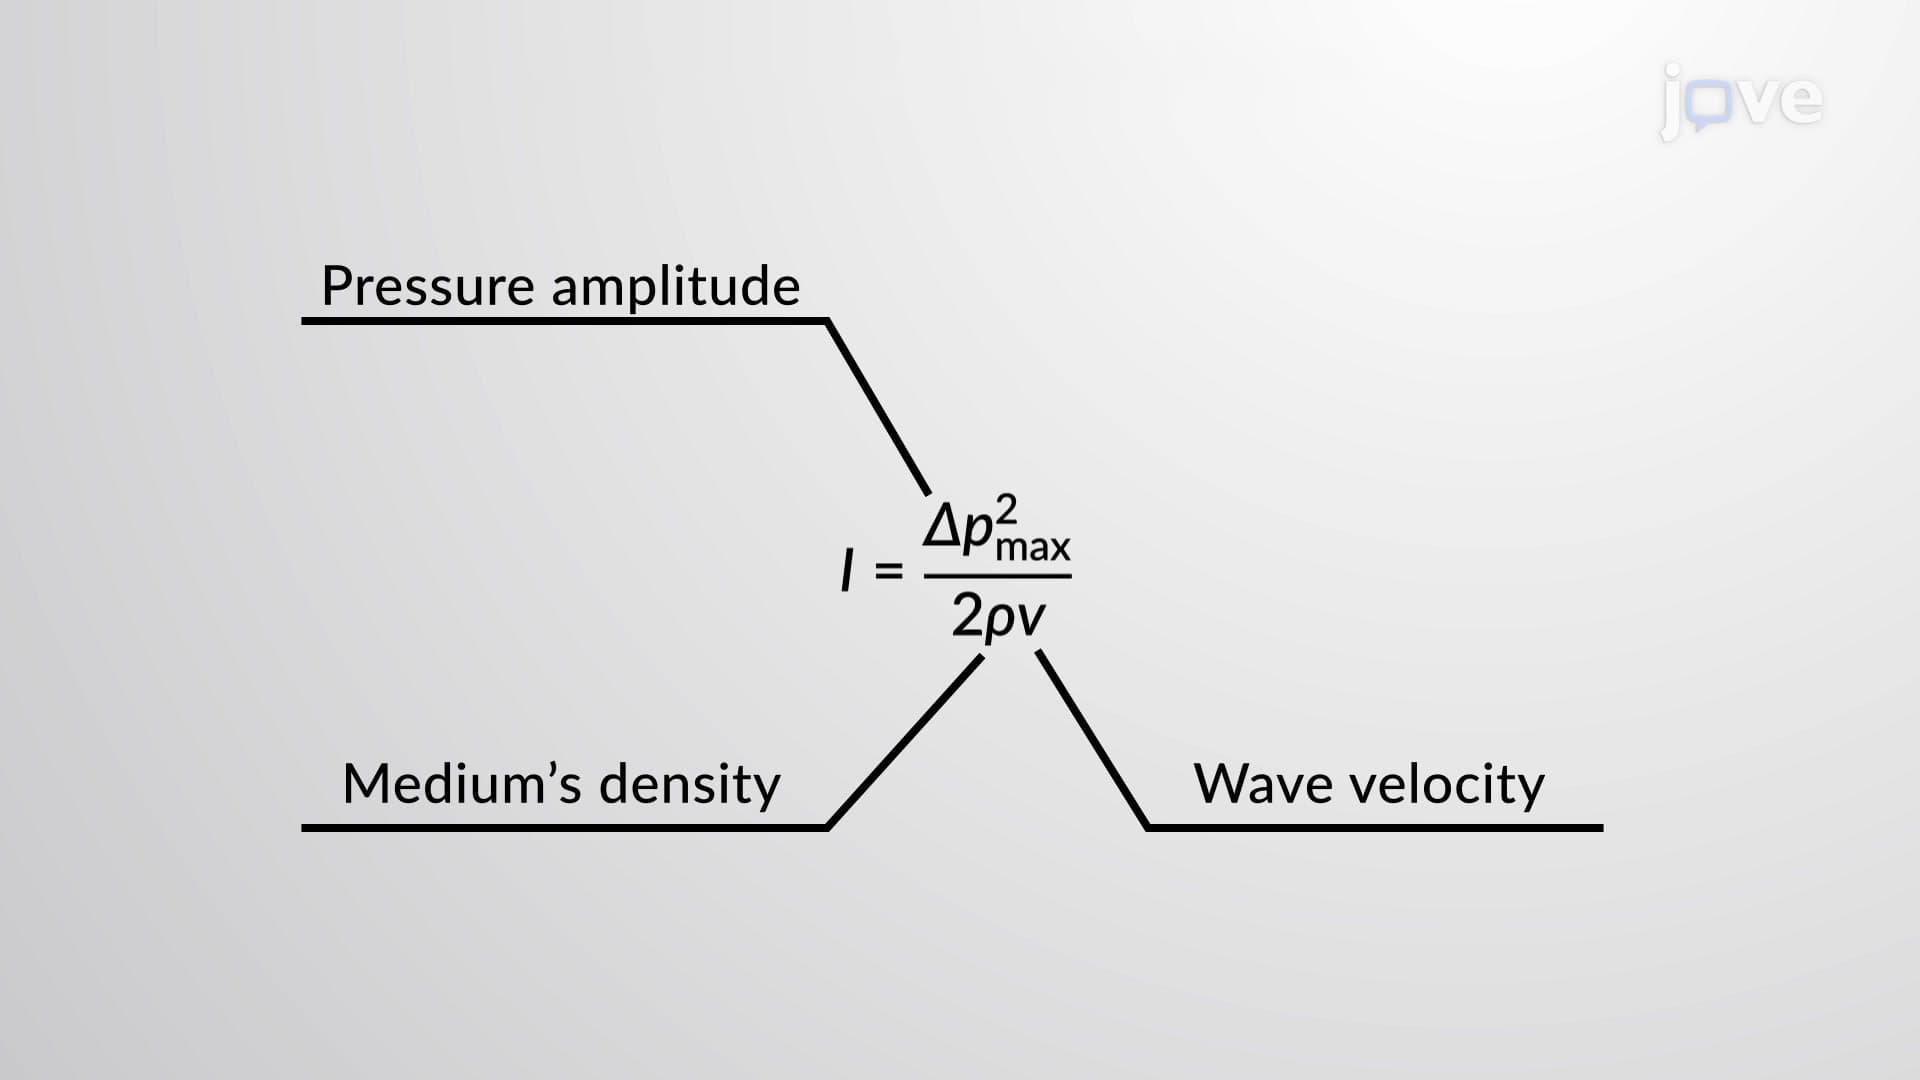
Intensity and Pressure of Sound Waves
Unlike the time average of a sinusoidal term, which is zero since it is positive...
 01:24
Blood Pressure
 01:30
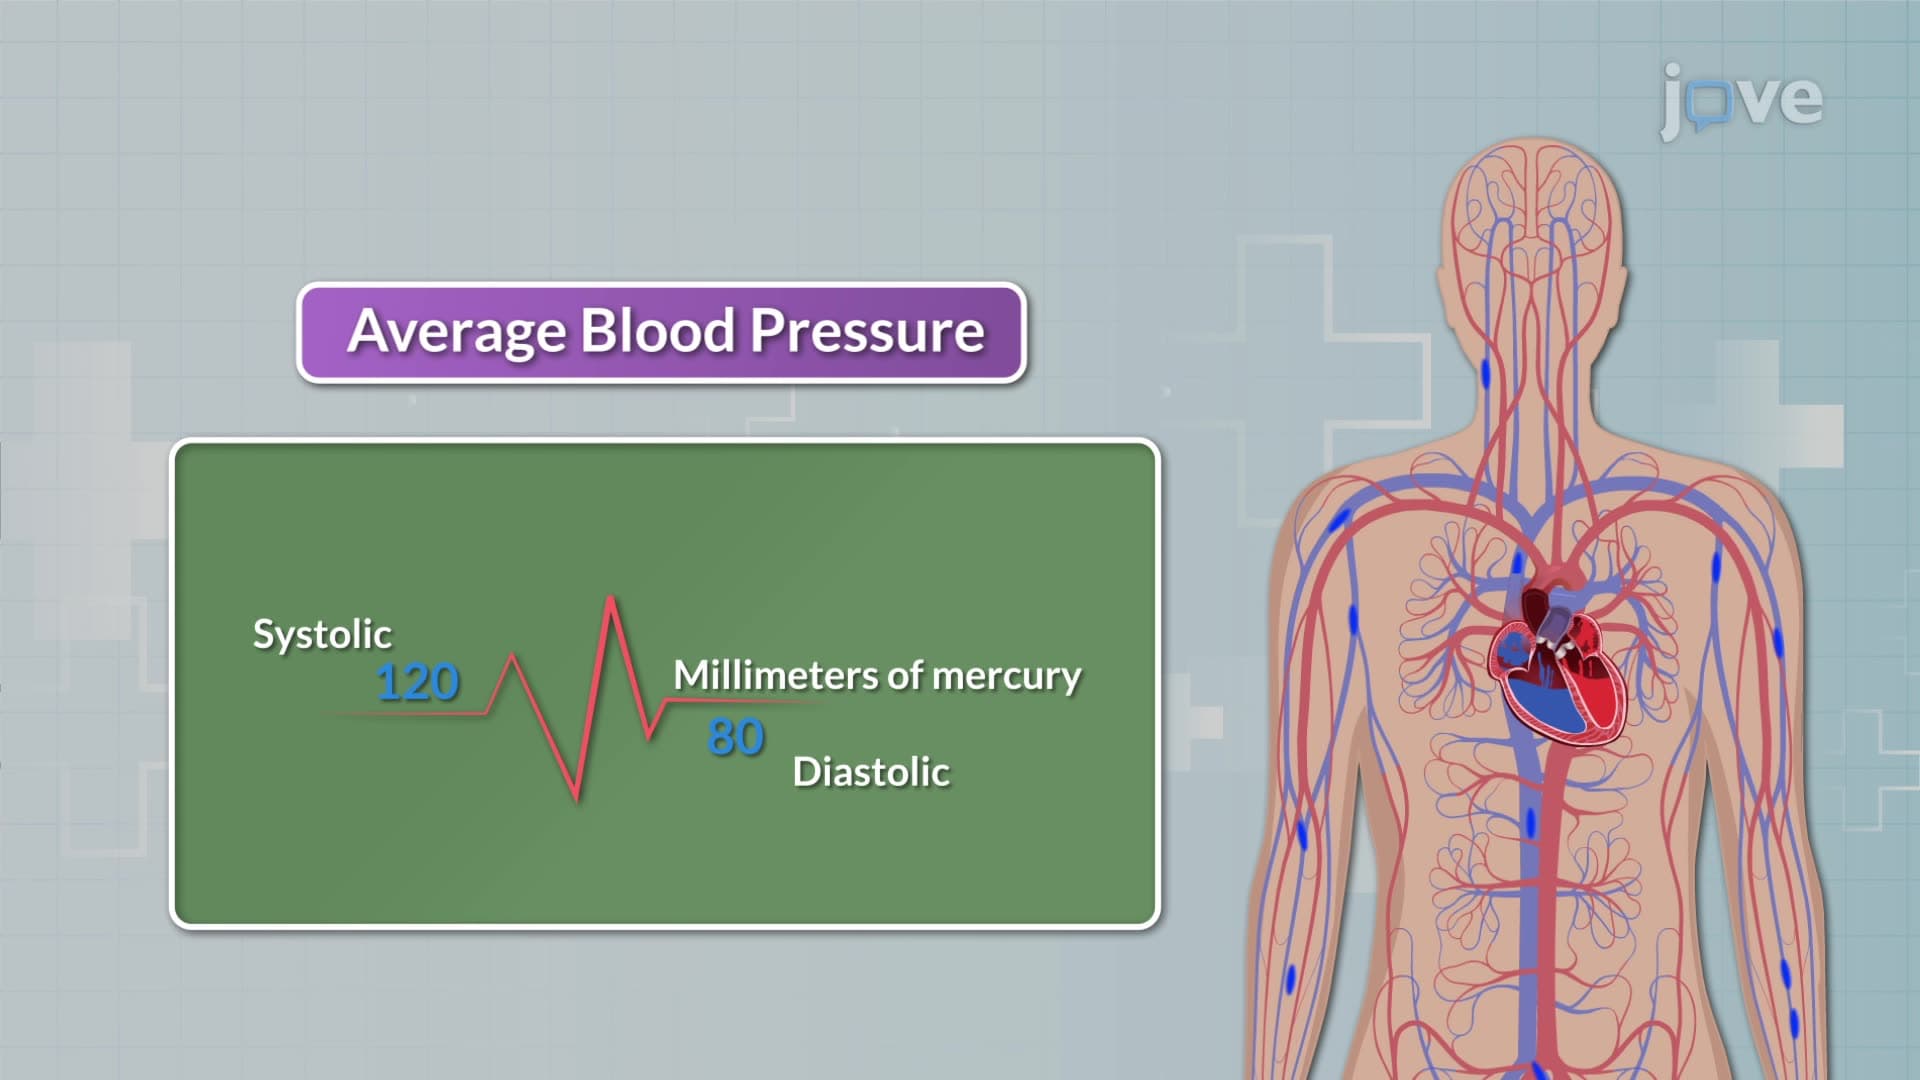
Blood Pressure
The average BP in an adult is typically around 120/80 mmHg (millimeters of mercury). In this measurement, the numerator (120) indicates the systolic pressure, which is the pressure in the arteries during the contraction of the heart's ventricles as blood is expelled. The denominator (80) represents the...
 01:17
Measurement of Blood Pressure
 01:28
Factors affecting Blood pressure
Physiological Factors:
 01:30
Alterations in Blood Pressure
Hypertension (High blood pressure)
Hypertension occurs when blood pressure readings consistently exceed the normal range. It is diagnosed when systolic blood pressure (the top number, indicating pressure while the heart...