Related Experiment Video
Updated: Jan 21, 2026


Glomerular Outgrowth as an Ex Vivo Assay to Analyze Pathways Involved in Parietal Epithelial Cell Activation
Published on: August 19, 2020
ANCA vasculitis presenting with acute interstitial nephritis without glomerular involvement
Callie Plafkin1, Weixiong Zhong1, Tripti Singh1
1University of Wisconsin School of Medicine and Public Health, Department of Medicine, Madison, WI, USA.

Abstract:
ANCA-associated vasculitis (AAV) with renal involvement typically causes pauci-immune glomerulonephritis. We present a case of acute interstitial nephritis (AIN) as the sole renal lesion without glomerulonephritis with myeloperoxidase (MPO) AAV. A 45-year-old female with history of Crohn's disease, gastroesophageal reflux disease (GERD) with Barrett's esophagus, pulmonary embolism, and polyarthralgias was evaluated in nephrology clinic in 2018. AIN without glomerulonephritis was first diagnosed in 2011 on renal biopsy. p-ANCA was positive with MPO titer of > 100 U/mL. Serum creatinine improved from 2.1 to 0.9 mg/dL with prednisone and azathioprine. Repeat biopsy in 2013 for worsening renal function showed AIN without glomerular involvement. Serum creatinine improved from 1.9 to 1.2 mg/dL with prednisone and cyclosporine. Crohn's disease was diagnosed in 2014. AIN was attributed to Crohn's, and cyclosporine was stopped in 2016. Adalimumab was started in 2016, without improvement in renal function or urine sediment. Attempt was made to switch proton pump inhibitor (PPI) to H2-blocker, but the latter was not tolerated. Repeat biopsy in 2/2018 showed AIN with severe fibrosis and tubular atrophy and glomerulosclerosis but no active glomerular disease. MPO titers remained high at 132 U/mL. Mycophenolic acid and prednisone were started without response, followed by rituximab for AAV-associated AIN. Serum creatinine worsened to 6.0 mg/dL in 9/2018, with plan to start peritoneal dialysis. AAV may present with isolated AIN without glomerular involvement. The rarity of this presentation may contribute to delay in appropriate management. Alternative explanations for AIN, such as Crohn's disease or PPI use should be considered with caution in the setting of high-titer ANCA positivity.

Related Concept Videos
 01:15
Glomerular Filtration
Components of the Filtration Membrane
The filtration process involves three key layers: the glomerular endothelial cells, the basement membrane, and the podocyte-formed filtration slits.
 01:28
Glomerular Filtration Rate and its Regulation
GFR regulation involves two primary intrinsic controls: the myogenic and tubuloglomerular feedback mechanisms.
The myogenic...
 01:26
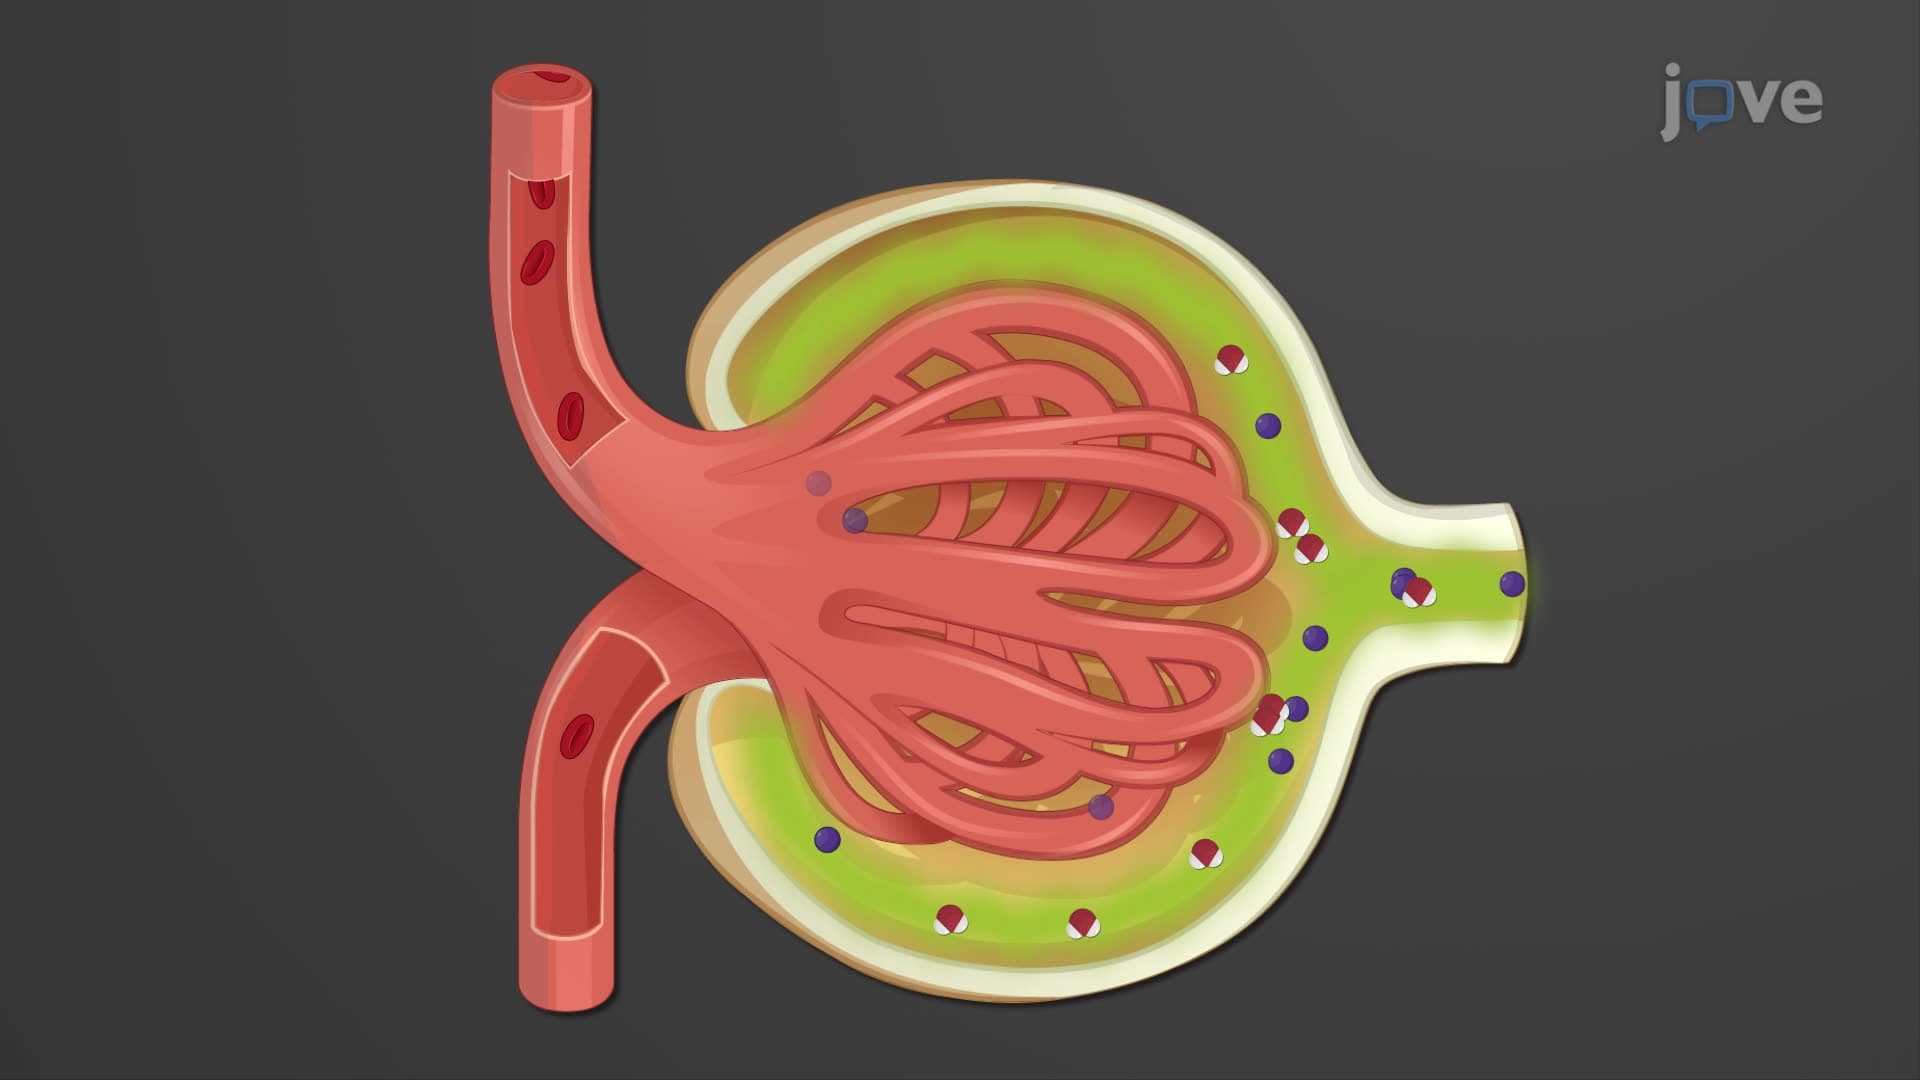
Glomerular Filtration: Net Filtration Pressure
GBHP, with an average value of 55 mmHg, promotes filtration by pushing water and solutes through the filtration membrane. This is balanced by two opposing forces: CHP, a "back pressure" exerted against the filtration membrane by fluid already in the capsular space and renal...
 01:26
Antigens Involved in Adaptive Immunity
Complete Antigens
Complete antigens possess both immunogenicity and...
 01:02
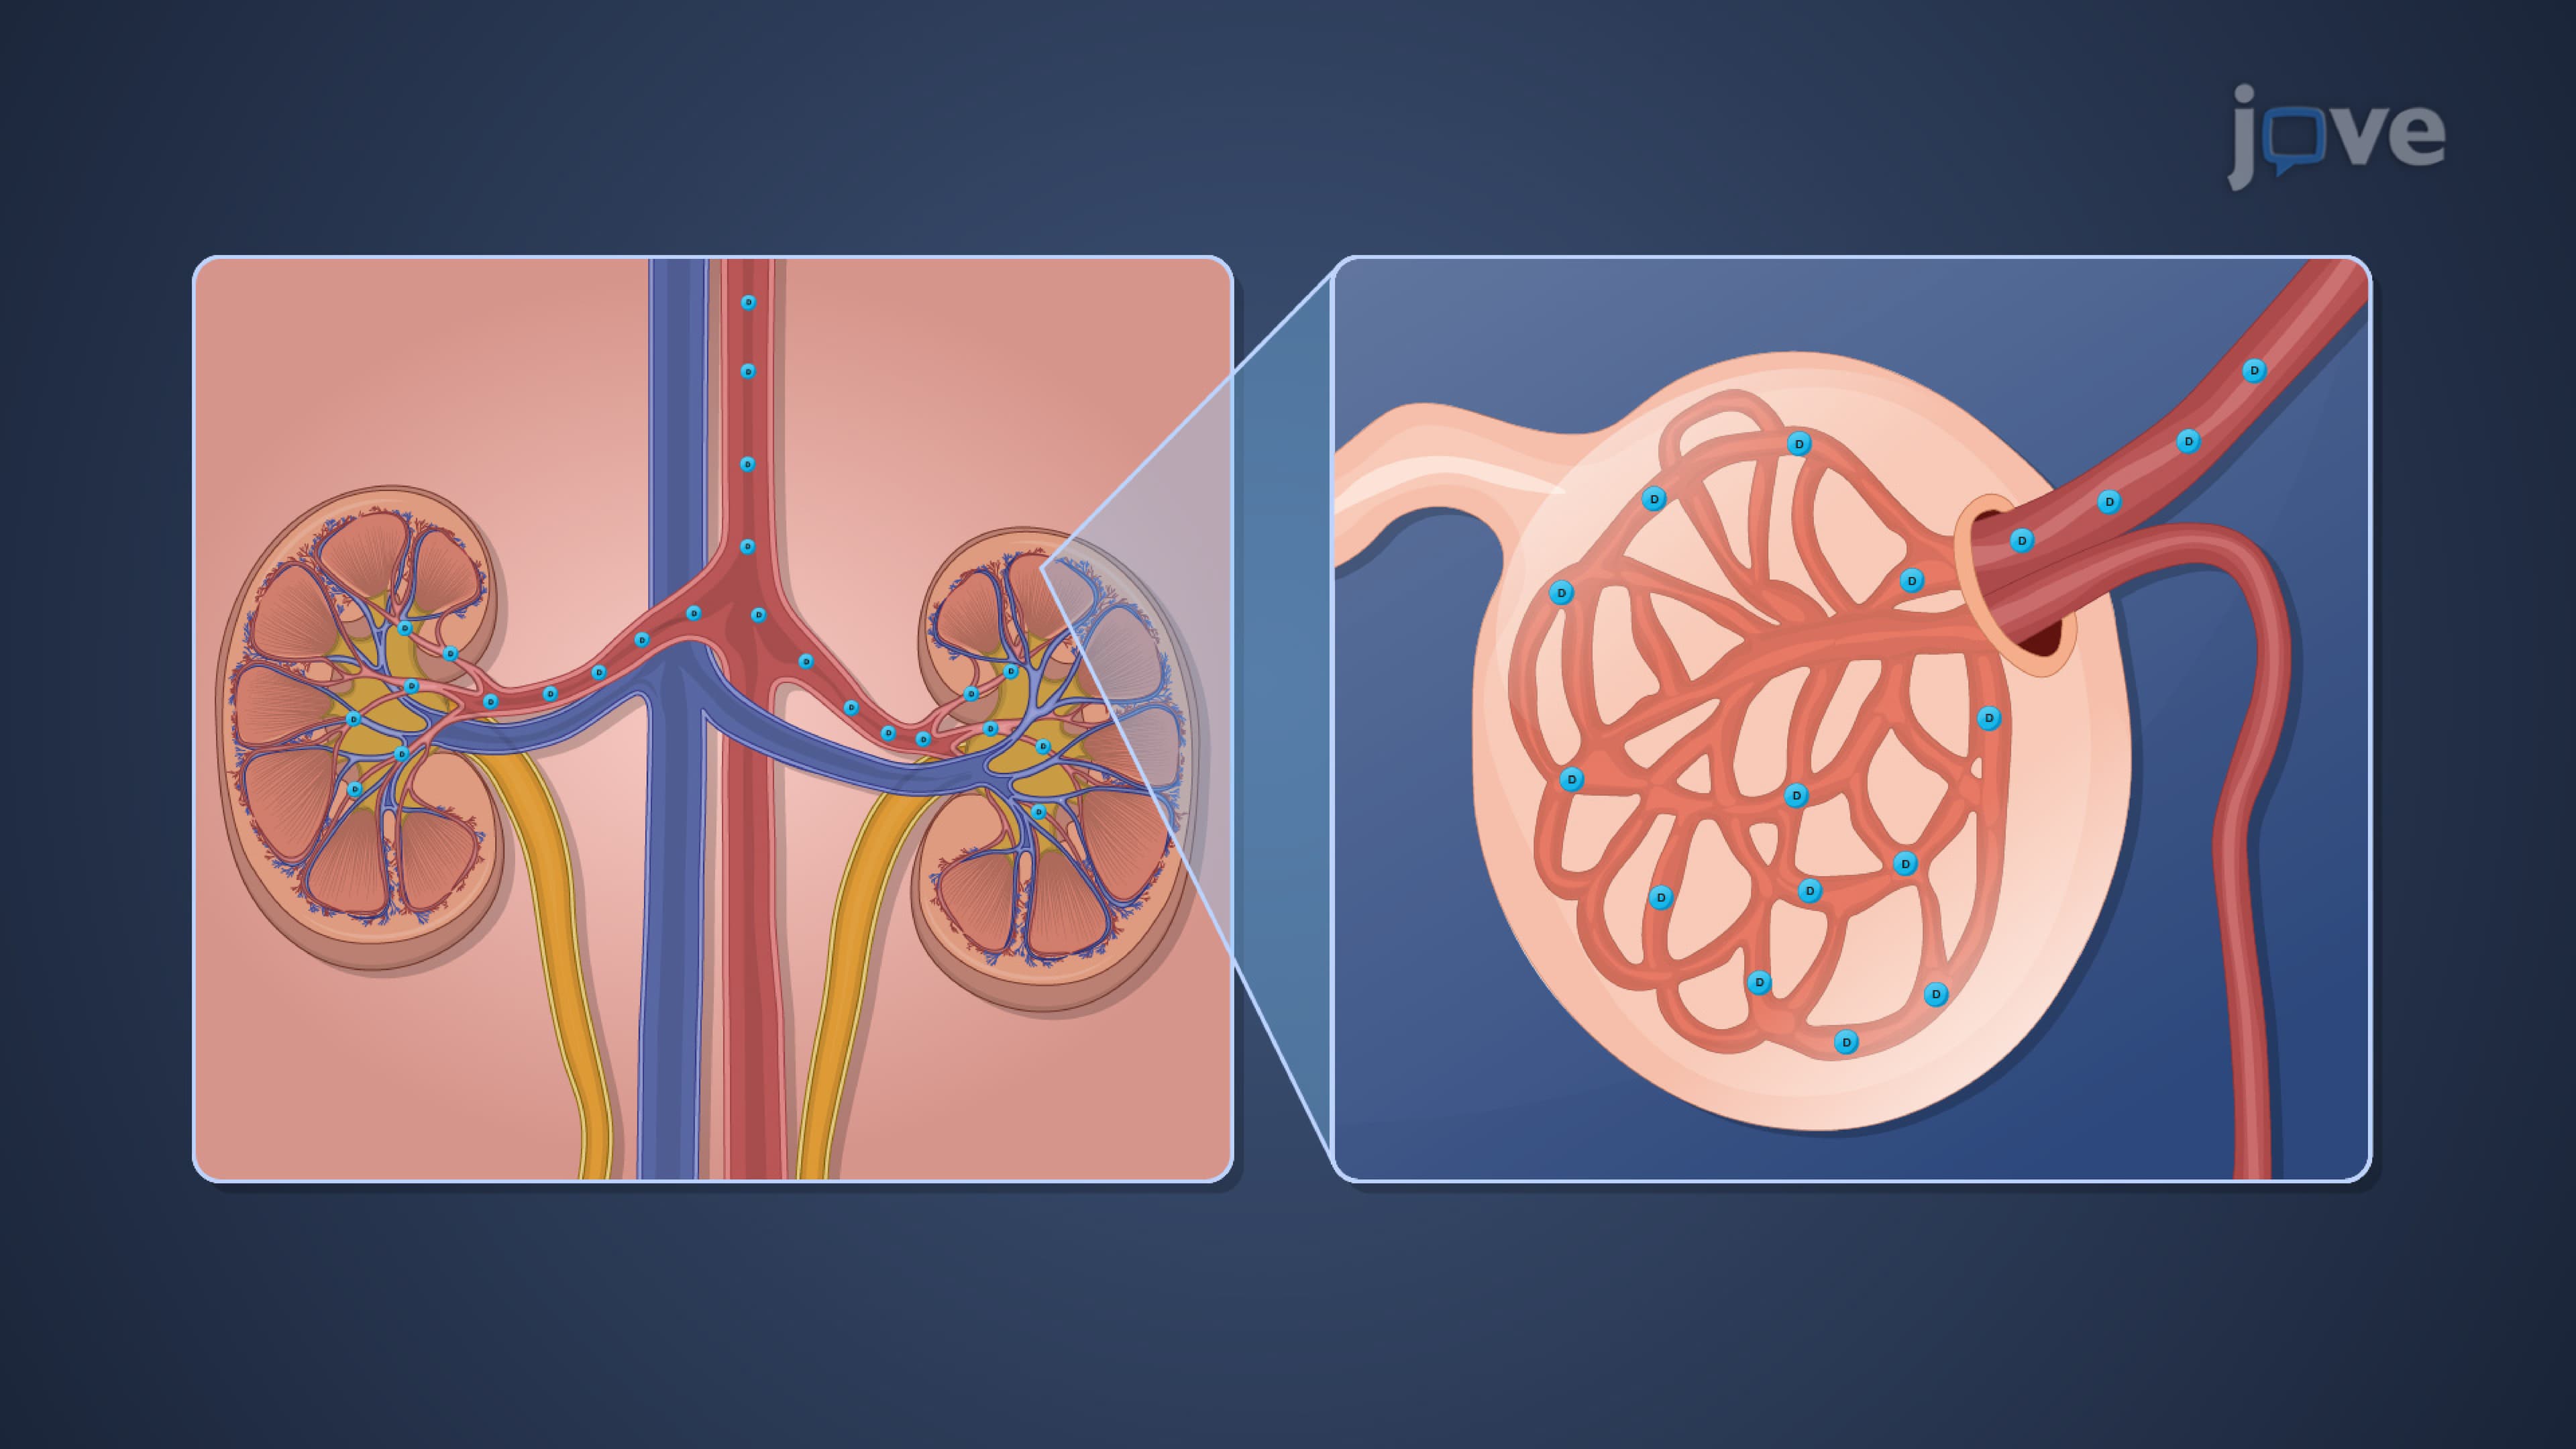
Renal Drug Excretion: Glomerular Filtration
Drugs gain access to the kidney via the renal artery, which progressively branches off into afferent arterioles....
 01:17
Drug Elimination by Renal Route: Glomerular Filtration