Related Experiment Video
Updated: Jan 21, 2026

Duodenal-Jejunal Bypass Surgery in Diet-Induced Obese Diabetic Mice
Published on: October 18, 2024
Recurrent intestinal ischemia following surgery for gastric and duodenal perforations: a case report
Takahiro Korai1, Katsunori Kouchi2, Ayako Takenouchi2
1Department of Pediatric Surgery, Tokyo Women's University Yachiyo Medical Center, 477-96 Ohwada-shinden, Yachiyo City, Chiba, 276-8524, Japan. koraitaka@gmail.com.

Insights
This case report details an extremely low birth weight infant who experienced simultaneous gastric and duodenal perforations, followed by necrotizing enterocolitis (NEC). Anticoagulation therapy proved effective in preventing short bowel syndrome.
Area of Science:
- Neonatal Medicine
- Gastroenterology
- Pediatric Surgery
Background:
- Extremely low birth weight (ELBW) infants face increased risks for gastrointestinal complications.
- Advances have improved survival rates for ELBW infants with necrotizing enterocolitis (NEC).
- Simultaneous gastric and duodenal perforations preceding NEC are previously unreported in neonates.
Purpose of the Study:
- To report a unique case of simultaneous gastric and duodenal perforations followed by NEC in an ELBW infant.
- To explore potential causative links between barotrauma, pulmonary venous thrombosis, and gastrointestinal perforations.
- To evaluate the efficacy of anticoagulation in preventing complications.
Main Methods:
- Case report of a female ELBW infant.
- Detailed clinical course including mechanical ventilation, barotrauma, and subsequent perforations.
- Initiation of heparin for anticoagulation and management of non-IgE-mediated gastrointestinal food allergies.
Main Results:
- The infant developed simultaneous gastric and duodenal perforations and later NEC.
- Pulmonary venous thrombosis (PVT) secondary to barotrauma was hypothesized as a trigger for perforations.
- Heparin anticoagulation was administered for suspected arterial thrombosis.
Conclusions:
- Anticoagulation with heparin may prevent short bowel syndrome in cases of acute arterial thrombosis.
- Surgical interventions for perforations may increase the risk of developing non-IgE-mediated gastrointestinal food allergies.
- The infant was stabilized at the time of reporting.
Background:
Extremely low birth weight (ELBW) is a risk factor for various gastrointestinal complications. In the recent decades, advances in medicine have increased the survival of ELBW infants with necrotizing enterocolitis (NEC). To our knowledge, there have been no reports of neonates or infants developing simultaneous gastric and duodenal perforations and later developing NEC. We report a case of an extremely low birth weight infant (ELBWI) who developed both gastric and duodenal perforations at the same time and developed NEC after operation for gastric and duodenal perforations.
Case Presentation:
The patient was a female infant with ELBW who developed both gastric and duodenal perforations at the same time and developed NEC after operation for gastric and duodenal perforations. After birth, endotracheal intubation was performed. However, barotrauma occurred during positive pressure ventilation, resulting in a large area of emphysema in the left lower lung field, leading to collapse of the left lung. This giant bulla may have compressed the pulmonary vein, possibly resulting in pulmonary venous thrombosis (PVT). This episode could have triggered simultaneous gastric and duodenal perforations. In addition, we hypothesized that PVT caused acute arterial ischemia, leading to the development of NEC. The infant was started on heparin for anticoagulation. Later, the infant developed non-immunoglobulin E (IgE)-mediated gastrointestinal food allergies (non-IgE-GI-FAs). The giant bulla associated with barotrauma might have caused PVT, resulting in arterial emboli and multiple simultaneous gastrointestinal perforations.
Conclusions:
Anticoagulation therapy with heparin for acute arterial thrombosis is effective for preventing the development of short bowel syndrome. Duodenal and intestinal surgery probably acted as risk factors for the subsequent development of non-IgE-GI-FAs. The infant had been stabilized at the time of writing this report.
Related Concept Videos
 01:22
Esophageal Perforation-I: Introduction
The location of esophageal perforation can vary, occurring anywhere along the esophagus....
 01:16
Gastric Motility
Peristaltic Waves and Chyme Formation
Upon food entry, the stomach initiates...
 01:23
Anatomy of the Intestines
Small Intestines
The small intestine is an ~7 meter-long tube with an inner diameter of just 2.5 cm. Since most nutrients are absorbed here, the inner lining of the...
 01:16
Gastric Emptying
 01:26
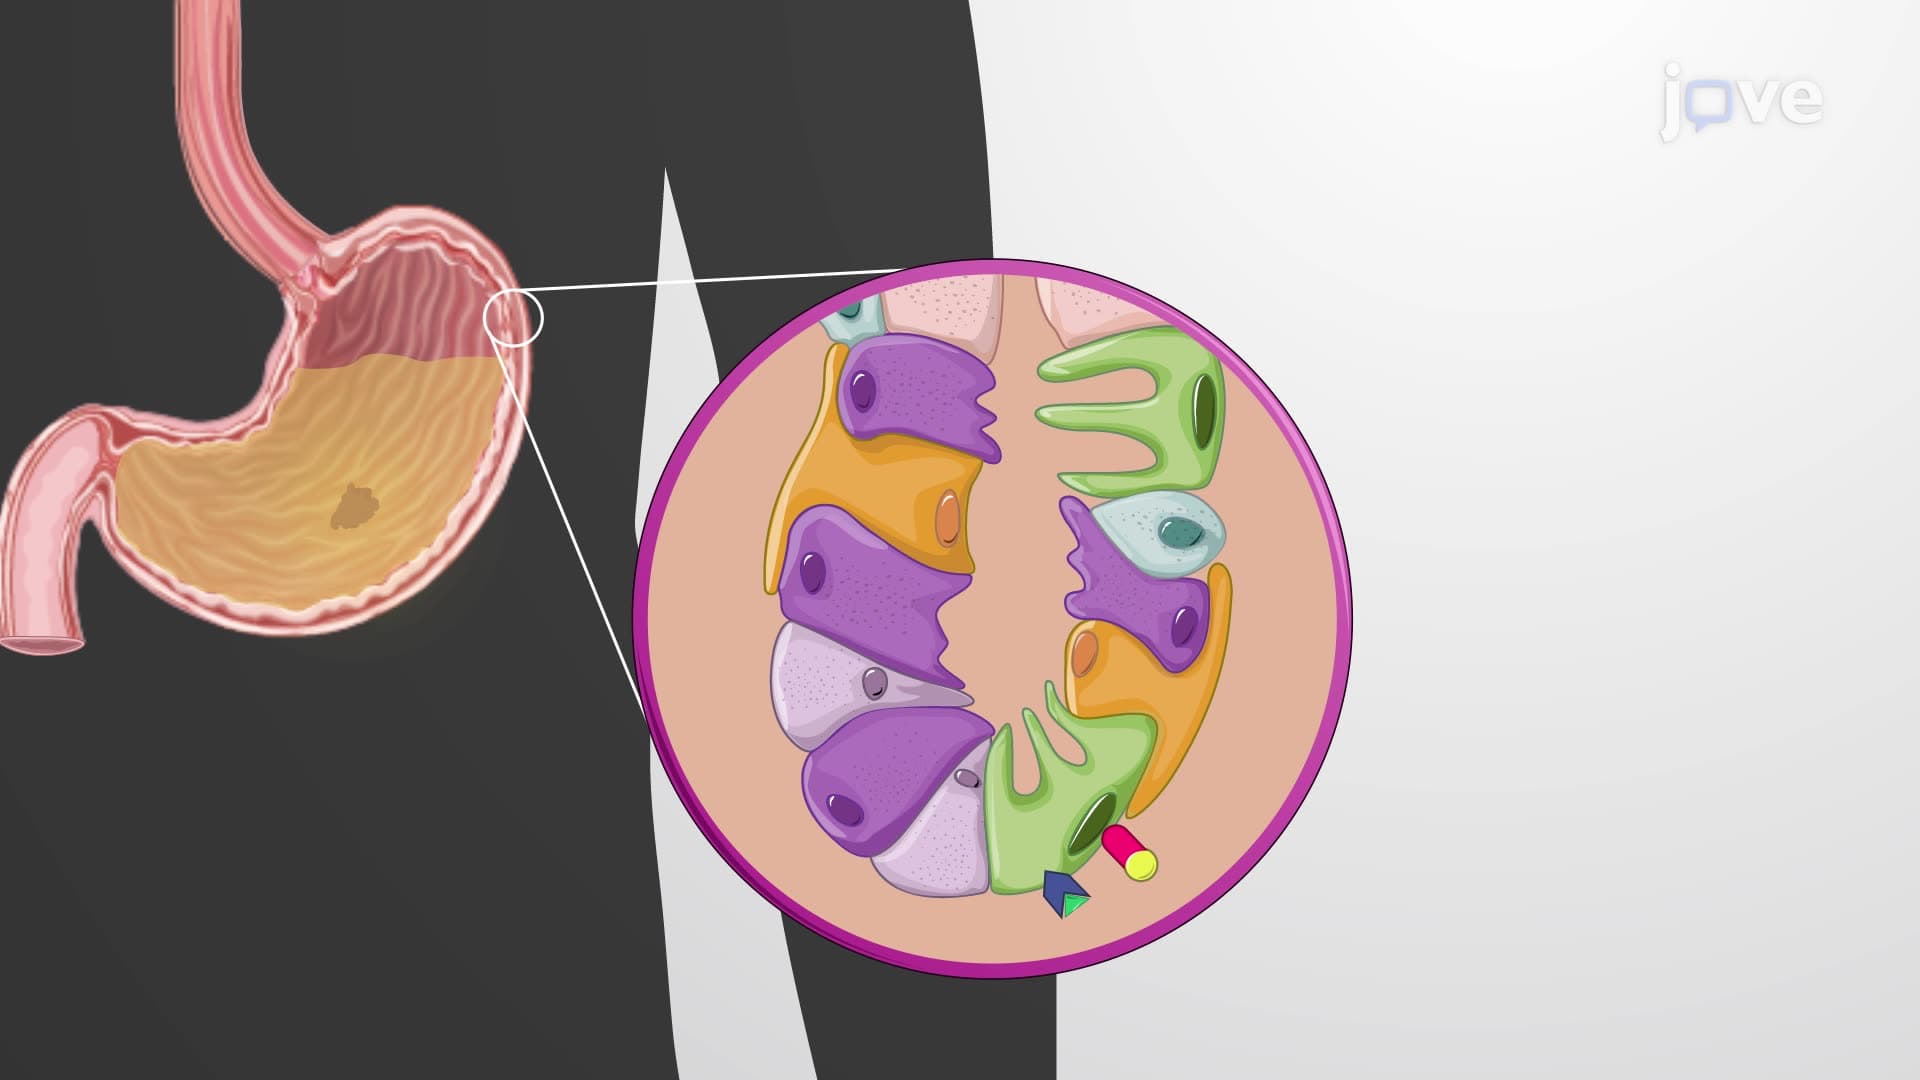
Gastric Phase of Digestion
When food enters the stomach, it stretches the stomach walls and activates stretch receptors. This triggers local reflexes of the enteric nervous system, mediated through the myenteric plexus. These...
 01:28
Esophageal Perforation-II: Clinical Manifestations and Management
Clinical Manifestations: