Related Experiment Video
Updated: Jan 21, 2026


Robot-assisted Total Mesorectal Excision and Lateral Pelvic Lymph Node Dissection for Locally Advanced Middle-low Rectal Cancer
Published on: February 12, 2022
MRI for Restaging Locally Advanced Rectal Cancer: Detailed Analysis of Discrepancies With the Pathologic Reference
Xiaoxuan Jia1, Yinli Zhang2, Yi Wang1
1Department of Radiology, Peking University People's Hospital, 11 Xizhimen S St, Xicheng District Beijing 100044, China.

Abstract:
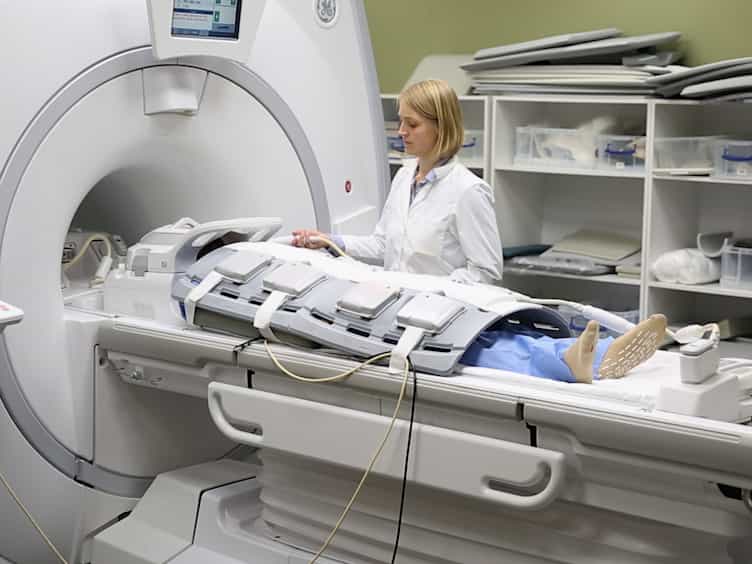
OBJECTIVE. The purpose of this study was to analyze causes of discrepancies between restaging MRI and pathologic findings in the assessment of morphologic indicators of tumor response in patients with rectal cancer who have undergone neoadjuvant treatment. MATERIALS AND METHODS. MRI and pathologic data from 57 consecutively registered patients who underwent neoadjuvant treatment and total mesorectal excision between August 2015 and July 2018 were retrospectively analyzed. The sensitivity and specificity of restaging MRI in determining tumor regression grade, T category, N category, circumferential resection margin, and extramural vascular invasion were calculated with pathologic results as the reference standard. One-by-one comparisons between MRI and pathologic findings were conducted to identify causes of discrepancies. RESULTS. The sensitivity of MRI in determining tumor regression grades 3-5 was 77.1%; T3 and T4 category, 100.0%; node-positive disease, 75.0%; circumferential resection margin, 87.5%; and extramural vascular invasion, 91.7%. The specificity values were 72.7%, 62.5%, 70.7%, 85.7%, and 64.4%. Overstaging was mainly caused by misinterpretation of fibrotic areas as residual tumor. Inflammatory cell infiltration could appear as high signal intensity in fibrotic areas on DW images, an appearance similar to that of residual tumor. Edematous mucosa and submucosa adjacent to the tumor and muscularis propria could also be mistaken for residual tumor because of their intermediate signal intensity on T2-weighted MR images. CONCLUSION. MRI was prone to overstaging of disease. Discrepancies between MRI and pathologic findings were mainly caused by misinterpretation of fibrosis. Inflammatory cell infiltration, pure mucin, edematous mucosa and submucosa adjacent to the tumor, and muscularis propria could also be misinterpreted as residual tumor.

Related Concept Videos
 02:45
Self-Discrepancy Theory
 01:29
Self-Discrepancy and Its Effects
 01:08
Sample Preparation for Analysis: Advanced Techniques
Acid digestion with strong acids is commonly used to dissolve inorganic materials that are insoluble (do not dissolve) in water. This method can be useful for...
 01:27
Assessing Body Temperature - Rectal
Follow these steps for rectal temperature assessment:
Step 1: Perform hand hygiene and don clean gloves to prevent cross-infection.
Step 2: Position the patient in a side-lying position to better visualize the rectal...
 02:37
Standard Enthalpy of Formation
 01:03
Inertial Frames of Reference