Related Experiment Video
Updated: Jan 20, 2026


Robotic Ablation of Atrial Fibrillation
Published on: May 29, 2015
Site Variation and Outcomes for Antithrombotic Therapy in Atrial Fibrillation Patients After Percutaneous Coronary
Christoph B Olivier1,2, Jun Fan3, Mariam Askari3
1Department of Medicine, Stanford Center for Clinical Research (C.B.O., K.W.M.), Stanford University School of Medicine, CA.

Insights
Patients with atrial fibrillation (AF) undergoing percutaneous coronary intervention (PCI) showed significant variation in antithrombotic therapy. Oral anticoagulation plus platelet inhibition (OAC+PI) was underutilized but associated with better outcomes, suggesting a need for standardized strategies.
Area of Science:
- Cardiology
- Pharmacology
- Health Services Research
Background:
- Patients with atrial fibrillation (AF) undergoing percutaneous coronary intervention (PCI) require complex antithrombotic regimens.
- Current optimal antithrombotic strategies for AF patients post-PCI are debated, leading to treatment variation.
- Site-level variations in antithrombotic prescribing patterns post-PCI in AF patients are not well characterized.
Purpose of the Study:
- To analyze site-level variations in antithrombotic therapy prescribed to AF patients after PCI.
- To determine the association between different antithrombotic strategies and patient outcomes.
- To identify potential areas for improving treatment consistency and efficacy.
Main Methods:
- Retrospective analysis of the TREAT-AF study data from the Veterans Health Administration (2004-2015).
- Identification of nonvalvular AF patients who underwent PCI and received a P2Y12-antagonist.
- Grouping patients into oral anticoagulation plus platelet inhibition (OAC+PI) or platelet inhibition only, assessing outcomes at 1 year post-PCI using Cox regression.
Main Results:
- Out of 4042 AF patients undergoing PCI, 47% received OAC+PI and 53% received platelet inhibition only.
- Significant site-level variation in OAC+PI use was observed, ranging from 19% to 66%.
- OAC+PI prescription was associated with a reduced risk of combined death, myocardial infarction, stroke, or major bleeding (aHR, 0.85; P=0.033).
Conclusions:
- Substantial site variation exists in 30-day post-PCI antithrombotic use for AF patients.
- Anticoagulation appeared underutilized but linked to improved patient outcomes.
- Standardizing OAC+PI use and minimizing prescribing variations may enhance outcomes for AF patients post-PCI.
Background:
Patients with atrial fibrillation (AF) treated with percutaneous coronary intervention (PCI) require multiple antithrombotic therapies. The optimal strategy is debated suggesting increased treatment variation. This study sought to characterize site-level variation in antithrombotic therapies in AF patients after PCI and determine the association with outcomes.
Methods:
Using the retrospective TREAT-AF study (The Retrospective Evaluation and Assessment of Therapies in AF) from the Veterans Health Administration, patients with newly diagnosed, nonvalvular AF between 2004 and 2015 followed by a PCI with a P2Y12-antagonist prescription were identified. Patients were grouped according to the therapy dispensed 7 days before until 30 days after the PCI: oral anticoagulation plus platelet inhibition (OAC+PI) or platelet inhibition only. A combined outcome of death, myocardial infarction, stroke, or major bleeding was assessed 1 year after PCI and Cox regression was performed to estimate hazard ratios.
Results:
Of 230 762 patients with newly diagnosed AF, 4042 (1.8%) underwent PCI and received a P2Y12-antagonist during the observation period (age, 67±9 years; CHA2DS2-VASc, 2.7±1.7; HAS-BLED, 2.6±1.2). Among these, 47% were prescribed OAC+PI, and 53% platelet inhibition only 7 days before until 30 days after the PCI. Across 63 sites, the use of OAC+PI ranged from 19% to 66%. Prescription of OAC+PI was independently associated with a reduction in the combined outcome of death, myocardial infarction, stroke, or major bleeding compared with platelet inhibition only (adjusted hazard ratio, 0.85; 95% CI, 0.73-0.99; P=0.033).
Conclusions:
In patients with established AF undergoing PCI, the use of OAC+PI varied substantially across sites in the 30 days post-PCI. Anticoagulation appeared to be underutilized but was associated with improved outcomes. Strategies to promote OAC+PI and minimize site variation may be useful, particularly in light of recent randomized trials.
More Related Videos


Related Concept Videos
 03:03
Amyloid Fibrils
Amyloid deposits were observed as early as 1639 in the liver and the spleen. In 1854, Rudolph Virchow performed iodine staining,...
03:03Amyloid Fibrils
 02:53
Conservative Site-specific Recombination and Phase Variation
The recognition sites for Cre recombinase called LoxP...
 01:14
What is Variation?
The range, standard deviation, standard error, and variance are the different measures of variation.
Range: The range is the difference between its maximum and...
 01:19
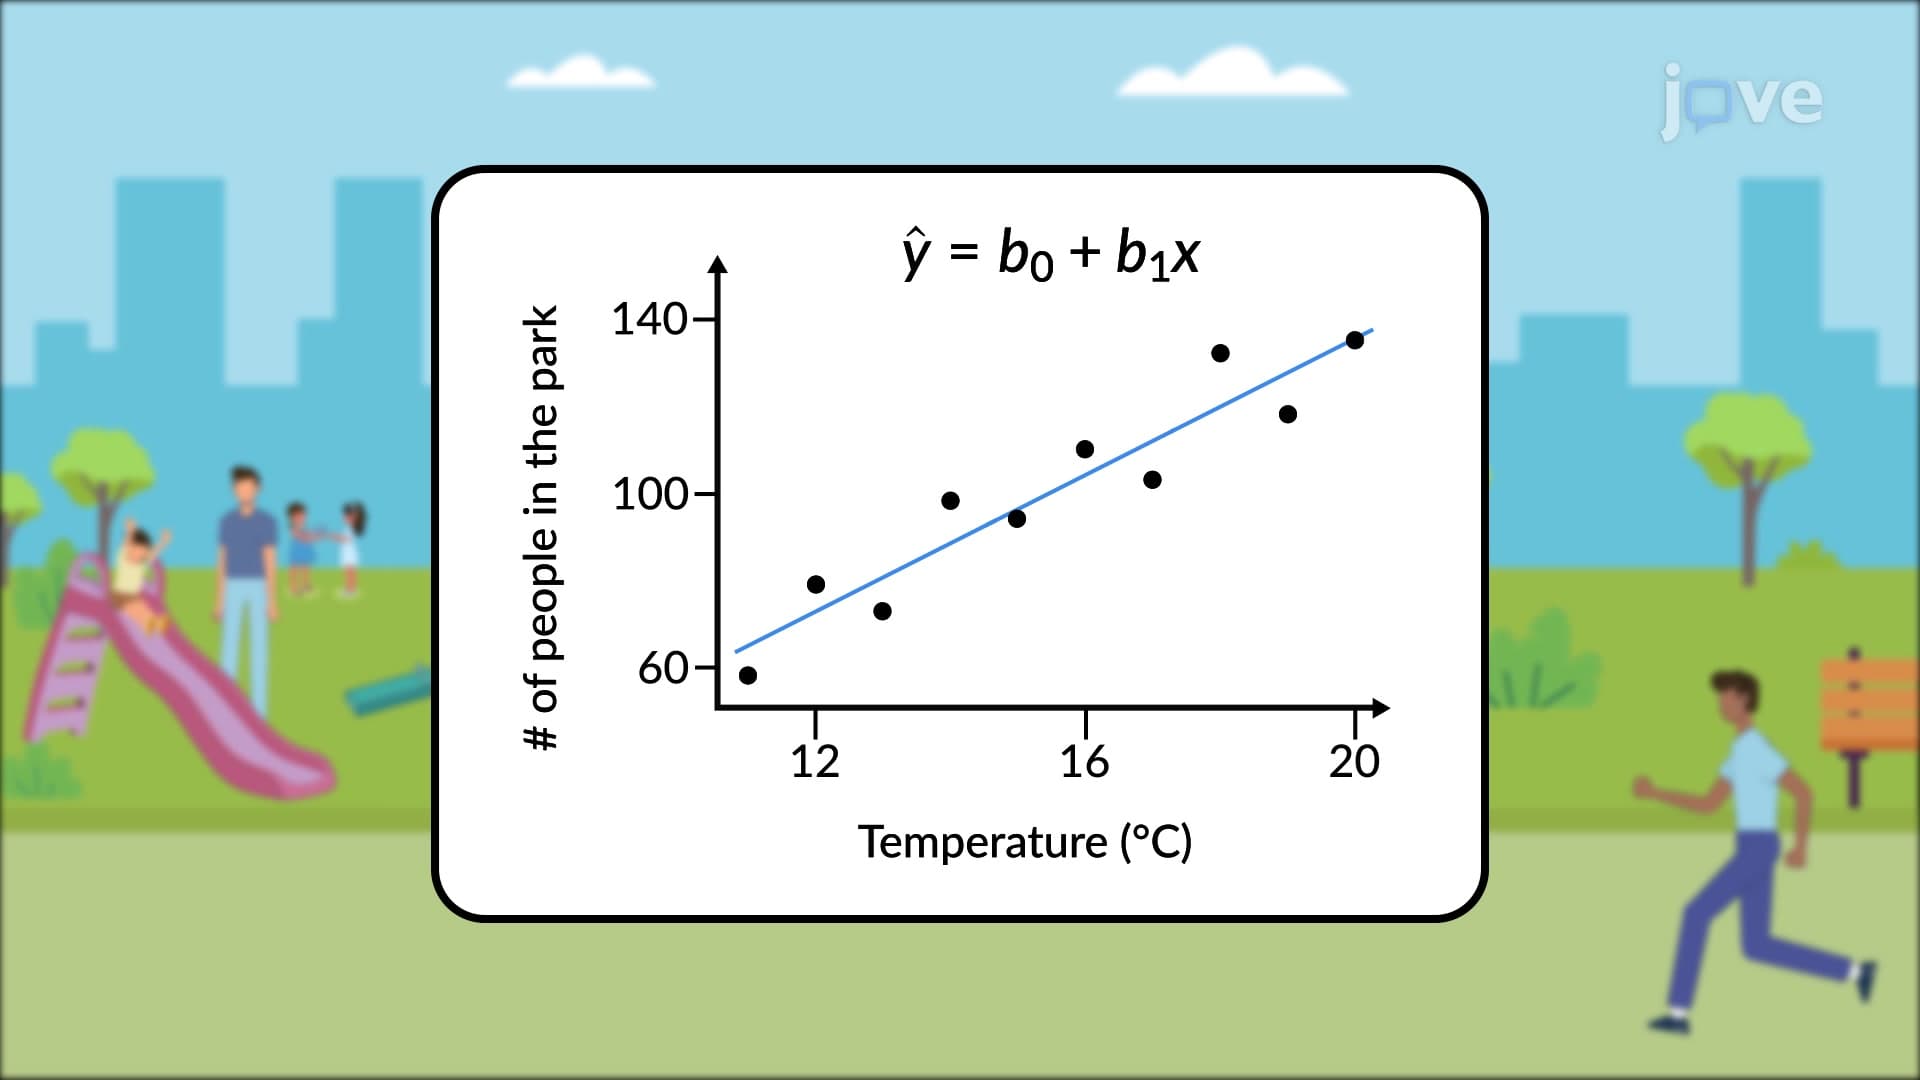
Variation
When independent and dependent variables are plotted on a scatter plot, the slope of a line is a value that describes the rate of change between the two...
 01:03
Nursing Interventions I: Taxonomy of Nursing Interventions
A nursing intervention is a treatment or action based on scientific concepts and knowledge from the nursing, behavioral, and physical sciences. Identifying and prioritizing nursing interventions based on the desired outcome...