Related Experiment Video
Updated: Jan 20, 2026


Assessment of Gastric Emptying in Non-obese Diabetic Mice Using a [13C]-octanoic Acid Breath Test
Published on: March 23, 2013
Rapid gastric emptying in diabetes mellitus: Pathophysiology and clinical importance
Raj K Goyal1, Vivian Cristofaro1, Maryrose P Sullivan1
1Departments of Medicine and Surgery, VA Boston Healthcare System and Harvard Medical School, Boston, MA, United States of America.

Abstract:
Although slow gastric emptying (gastroparesis) is a well-known complication of chronic hyperglycemia in diabetes mellitus (DM), it recently has become clear that rapid gastric emptying also is a frequent and important diabetic complication. In contrast, acute hyperglycemia causes slow gastric emptying, and acute hypoglycemia causes rapid gastric emptying. Rapid gastric emptying is frequent in T2DM; however, it may also occur in T1DM, particularly in the early stages of the disease, but may persist even into late stages. Recent studies suggest that usually, the stomach restricts the emptying of nutrients to 1-4 kcals/min. This restriction is due to the action of the gastric 'braking' hormones such as GLP-1, leptin, and amylin acting via the gastric inhibitory vagal motor circuit (GIVMC). Disruption of this braking system leads to rapid gastric emptying. Acute hyperglycemia also slows gastric emptying by stimulating the GIVMC, while acute hypoglycemia causes rapid gastric emptying by stimulating the gastric excitatory vagal motor circuit (GEVMC). In contrast, chronic hyperglycemia causes rapid gastric emptying by inducing oxidative stress in the stomach wall that disrupts inhibitory neuromuscular transmission and increases the contractility of the smooth muscle, while chronic hyperglycemia may also cause slow gastric emptying via severe inflammatory stress caused by proinflammatory macrophages and reduce contractility of the smooth muscle. There is a bidirectional relationship between blood glucose and gastric emptying. Thus, rapid gastric emptying may lead to a sizeable postprandial spike, and slow gastric emptying may blunt it. Postprandial hyperglycemia is involved in the development, progression, and complications of DM. Correction of fast gastric emptying involves agents that activate GIVMC and the use of gastric 'braking' hormones or their analogs. Recognition and treatment of rapid gastric emptying may contribute to better management of postprandial hyperglycemia and prevention of some diabetic complications.


Related Concept Videos
 01:16
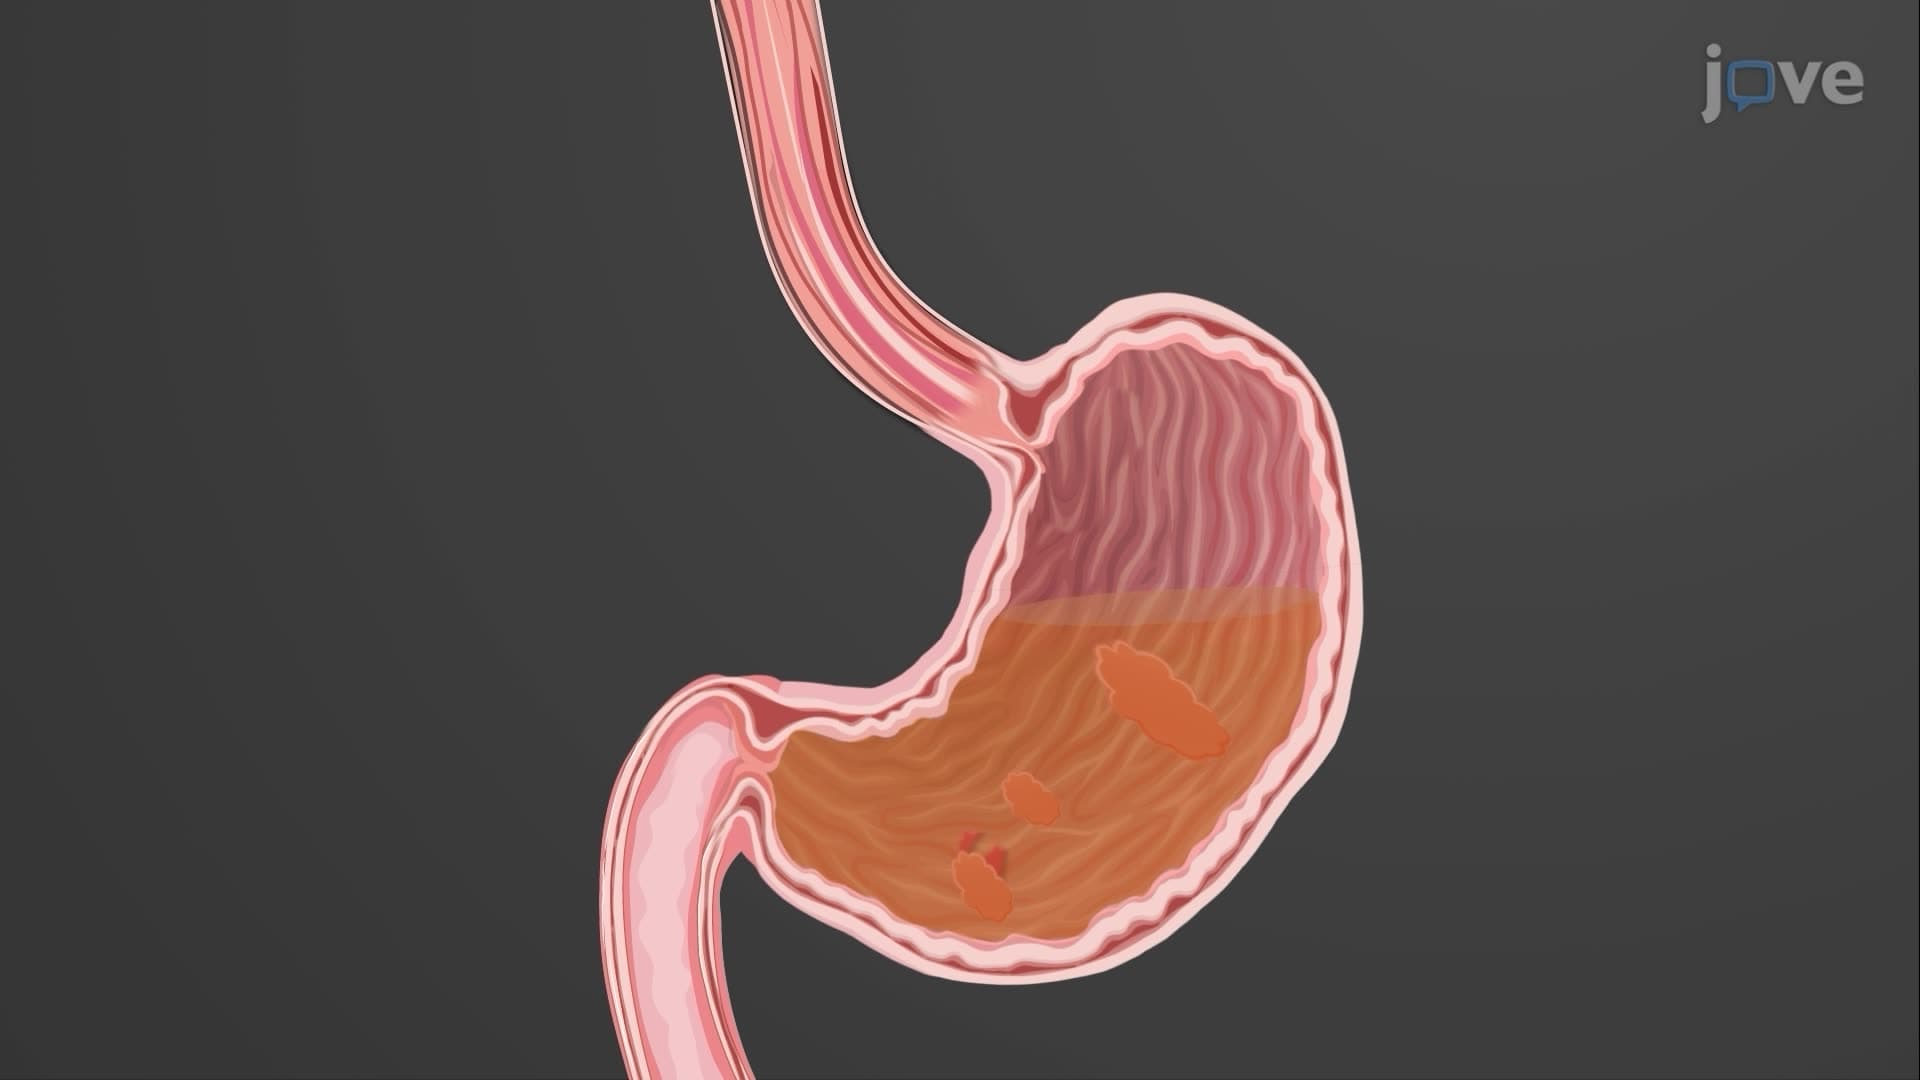
Gastric Emptying
 01:20
Pathophysiology of Diabetes
Type 1 diabetes is characterized by autoimmune-mediated destruction of pancreatic β cells, with environmental factors potentially triggering this process in genetically susceptible individuals. Despite many not having a family history, certain genes increase susceptibility,...
 01:22
Diabetes Mellitus: Type 2 and Gestational
 01:22
Diabetes Mellitus: Overview and Type I Subtype
Type 1 diabetes is an autoimmune disease in which the immune system mistakenly attacks and destroys the insulin-producing beta cells in the pancreas. As a result, the body is unable to produce sufficient insulin, and individuals with...
 01:19
Acute Coronary Syndrome II: Pathophysiology and Clinical Manifestations
 01:26
Urinary Tract Calculi II: Pathophysiology and Clinical Manifestations