Early enteral feeding in preterm infants
Related Experiment Video
Updated: Jan 20, 2026
Transcutaneous Microcirculatory Imaging in Preterm Neonates
Published on: December 31, 2015
T'ng Chang Kwok1, Jon Dorling2, Chris Gale3
1Division of Academic Child Health, University of Nottingham, E floor, East Block, Queens Medical Centre, Nottingham NG7 2UH, United Kingdom.

Insights
Early enteral feeding within 48 hours and progressive feeding before day 4 is safe for stable preterm infants. However, optimal feeding advancement for high-risk infants requires further research.
Area of Science:
- Neonatalogy
- Pediatric Gastroenterology
- Clinical Nutrition
Background:
- Enteral feeding practices for preterm infants vary significantly.
- Early enteral feeding is a modifiable risk factor for necrotising enterocolitis (NEC) and late onset sepsis (LOS).
- High-quality evidence is emerging to guide feeding protocols in preterm neonates.
Purpose of the Study:
- To review current evidence on early enteral feeding in preterm infants.
- To assess the safety and efficacy of different feeding advancement strategies.
- To identify knowledge gaps in feeding high-risk preterm populations.
Main Methods:
- Meta-analyses of randomized controlled trials (RCTs) were examined.
- Data from trials involving clinically stable very preterm and very low birthweight (VLBW) infants were synthesized.
- Limited data on high-risk infants (e.g., small for gestational age, absent/reversed end diastolic flow velocity) were considered.
Main Results:
- Early trophic feeding (within 48h) and progressive feeding (before day 4 at >24 ml/kg/day) are safe for stable VLBW infants, without increased mortality or NEC.
- Evidence suggests progressive enteral feeding initiated within the first 4 days is safe for high-risk preterm infants.
- There is limited evidence comparing bolus versus continuous gavage feeding in stable preterm infants.
- Many trials are unblinded, increasing bias risk for subjective outcomes like NEC and LOS.
Conclusions:
- Current evidence supports early and progressive enteral feeding in stable preterm infants.
- Further research is needed to establish optimal feeding advancement protocols for high-risk preterm infants.
- Future trials should prioritize objective outcomes and blinded assessments to minimize bias.
Abstract:
Early enteral feeding is a potentially modifiable risk factor for necrotising enterocolitis (NEC) and late onset sepsis (LOS), however enteral feeding practices for preterm infants are highly variable. High-quality evidence is increasingly available to guide early feeding in preterm infants. Meta-analyses of randomised trials indicate that early trophic feeding within 48 h after birth and introduction of progressive enteral feeding before 4 days of life at an advancement rate above 24 ml/kg/day can be achieved in clinically stable very preterm and very low birthweight (VLBW) infants, without higher mortality or incidence of NEC. This finding may not be generalisable to high risk infants such as those born small for gestational age (SGA) or following absent/reversed end diastolic flow velocity (AREDFV) detected antenatally on placental Doppler studies, due to the small number of such infants in existing trials. Trials targeting such high-risk preterm infants have demonstrated that progressive enteral feeding started in the first 4 days is safe and does not lead to higher NEC or mortality; however, there is a paucity of data to guide feeding advancement in such infants. There is little trial evidence to support bolus or continuous gavage feeding as being superior in clinically stable preterm infants. Trials that examine enteral feeding are commonly unblinded for technical and practical reasons, which increases the risk of bias in such trials, specifically when considering potentially subjective outcome such as NEC and LOS; future clinical trials should focus on objective, primary outcome measures such as all-cause mortality, long term growth and neurodevelopment. Alternatively, important short-term outcomes such as NEC could be used with blinded assessment.
More Related Videos

Related Concept Videos
 01:26
Enteral Nutrition I: Orogastric and Nasogastric Feeding
Orogastric (OG) and nasogastric (NG) feeding are two standard methods used for enteral nutrition. Enteral nutrition is often preferred over...
 01:15
Enteral Nutrition II: Nasointestinal and Gastrostomy Feeding
Nasointestinal Feeding
Nasointestinal feeding involves placing a tube...
 01:18
Drug Delivery: Enteral Route
 01:18
Routes of Drug Administration: Enteral
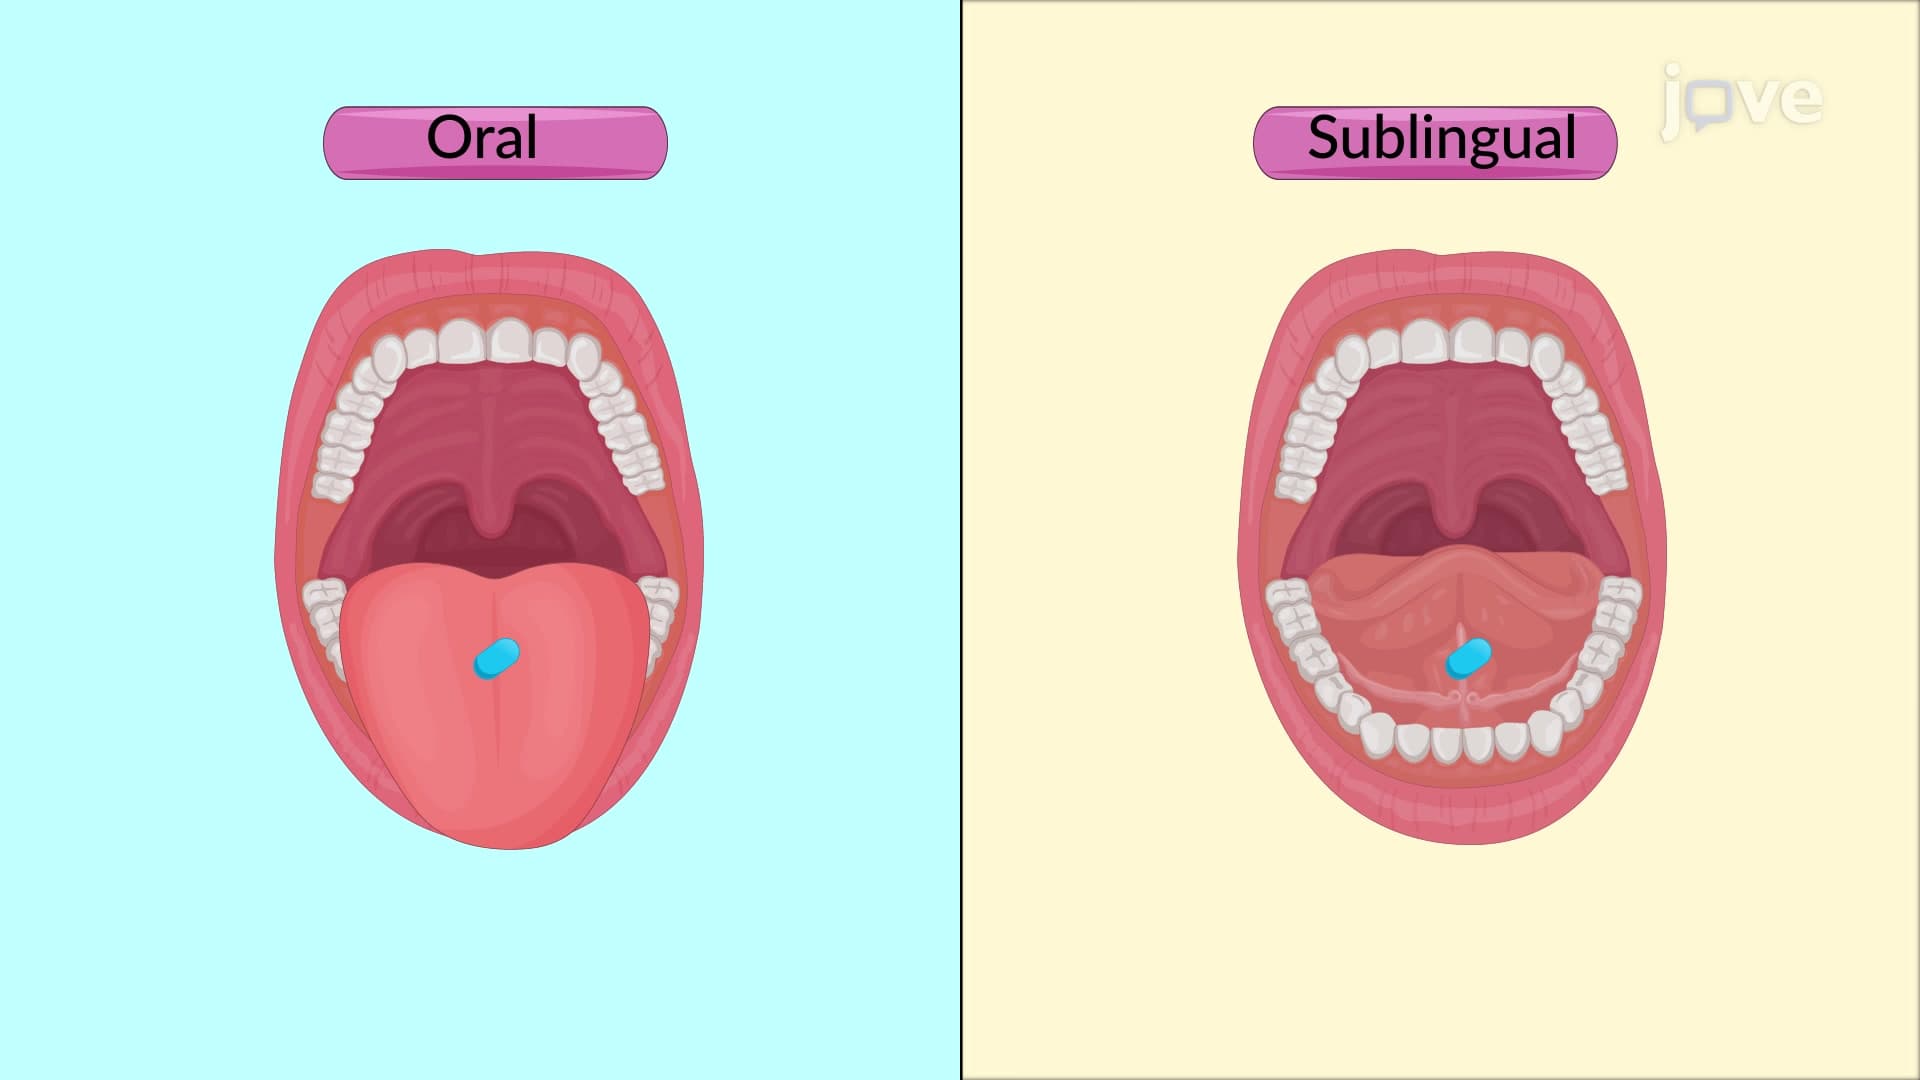
Enteral administration involves drug administration via the mouth in two ways: orally or sublingually.
Unlike sublingually drugs, drugs that are taken orally pass through the gastrointestinal (GI) tract and get metabolized by the liver. Once metabolized, the drug is absorbed into the systemic circulation, reaching different body parts via the bloodstream. However, while passing through the stomach,...
 01:05
Physiology of Enteric Nervous System and Gut Health
 01:11
Enteric Nervous System: Regulation of GI Motor Activity
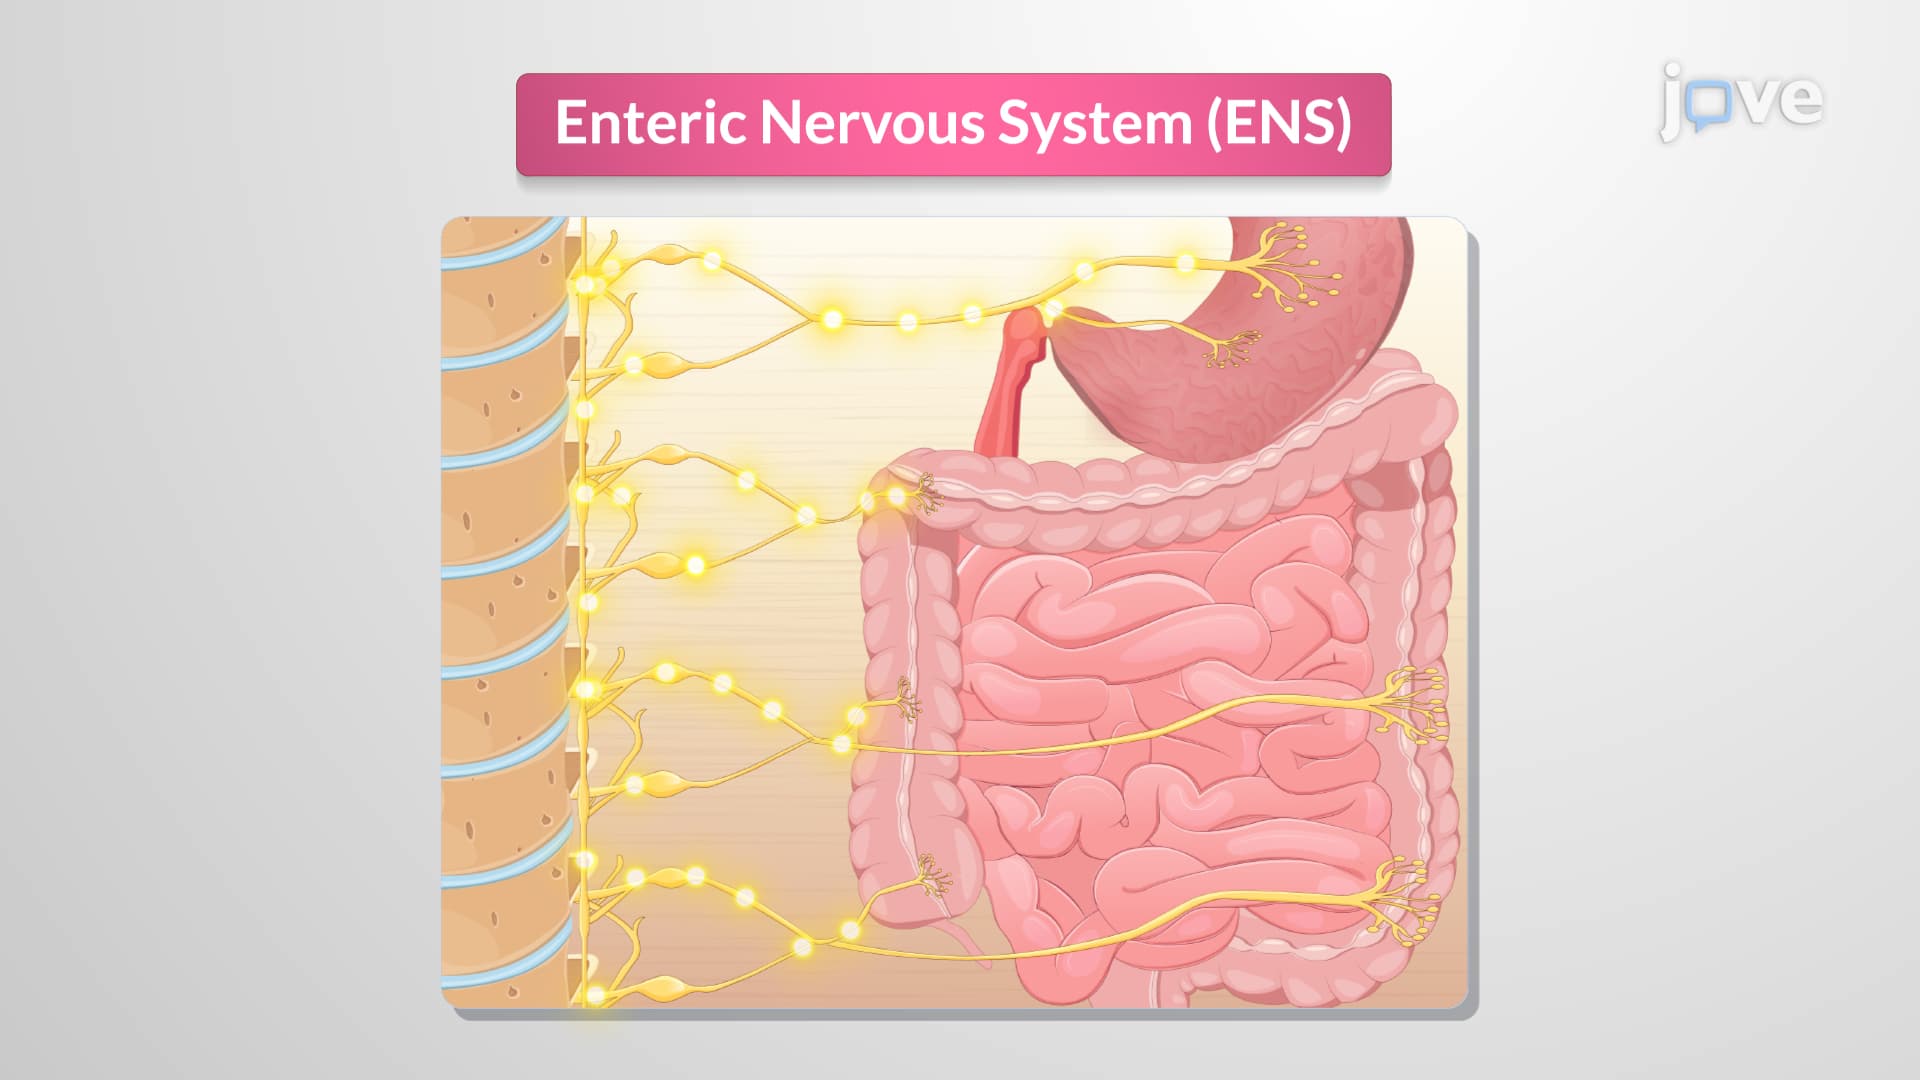
During periods of fasting, the ENS initiates the migrating myoelectric complex, a...