Related Experiment Video
Updated: Jan 19, 2026


ADSC-sheet Transplantation to Prevent Stricture after Extended Esophageal Endoscopic Submucosal Dissection
Published on: February 10, 2017
Endoscopic hemostasis followed by preventive transarterial embolization in high-risk patients with bleeding peptic
Aleksejs Kaminskis1, Patricija Ivanova1, Aina Kratovska1
11Riga East University Hospital, University of Latvia, Riga, Latvia.

Insights
Preventive transarterial embolization (P-TAE) significantly reduces rebleeding in high-risk peptic ulcer patients after endoscopic hemostasis. This safe procedure also lowers surgical intervention needs and fresh frozen plasma transfusions, improving outcomes.
Area of Science:
- Gastroenterology
- Interventional Radiology
- Vascular Surgery
Background:
- Peptic ulcer disease is a leading cause of non-variceal upper gastrointestinal bleeding (UGIB), with high mortality and rebleeding rates.
- Patients with Forrest IA, IB, or IIA bleeding ulcers and high rebleeding risk often require additional therapies post-endoscopic hemostasis.
- Preventive transarterial embolization (P-TAE) was introduced in 2014 to manage such high-risk cases.
Purpose of the Study:
- To assess the intermediate outcomes of P-TAE following primary endoscopic hemostasis in patients with severe comorbidities and high rebleeding risk.
- To evaluate the efficacy and safety of P-TAE in reducing rebleeding and complications in high-risk UGIB patients.
Main Methods:
- A prospective study included 399 high-risk patients (Forrest IA, IB, IIA, Rockall score ≥ 5) from 2014-2018.
- Patients were divided into two groups: P-TAE (n=58) and endoscopy alone (EA, n=341).
- P-TAE involved flow-reducing embolization of the left gastric or gastroduodenal artery; outcomes analyzed included rebleeding, surgery, transfusions, and mortality.
Main Results:
- P-TAE group showed a significantly lower rebleeding rate (3.4% vs. 16.2%, p=0.005).
- Surgical intervention rates were lower in the P-TAE group (10.3% vs. 20.6%, p=0.065).
- P-TAE patients required less fresh frozen plasma (FFP) (1.3 units vs. 2.6 units, p=0.0001); mortality was similar (5.7% vs. 8.5%, p=0.417).
Conclusions:
- P-TAE is a feasible and safe adjunctive therapy for high-risk bleeding peptic ulcers post-endoscopic hemostasis.
- P-TAE effectively reduces rebleeding rates and the need for surgical intervention.
- This procedure offers a valuable option for managing complex UGIB cases with persistent high rebleeding risk.
Background:
Upper gastrointestinal bleeding (UGIB) due to peptic ulcer disease is one of the leading causes of death in patients with non-variceal bleeding, resulting in up to 10% mortality rate, and the patient group at high risk of rebleeding (Forrest IA, IB, and IIA) often requires additional therapy after endoscopic hemostasis. Preventive transarterial embolization (P-TAE) after endoscopic hemostasis was introduced in our institution in 2014. The aim of the study is an assessment of the intermediate results of P-TAE following primary endoscopic hemostasis in patients with serious comorbid conditions and high risk of rebleeding.
Methods:
During the period from 2014 to 2018, a total of 399 patients referred to our institution with a bleeding peptic ulcer, classified as type Forrest IA, IB, or IIA with the Rockall score ≥ 5, after endoscopic hemostasis was prospectively included in two groups-P-TAE group and control group, where endoscopy alone (EA) was performed. The P-TAE patients underwent flow-reducing left gastric artery or gastroduodenal artery embolization according to the ulcer type. The rebleeding rate, complications, frequency of surgical interventions, transfused packed red blood cells (PRBC), amount of fresh frozen plasma (FFP), and mortality rate were analyzed.
Results:
From 738 patients with a bleeding peptic ulcer, 399 were at high risk for rebleeding after endoscopic hemostasis. From this cohort, 58 patients underwent P-TAE, and 341 were allocated to the EA. A significantly lower rebleeding rate was observed in the P-TAE group, 3.4% vs. 16.2% in the EA group; p = 0.005. The need for surgical intervention reached 10.3% vs. 20.6% in the P-TAE and EA groups accordingly; p = 0.065. Patients that underwent P-TAE required less FFP, 1.3 unit vs. 2.6 units in EA; p = 0.0001. The mortality rate was similar in groups with a tendency to decrease in the P-TAE group, 5.7% vs. 8.5% in EA; p = 0.417.
Conclusion:
P-TAE is a feasible and safe procedure, and it may reduce the rebleeding rate and the need for surgical intervention in patients with a bleeding peptic ulcer when the rebleeding risk remains high after primary endoscopic hemostasis.
Related Concept Videos
 01:28
Peptic Ulcer Disease II: Pathophysiology
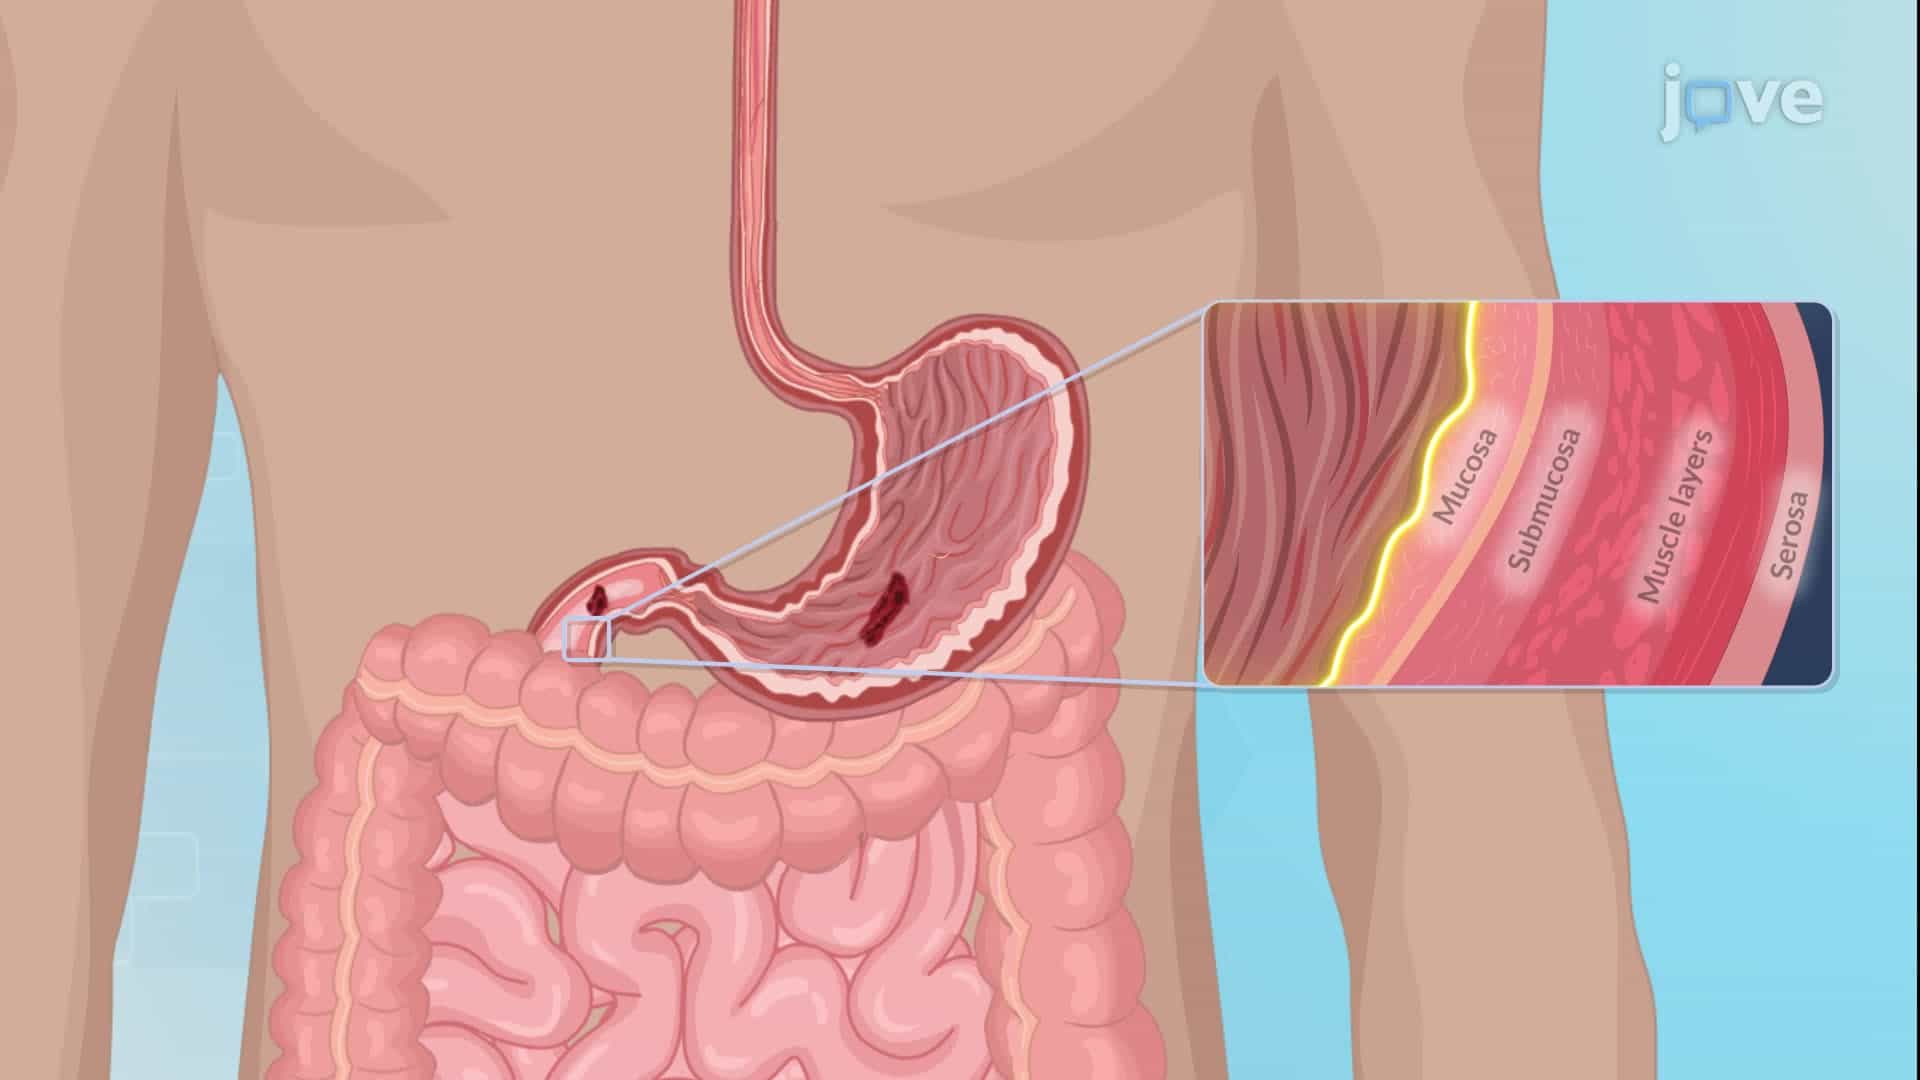
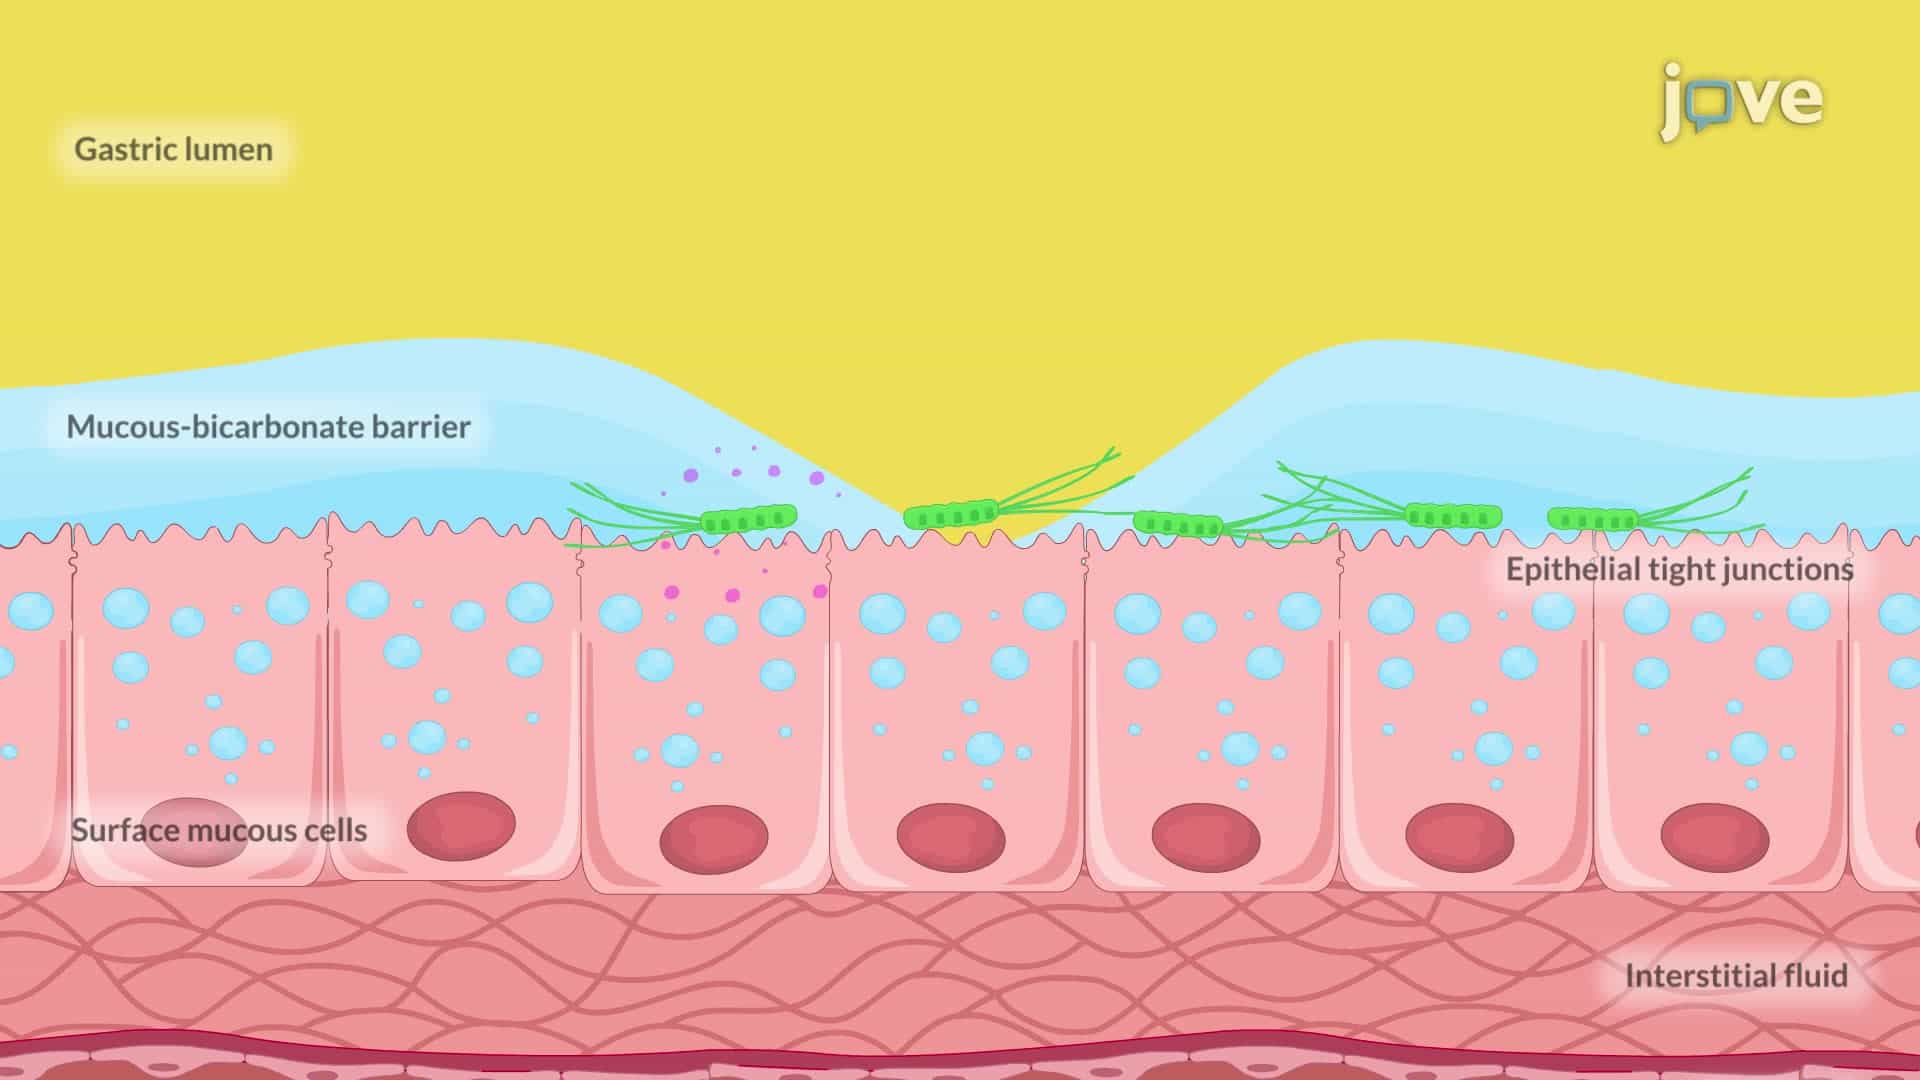
Damaging agents such as Helicobacter pylori, gastric acid, pepsin, and nonsteroidal anti-inflammatory drugs (NSAIDs) can weaken the mucosal defense, allowing hydrogen ions to infiltrate back and harm epithelial cells.
 01:30
Peptic Ulcer Disease I: Introduction
An acute ulcer, marked by superficial erosion and minimal inflammation, swiftly resolves upon identifying and addressing the underlying cause. In contrast, a chronic ulcer persists, potentially eroding through the muscular wall and forming fibrous tissue.
Peptic ulcers can also be...
 01:26
Peptic Ulcer Disease IV: Management
The therapeutic approach involves ensuring adequate rest, implementing drug therapy, promoting smoking cessation, making dietary modifications, and emphasizing long-term follow-up care.
Pharmacological management
The prevailing therapy for peptic ulcers involves a combination of managing the patient's current...
 01:22
Pathophysiology of Peptic Ulcer Disease: Injurious Factors
In the antrum region, G cells secrete the gastrin hormone that binds to gastrin-cholecystokinin-B (CCK2) receptors on parietal and enterochromaffin-like (ECL) cells in the fundic glands. Simultaneously, the vagus nerve releases acetylcholine, which binds...
 05:57
ADSC-sheet Transplantation to Prevent Stricture after Extended Esophageal Endoscopic Submucosal Dissection
 01:25
Peptic Ulcer Disease V: Surgical Management and Nursing Care
Surgical Interventions for Peptic Ulcer Disease