Growth from birth to adulthood in a patient with the neonatal form of Bartter syndrome
Related Experiment Video
Updated: Aug 19, 2026
Isolation of Neonatal Extrahepatic Cholangiocytes
Published on: June 5, 2014
W Proesmans1, G Massa, M Vanderschueren-Lodeweyckx
1Department of Paediatrics, University Hospital Gasthuisberg, Leuven, Belgium.

Insights
This study tracked growth in a patient with neonatal Bartter syndrome. Prostaglandin synthetase inhibitors, like indomethacin, promoted optimal growth and reduced symptoms, suggesting they are the best treatment.
Area of Science:
- Pediatric Endocrinology
- Nephrology
- Genetics
Background:
- Neonatal Bartter syndrome is a rare genetic disorder affecting kidney function.
- Early management focuses on fluid and electrolyte balance.
Observation:
- A patient with neonatal Bartter syndrome experienced suboptimal growth with initial therapies (fluids, potassium, triamterene).
- Spironolactone and potassium supplementation led to catch-up growth.
- Indomethacin initiation at age 9 resulted in accelerated growth and reduced polyuria/hypercalciuria.
Findings:
- Prostaglandin synthetase inhibitors (indomethacin) significantly improved growth velocity in this patient.
- Normal puberty and adult height (162 cm) were achieved.
- Therapy with prostaglandin synthetase inhibitors appears most effective for neonatal Bartter syndrome.
Implications:
- Early and optimized pharmacotherapy is crucial for achieving normal growth outcomes in neonatal Bartter syndrome.
- Prostaglandin synthetase inhibitors represent a key therapeutic strategy for managing growth deficits.
- This case highlights the long-term benefits of targeted treatment for rare genetic kidney diseases.
Abstract:
Growth from birth to the age of 19 years was studied in a patient with the neonatal form of Bartter syndrome. The initial modes of therapy (extra fluid, potassium supplements and triamterene) resulted in satisfactory but not optimal growth. Treatment with spironolactone together with potassium led to impressive catch-up growth. When the patient reached the age of 9 years, indomethacin therapy was started, which resulted in a second growth acceleration and was also accompanied by a significant reduction of both polyuria and hypercalciuria. Puberty developed normally, menarche occurred at 12 years 4 months and a normal adult height of 162 cm was reached at the age of 14 years. Treatment with prostaglandin synthetase inhibitors seems to be the best therapy for children with the neonatal form of Bartter syndrome.
Related Concept Videos
 01:24
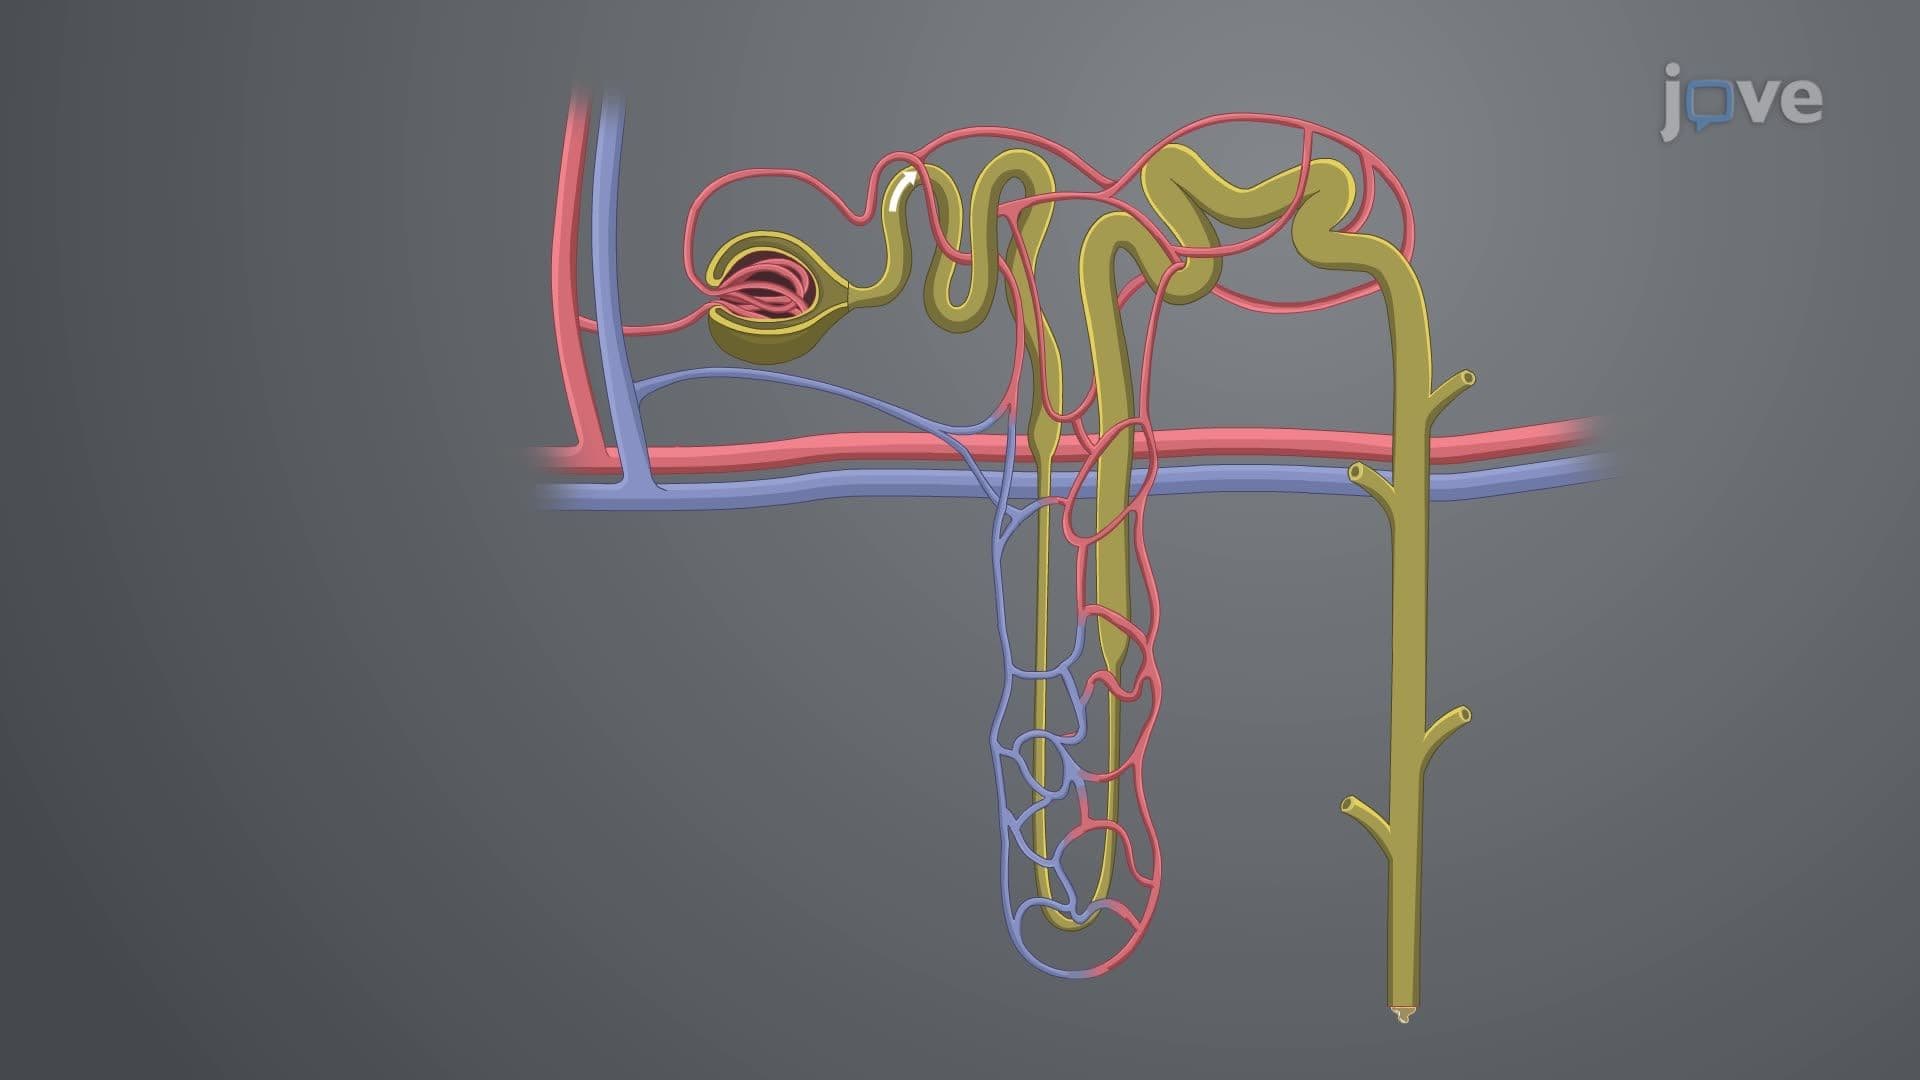
Renal Tubule and Collecting Duct
Proximal Convoluted Tubule (PCT):
The PCT is the initial segment of the renal tubule, extending from the Bowman's capsule that encloses the glomerulus. Its convoluted structure and microvilli-lined cells increase the surface area for reabsorption. The PCT reabsorbs glucose, amino acids, sodium, and water from the filtrate, ensuring essential...
 01:26
Reabsorption and Secretion in the DCT and Collecting Duct
The distal part of the DCT, along with the...
 01:21
Barrett Esophagus-I: Introduction
This constant acid exposure transforms the esophagus's pink mucosal lining (stratified squamous epithelium) into a type of lining more similar...
 01:24
Pharmacokinetics in Pediatric Patients: Drug Metabolism
 01:20
Pathophysiology of Diabetes
Type 1 diabetes is characterized by autoimmune-mediated destruction of pancreatic β cells, with environmental factors potentially triggering this process in genetically susceptible individuals. Despite many not having a family history, certain genes increase susceptibility, suggesting a...
 01:22
Physiology of the Genitourinary System II: Tubular Reabsorption and Secretion