Related Experiment Video
Updated: Jan 5, 2026


Optimized Minimally Invasive Transscleral Subretinal Injection Technique in Mouse
Published on: July 25, 2025
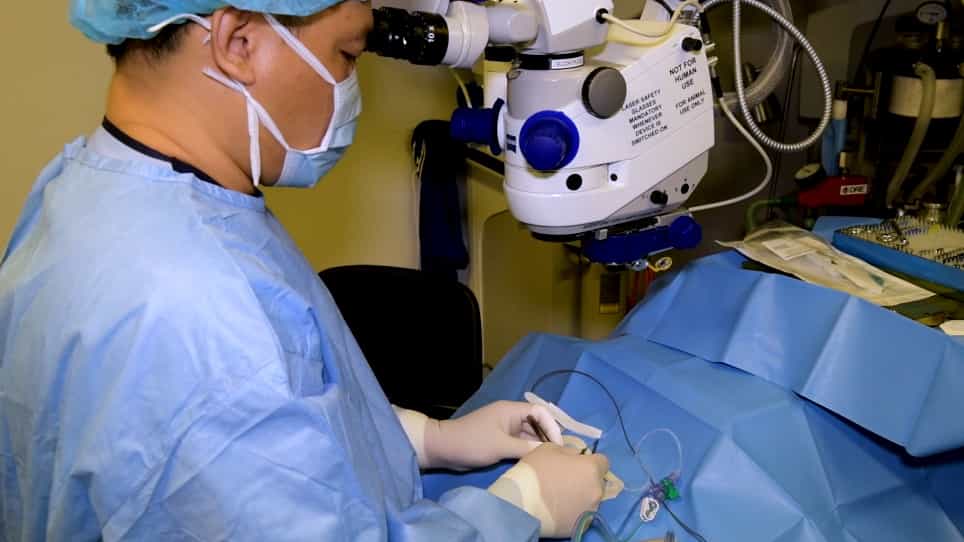
Efficacy and Safety of a Novel Blunt Cannula Trans-Sub-Tenon's Retrobulbar Block for Vitreoretinal Surgery
Tafadzwa Young-Zvasara1, Johanna Winder1, Sidath Wijetilleka1
1Cardiff Eye Unit, University Hospital of Wales, Cardiff, Wales.

Purpose:
To evaluate a novel trans-sub-Tenon's retrobulbar block (TSTRB) compared to sub-Tenon's block (STB) and peribulbar block (PBB) anesthesia for vitreoretinal surgery.
Methods:
This study was a prospective evaluation of cases undergoing TSTRB, STB, or PBB. The Kallio scale and Brahma scales were used to score hemorrhage and extraocular motility, respectively. Pain was documented on a visual analog score graded (1-10) at induction, intraoperatively, and postoperatively, any confounding variables were noted.
Results:
Seventy eyes have been used in this analysis, of which TSTRB was used in 37% (n = 26), PBB in 34% (n = 24), and STB in 29% (n = 20). Postoperative analgesia was required by 10% (n = 2) of STB and 8% (n = 2) of PBB; none of the TSTRB cases required analgesia (P = 0.003). The mean volume required with each technique was as follows: TSTRB, 4.8 ml; STB, 5.3 ml; and PBB, 10.4 ml (P = 0.030). The volume of anesthesia was correlated with the level of proptosis and even more important affected the ease of surgery most (P = 0.005). Akinesia was greatest with TSTRB > PBB > STB (P = 0.040). There were no complications such as brainstem anesthesia, globe perforation, or retrobulbar hemorrhage.
Conclusion:
Intentionally extending a STB into the retrobulbar space, via a TSTRB fenestration utilizes a familiar skill set. TSTRB produced the best levels of reduced kinesia during surgery and increased duration of postoperative analgesia. The technique uses a small-volume anesthesia.