Related Experiment Video
Updated: Jan 4, 2026
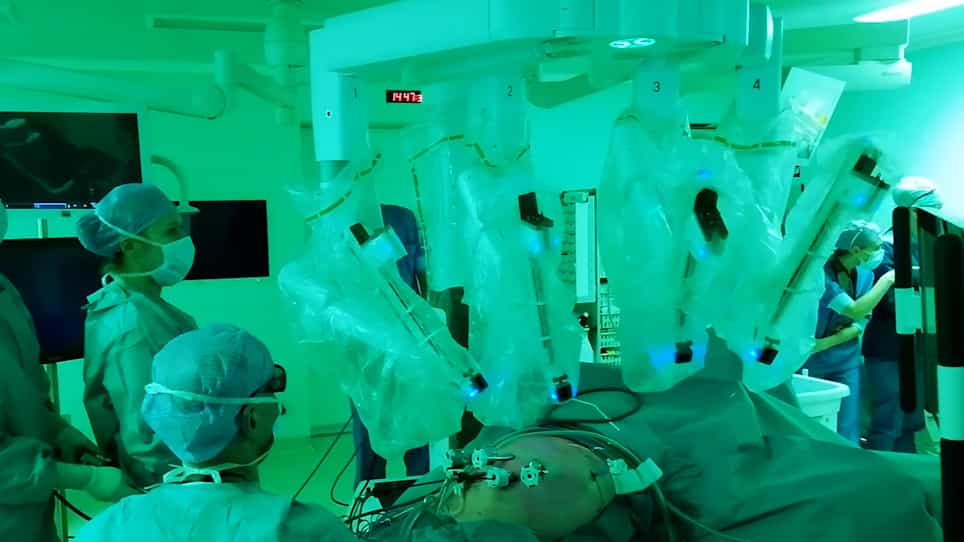

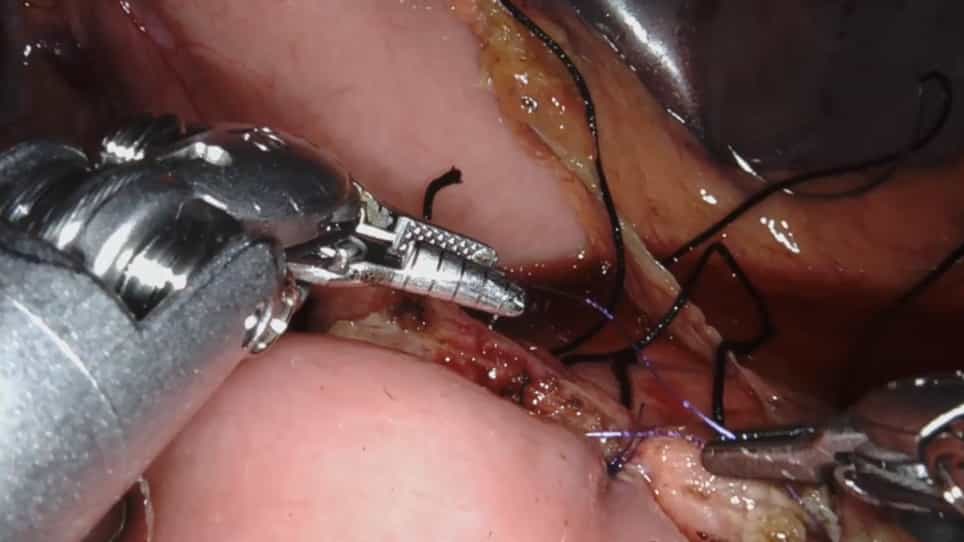
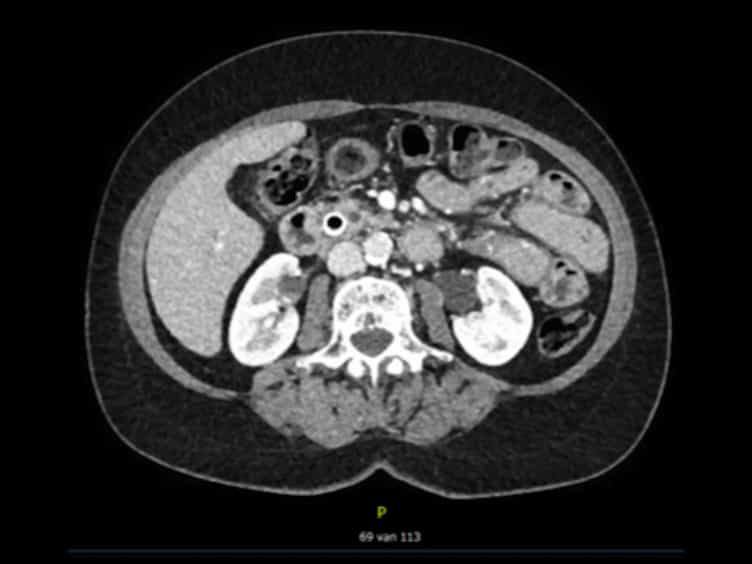
Robotic Pancreatoduodenectomy for Pancreatic Head Cancer: a Case Report of a Standardized Technique
Published on: June 24, 2022
A systematic review and network meta-analysis of different surgical approaches for pancreaticoduodenectomy
Sivesh K Kamarajah1, James R Bundred2, Olivier S Marc3
1Department of HPB and Transplant Surgery, Freeman Hospital, Newcastle upon Tyne, Tyne and Wear, United Kingdom; Institute of Cellular Medicine, Newcastle University, Newcastle upon Tyne, Tyne and Wear, United Kingdom.

Background:
Minimally invasive pancreaticoduodenectomy (MIPD) is a demanding surgical procedure, thus explaining its slow expansion and limited popularity amongst Hepato-Pancreatico-Biliary (HPB) surgeons. However, three main advantages of robotic assisted pancreaticoduodenectomy (PD) including improved dexterity, 3D vision less surgical fatigue, may overcome some of the hurdles and ultimately lead to a wider adoption. This systematic review and network meta-analysis aims to evaluate the current literature on open and MIPD.
Methods:
A systematic literature search was conducted for studies reporting robotic, laparoscopic and open surgery for PD. Network meta-analysis of intraoperative (operating time, blood loss, transfusion rate), postoperative (overall and major complications, pancreatic fistula, delayed gastric emptying, length of hospital stay) and oncological outcomes (R0 resection, lymphadenectomy) were performed.
Results:
Sixty-one studies including 62,529 patients were included in the network meta-analysis, of which 3% (n = 2131) were totally robotic (TR) and 10% (n = 6514) were totally laparoscopic (TL). There were no significant differences between surgical techniques for major complications, overall and grade B/C fistula, biliary leak, mortality and R0 resections. Transfusion rates were significantly lower in TR compared to TL and open. Operative time for TR was longer compared with open and TL. Both TL and TR were associated with significantly lower rates of wound infections, pulmonary complications, shorter length of stay and higher lymph nodes examined when compared to open. TR was associated with significantly lower conversion rates than TL.
Conclusion:
In summary, this network meta-analysis highlights the variability in techniques within MIPD and compares other variations to the conventional open PD. Current evidence appears to demonstrate MIPD, both laparoscopic and robotic techniques are associated with improved rates of surgical site infections, pulmonary complications, and a shorter hospital stay, with no compromise in oncological outcomes for cancer resections.