Related Experiment Video
Updated: Jan 4, 2026
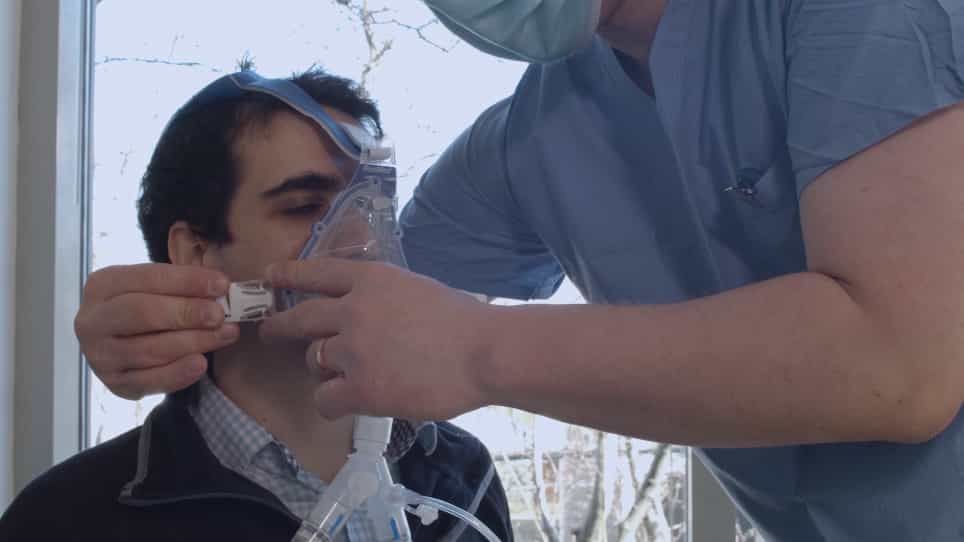

A Novel Inhalation Mask System to Deliver High Concentrations of Nitric Oxide Gas in Spontaneously Breathing Subjects
Published on: May 4, 2021
Is a 12-h Nitrox dive hazardous for pulmonary function?
Olivier Castagna1,2, Cedric Bergmann3, Jean Eric Blatteau4
1Underwater Research Team, ERRSO, Military Biomedical Research Institute (IRBA), BP 600, 83800, Toulon Cedex 9, France. castagna.olivier@gmail.com.

Purpose:
Prolonged exposure to a high partial pressure of oxygen leads to inflammation of pulmonary tissue [pulmonary oxygen toxicity (POT)], which is associated with tracheobronchial irritation, retrosternal pain and coughing, and decreases in vital capacity (VC). The nitric oxide (NO) concentration in exhaled gas (FeNO) has been used as an indicator of POT, but the effect of SCUBA diving on FeNO has rarely been studied. The study presented here aimed to assess alterations to pulmonary function and FeNO following a 12-h dive using breathing apparatus with a relatively high partial pressure of oxygen.
Methods:
Six healthy, male, non-smoking military SCUBA divers were recruited (age 31.8 ± 2.7 years, height 179 ± 0.09 cm, and body weight 84.6 ± 14 kg). Each diver completed a 12-h dive using a demand-controlled semi-closed-circuit rebreather. During the 12 h of immersion, divers were subjected to 672 oxygen toxicity units (OTU). A complete pulmonary function test (PFT) was completed the day before and immediately after immersion. FeNO was measured using a Nobreath™ Quark (COSMED™, Rome, Italy), three times for each diver. The first datapoint was collected before the dive to establish the "basal state", a second was collected immediately after divers emerged from the water, and the final measurement was taken 24 h after the dive.
Result:
Despite prolonged inhalation of a hyperoxic hyperbaric gas mixture, no clinical pulmonary symptoms were observed, and no major changes in pulmonary function were detected. However, a major decrease in FeNO values was observed immediately after emersion [0-12 ppb (median, 3.8 ppb)], with a return to baseline [2-60 ppb (median, 26 ppb) 24 h later (3-73 ppb (median, 24.7 ppb)].
Conclusion:
These results suggest that if the OTU remain below the recommended limit values, but does alter FeNO, this type of dive does not persistently impair lung function.
More Related Videos
 08:44
Author Spotlight: Integrating Alveolar-Capillary Reserve Measurements in Exercise Adaptation and Therapeutic Strategies
Published on: February 2, 2024
 14:52
Recording Brain Electromagnetic Activity During the Administration of the Gaseous Anesthetic Agents Xenon and Nitrous Oxide in Healthy Volunteers
Published on: January 13, 2018
Related Concept Videos
 01:21
Acute Respiratory Failure-II
The underlying physiological abnormalities that contribute to hypoxemic respiratory failure include:
 01:26
Pneumothorax-I
Pneumothorax can be even further classified as spontaneous, traumatic, and tension pneumothorax.
 01:19
Respiratory Assessment: Purpose and Indications
Objectives and Importance:
The primary goal of respiratory assessment is to evaluate patients at early risk of clinical deterioration. Since respiratory distress often precedes other signs of declining health, breathing patterns and sounds become a...
 01:29
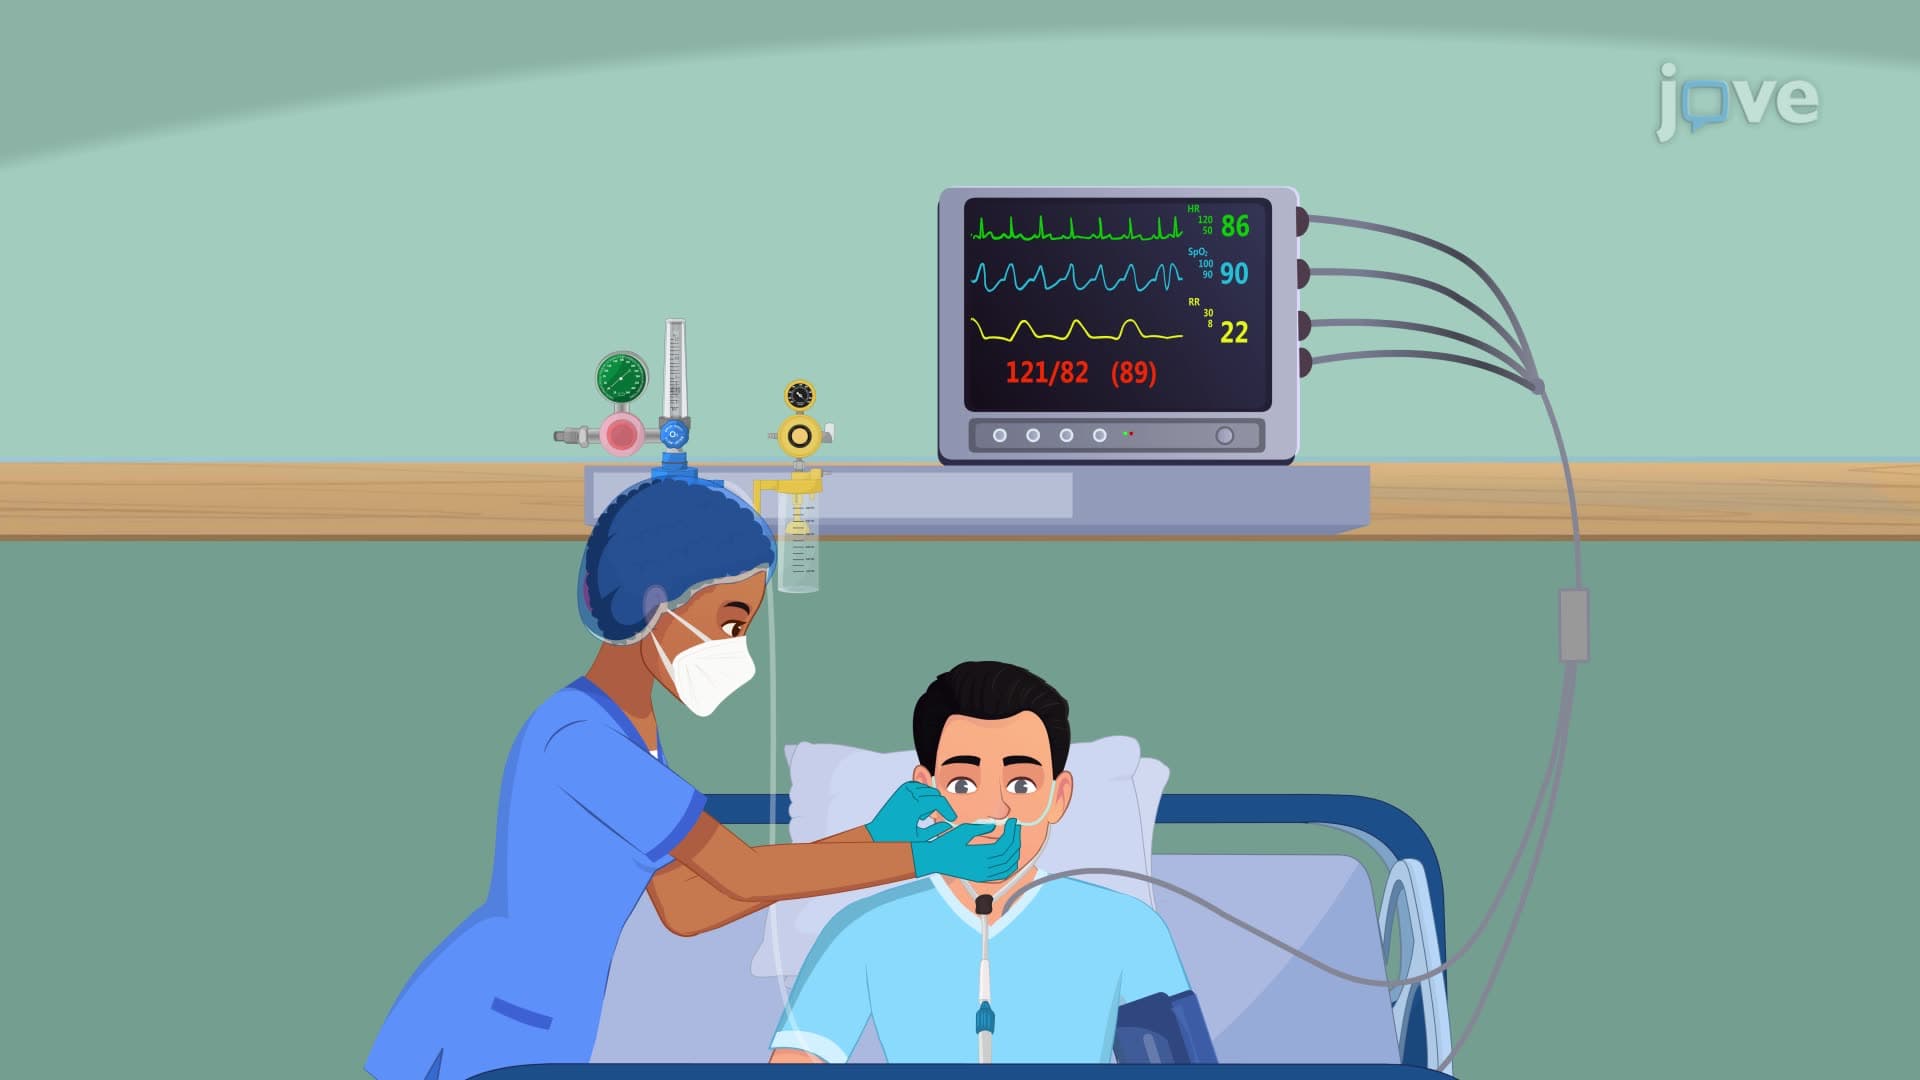
Administering Oxygen by Nasal Cannula
Nasal Cannulas
A nasal cannula is a lightweight tube split into two prongs placed in the nostrils,...
 01:23
Acute Respiratory Failure-IV
 01:25
Pulmonary Function Tests
Pulmonary Function Tests are crucial diagnostic tools for assessing respiratory function, particularly in patients with chronic respiratory disorders. They comprehensively evaluate lung volumes, ventilatory function, breathing mechanics, diffusion, and gas exchange. These tests help diagnose pulmonary diseases and play a significant role in monitoring disease progression, evaluating disability, and assessing response to therapy.
PFTs involve using a spirometer, a...