

Obesity alters the topographical distribution of ventilation and the regional response to bronchoconstriction
S Rutting1,2, S Mahadev1,2, K O Tonga1,2,3,4
1Department of Respiratory Medicine, Royal North Shore Hospital, St. Leonards, NSW, Australia.

Abstract:
Obesity is associated with reduced operating lung volumes that may contribute to increased airway closure during tidal breathing and abnormalities in ventilation distribution. We investigated the effect of obesity on the topographical distribution of ventilation before and after methacholine-induced bronchoconstriction using single-photon emission computed tomography (SPECT)-computed tomography (CT) in healthy subjects. Subjects with obesity (n = 9) and subjects without obesity (n = 10) underwent baseline and postbronchoprovocation SPECT-CT imaging, in which Technegas was inhaled upright and followed by supine scanning. Lung regions that were nonventilated (Ventnon), low ventilated (Ventlow), or well ventilated (Ventwell) were calculated using an adaptive threshold method and were expressed as a percentage of total lung volume. To determine regional ventilation, lungs were divided into upper, middle, and lower thirds of axial length, derived from CT. At baseline, Ventnon and Ventlow for the entire lung were similar in subjects with and without obesity. However, in the upper lung zone, Ventnon (17.5 ± 10.6% vs. 34.7 ± 7.8%, P < 0.001) and Ventlow (25.7 ± 6.3% vs. 33.6 ± 5.1%, P < 0.05) were decreased in subjects with obesity, with a consequent increase in Ventwell (56.8 ± 9.2% vs. 31.7 ± 10.1%, P < 0.001). The greater diversion of ventilation to the upper zone was correlated with body mass index (rs = 0.74, P < 0.001), respiratory system resistance (rs = 0.72, P < 0.001), and respiratory system reactance (rs = -0.64, P = 0.003) but not with lung volumes or basal airway closure. Following bronchoprovocation, overall Ventnon increased similarly in both groups; however, in subjects without obesity, Ventnon only increased in the lower zone, whereas in subjects with obesity, Ventnon increased more evenly across all lung zones. In conclusion, obesity is associated with altered ventilation distribution during baseline and following bronchoprovocation, independent of reduced lung volumes.NEW & NOTEWORTHY Using ventilation SPECT-computed tomography imaging in healthy subjects, we demonstrate that ventilation in obesity is diverted to the upper lung zone and that this is strongly correlated with body mass index but is independent of operating lung volumes and of airway closure. Furthermore, methacholine-induced bronchoconstriction only occurred in the lower lung zone in individuals who were not obese, whereas in subjects who were obese, it occurred more evenly across all lung zones. These findings show that obesity-associated factors alter the topographical distribution of ventilation.
More Related Videos
Related Concept Videos
 01:19
Factors Affecting Pulmonary Ventilation
Alveolar Surface Tension
The alveolar fluid lines the luminal surface of the alveoli and exerts a force called surface tension. This force is caused by the polar water molecules in the liquid being more strongly attracted to each...
 01:20
Chronic Obstructive Pulmonary Disease-II: Pathophysiology
Chronic Inflammation
 01:26
Asthma-II: Pathophysiology and Classification
Additionally, environmental and genetic factors play crucial roles in determining an individual's susceptibility to asthma and the severity of their condition.
Critical processes in asthma pathophysiology include:
 01:17
Gross Anatomy of the Lungs
 01:25
Pharmacokinetics in Obese Patients: Drug Absorption and Distribution
 01:23
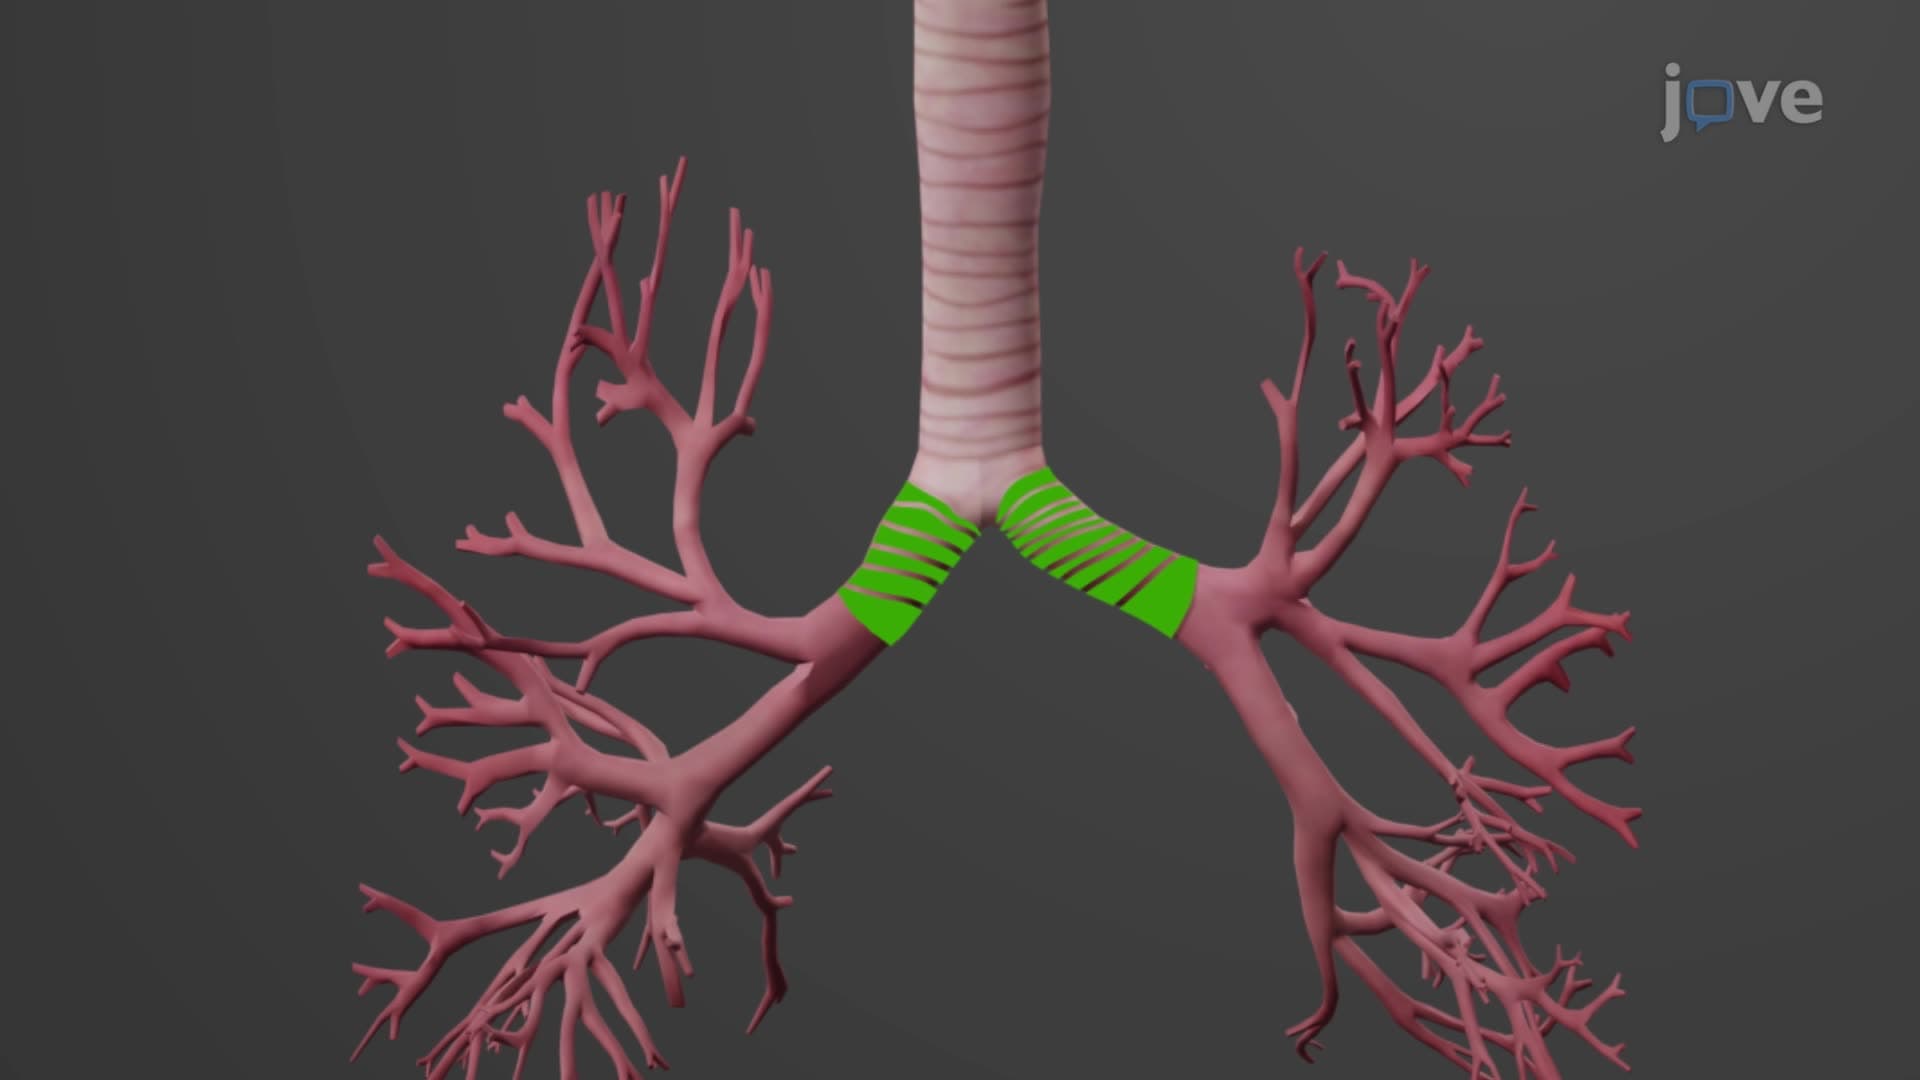
The Bronchial Tree
The trachea, commonly known as the windpipe, is a tube that connects the larynx (voice box) to the bronchi. At a point called the carina, it bifurcates into two primary bronchi. The right primary bronchus is wider, shorter, and more vertical than the left primary...