Related Experiment Video
Updated: Jan 3, 2026
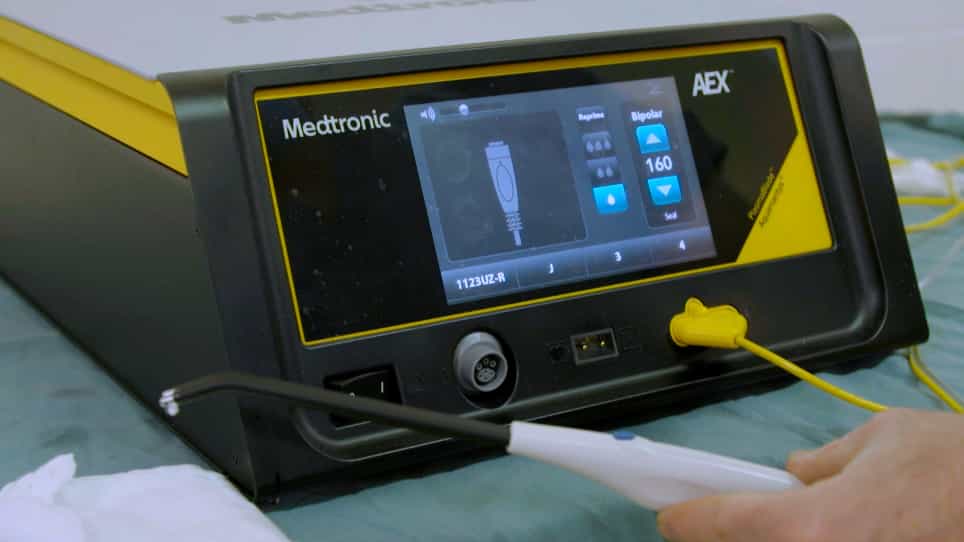

A Saline/Bipolar Radiofrequency Energy Device As an Adjunct for Hemostasis in Solid Organ Injury/Trauma
Published on: July 28, 2020
Sternotomy for Hemorrhage Control in Trauma
William Duong1, Areg Grigorian1, Lutfi Al-Khouja1
1Division of Trauma, Burns and Surgical Critical Care, Department of Surgery, University of California, Irvine, California.

Background:
Little is known about the injuries, mechanisms, and outcomes in trauma patients undergoing sternotomy for hemorrhage control (SHC). The purpose of this study was to identify predictors of mortality for SHC and provide a descriptive analysis of the use of SHC in trauma. We hypothesize blunt trauma is associated with higher mortality compared with penetrating trauma among trauma patients requiring SHC.
Methods:
The Trauma Quality Improvement Program (2013-2016) database was queried for adult patients undergoing SHC within 24 h of admission. Patients with blunt and penetrating trauma were compared using chi-square and Mann-Whitney U-test. A multivariable logistic regression model was used to determine the risk of mortality.
Results:
Of 584 patients undergoing SHC, 322 (55.1%) were involved in penetrating trauma, and 69 (11.8%) were involved in blunt. The blunt trauma group had a higher median injury severity score (31.5 versus 25.0; P < 0.001) compared with the penetrating group. The median time to hemorrhage control was longer in those with blunt compared with penetrating trauma (84.6 versus 49.8 min; P < 0.001). The mortality rate was higher in patients with blunt compared with penetrating trauma (29.0% versus 12.7%; P < 0.001). However, after adjusting for covariates, there was no difference in risk of mortality between blunt and penetrating trauma (P = 0.06).
Conclusions:
Trauma patients requiring SHC after blunt trauma had a higher mortality rate than those in penetrating trauma. After adjusting for predictors of mortality, there was no difference in risk of mortality despite nearly double the time to hemorrhage control in patients presenting after blunt trauma.
Related Concept Videos
 01:26
Flail Chest-II
Assessment:
1. Clinical Evaluation:
History:
 01:28
Esophageal Varices-II: Clinical Features and Management
In the initial assessment, a thorough review of the patient's medical history is vital to identify risk factors such as liver disease, alcohol...
 01:30
Epistaxis
Etiology
Possible causes of this condition include high blood pressure, trauma, low humidity, upper respiratory tract infections, allergies, foreign bodies, nasal inhalation of corticosteroids or illicit drugs, excessive use of decongestant nasal sprays, facial or nasal surgery, anatomic malformation, tumors, or systemic...