Related Experiment Video
Updated: Jan 1, 2026
Improved Home Blood Pressure Control by CT-guided Ozone-mediated Renal Denervation for Patients with Resistant Hypertension
Published on: June 6, 2025
A Randomized Trial Comparing the Safety, Adherence, and Pharmacodynamics Profiles of Two Doses of Sodium Bicarbonate
Kalani L Raphael1, Tamara Isakova2, Joachim H Ix3
1Department of Internal Medicine, University of Utah Health and Renal Section, Veterans Affairs Salt Lake City Health Care System, Salt Lake City, Utah; kalani.raphael@hsc.utah.edu.

Background:
Oral sodium bicarbonate (NaHCO3) may preserve kidney function in CKD, even if initiated when serum bicarbonate concentration is normal. Adequately powered trials testing this hypothesis have not been conducted, partly because the best dose for testing is unknown.
Methods:
This multicenter pilot trial assessed the safety, tolerability, adherence, and pharmacodynamics of two doses of NaHCO3 over 28 weeks in adults with eGFR 20-44 or 45-59 ml/min per 1.73 m2 with urinary albumin/creatinine (ACR) ≥50 mg/g and serum bicarbonate 20-28 meq/L. We randomly assigned 194 participants from ten clinical sites to receive higher-dose (HD-NaHCO3; 0.8 meq/kg of lean body wt per day; n=90) or lower-dose (LD-NaHCO3; 0.5 meq/kg of lean body wt per day; n=52) NaHCO3 or matching placebo (n=52). The dose was adjusted depending on side effects. The prescribed dose at week 28 was the primary outcome; a dose was considered acceptable for a full-scale trial if ≥67% of participants were on full-dose and ≥80% were on ≥25% of the per-protocol dose.
Results:
Mean±SD baseline eGFR was 36±9 ml/min per 1.73 m2, serum bicarbonate was 24±2 meq/L, and median (IQR) ACR was 181 (25-745) mg/g. Both doses were well tolerated without significant changes in BP, weight, or serum potassium. The proportions of adverse events and hospitalizations were similar across the groups. Consequently, 87% in HD-NaHCO3, 96% in LD-NaHCO3, and 87% in placebo were on full dose at week 28; and 91% in HD-NaHCO3, 98% in LD-NaHCO3, and 92% in placebo were on ≥25% of the per-protocol dose. Mean urinary ammonium excretion was 25% lower and serum bicarbonate concentration was 1.3 meq/L higher in HD-NaHCO3 compared with LD-NaHCO3 at week 28. However, mean ACR increased by 12% in the lower-dose group and 30% in the higher-dose group.
Conclusions:
Both NaHCO3 doses were well tolerated over 28 weeks with no significant difference in adverse events or hospitalization compared with placebo. The higher dose lowered urinary ammonium excretion and increased serum bicarbonate more than the lower dose but was associated with a greater increase in ACR. The higher 0.8 meq/kg of lean body wt per day dose of NaHCO3 may be a reasonable choice for future trials.
More Related Videos
 06:28
E-Patient Counseling Trial E-PACO: Computer Based Education versus Nurse Counseling for Patients to Prepare for Colonoscopy
Published on: August 1, 2019
 04:53
A Clinical Trial Assessing the Safety, Efficacy, and Delivery of Olive-Oil-Based Three-Chamber Bags for Parenteral Nutrition
Published on: September 20, 2019
Related Concept Videos
 01:25
Drug Dosing in Renal Diseases: Dose Adjustments Based on Drug Clearance and Elimination Rate Constant
 01:28
Drug Dosing in Renal Diseases: Estimation of Glomerular Filtration Rate Based on Serum Creatinine Concentration
 01:29
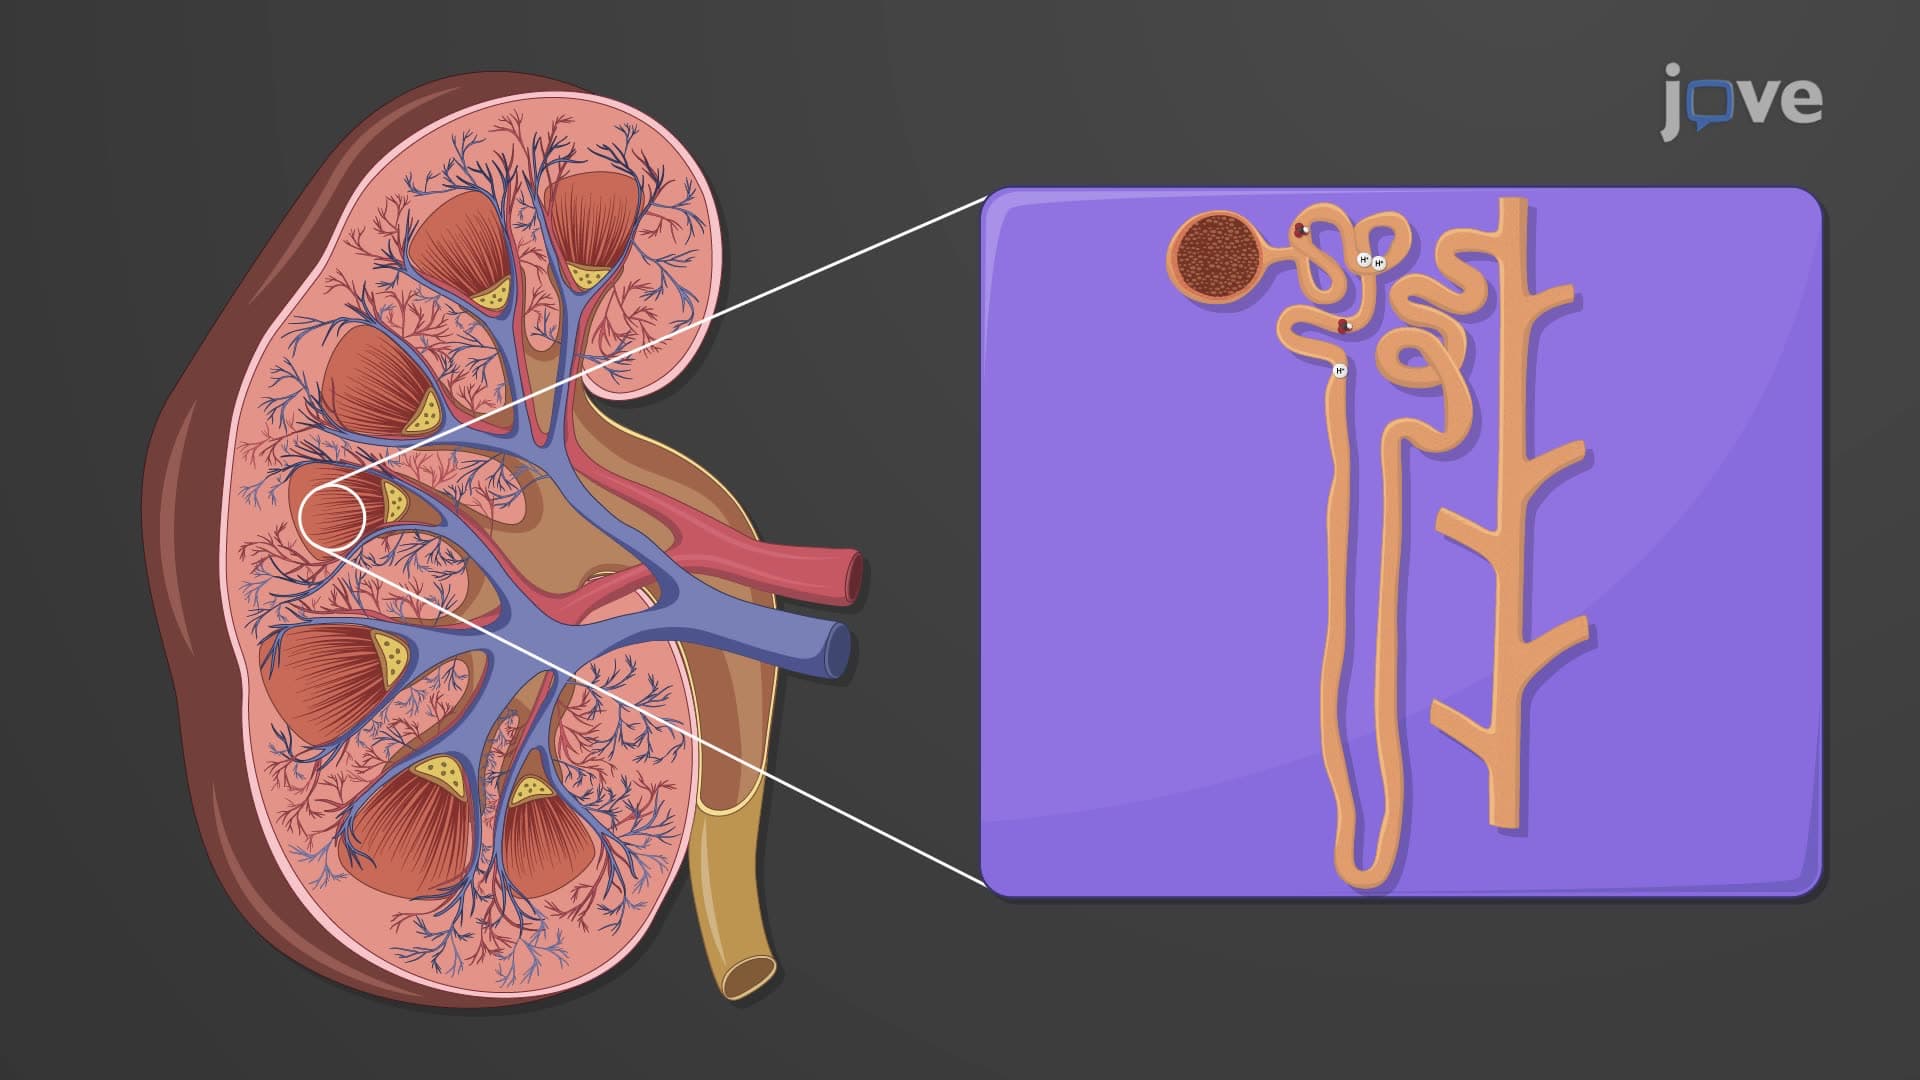
Renal Regulation of Acid-Base Balance
In the kidneys, cells within the proximal convoluted tubules (PCT) and the collecting ducts secrete hydrogen ions (H+) into the tubular fluid. Specifically, in the PCT, Na+/H+ antiporters secrete H+ while reabsorbing Na+.
However, the intercalated cells in...
 01:22
Bicarbonate-Carbonic Acid Buffer
 01:22
Renal Drug Excretion: Effect of Urine pH, Flow Rate, and Drug pKa
The pKa of a...
 01:15
Bioavailability Study Design: Healthy Subjects Versus Patients