Related Experiment Video
Updated: Jan 1, 2026
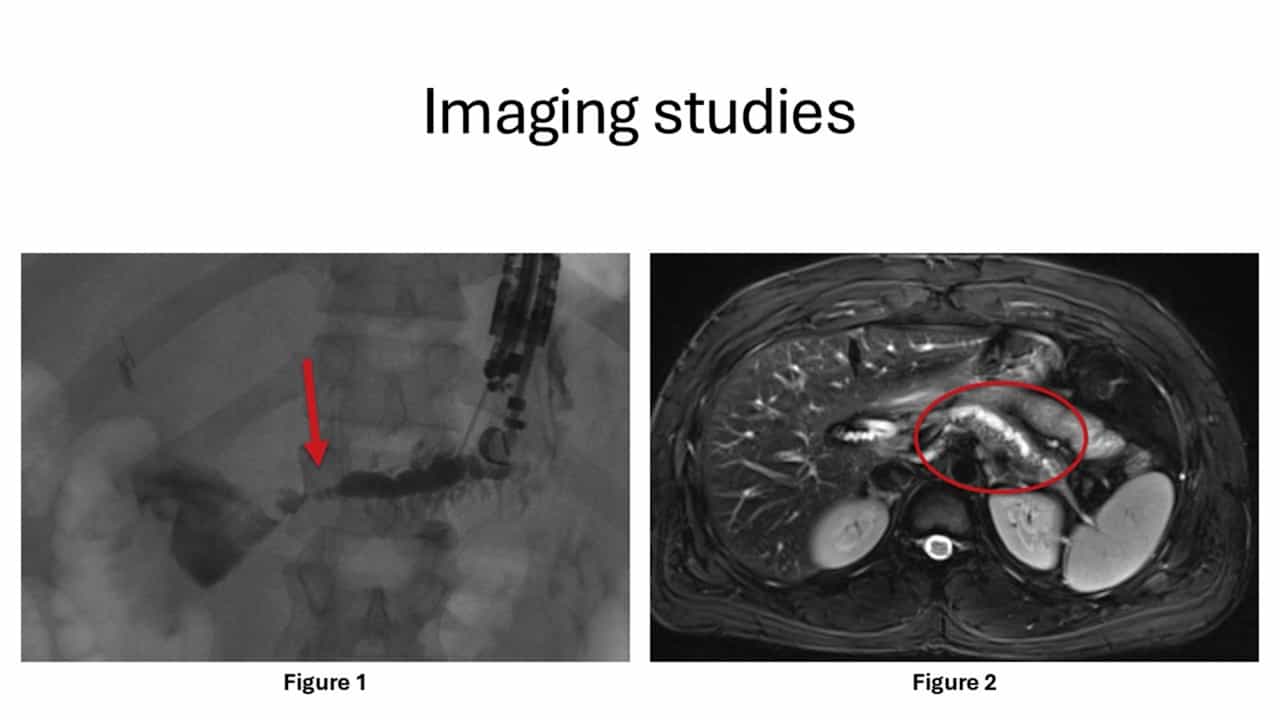

Robotic-assisted Lateral Pancreaticojejunostomy for Chronic Pancreatitis
Published on: September 5, 2025
Diagnosis and Management of Chronic Pancreatitis: A Review
Vikesh K Singh1, Dhiraj Yadav2, Pramod K Garg3
1Division of Gastroenterology, Department of Medicine, Johns Hopkins Medical Institutions, Baltimore, Maryland.

Importance:
Chronic pancreatitis (CP) is a chronic inflammatory and fibrotic disease of the pancreas with a prevalence of 42 to 73 per 100 000 adults in the United States.
Observations:
Both genetic and environmental factors are thought to contribute to the pathogenesis of CP. Environmental factors associated with CP include alcohol abuse (odds ratio [OR], 3.1; 95% CI, 1.87-5.14) for 5 or more drinks per day vs abstainers and light drinkers as well as smoking (OR, 4.59; 95% CI, 2.91-7.25) for more than 35 pack-years in a case-control study involving 971 participants. Between 28% to 80% of patients are classified as having "idiopathic CP." Up to 50% of these individuals have mutations of the trypsin inhibitor gene (SPINK1) or the cystic fibrosis transmembrane conductance regulator (CFTR) gene. Approximately 1% of people diagnosed with CP may have hereditary pancreatitis, associated with cationic trypsinogen (PRSS1) gene mutations. Approximately 80% of people with CP present with recurrent or chronic upper abdominal pain. Long-term sequelae include diabetes in 38% to 40% and exocrine insufficiency in 30% to 48%. The diagnosis is based on pancreatic calcifications, ductal dilatation, and atrophy visualized by imaging with computed tomography, magnetic resonance imaging, or both. Endoscopic ultrasound can assist in making the diagnosis in patients with a high index of suspicion such as recurrent episodes of acute pancreatitis when imaging is normal or equivocal. The first line of therapy consists of advice to discontinue use of alcohol and smoking and taking analgesic agents (nonsteroidal anti-inflammatory drugs and weak opioids such as tramadol). A trial of pancreatic enzymes and antioxidants (a combination of multivitamins, selenium, and methionine) can control symptoms in up to 50% of patients. Patients with pancreatic ductal obstruction due to stones, stricture, or both may benefit from ductal drainage via endoscopic retrograde cholangiopancreatography (ERCP) or surgical drainage procedures, such as pancreaticojejunostomy with or without pancreatic head resection, which may provide better pain relief among people who do not respond to endoscopic therapy.
Conclusions And Relevance:
Chronic pancreatitis often results in chronic abdominal pain and is most commonly caused by excessive alcohol use, smoking, or genetic mutations. Treatment consists primarily of alcohol and smoking cessation, pain control, replacement of pancreatic insufficiency, or mechanical drainage of obstructed pancreatic ducts for some patients.

Related Concept Videos
 01:29
Chronic Pancreatitis II: Collaborative Care
Assessment:
 01:24
Chronic Pancreatitis I: Introduction
Pancreatitis is the inflammation of the pancreas, which occurs when the immune system becomes active and causes swelling, pain, and disruptions in organ function. Pancreatitis can manifest as either an acute or chronic condition.
Acute pancreatitis arises suddenly and lasts for a brief duration, while chronic pancreatitis is a long-term affliction...
 01:30
Acute Pancreatitis II: Clinical Manifestations and Management
 01:27
Acute Pancreatitis I: Introduction
Acute pancreatitis is characterized by rapid inflammation of the pancreas, often caused by factors like gallstone blockage or excessive alcohol consumption. Chronic pancreatitis, on the other hand, is a slow, progressive inflammation that may result from long-term alcohol abuse, obstructions in the pancreatic duct, or genetic factors.
The causes of acute pancreatitis include:
 01:15
Diabetes: Management and Pharmacotherapy
Insulin remains the cornerstone of treatment for most patients with type 1 and many...
 01:26
Peptic Ulcer Disease IV: Management
The therapeutic approach involves ensuring adequate rest, implementing drug therapy, promoting smoking cessation, making dietary modifications, and emphasizing long-term follow-up care.
Pharmacological management
The prevailing therapy for peptic ulcers involves a combination of managing the patient's current...