Related Experiment Video
Updated: Jan 1, 2026

Establishment of an Extracellular Acidic pH Culture System
Published on: November 19, 2017
Successful correction of metabolic acidosis is difficult to achieve in chronic kidney disease
Fernando Caravaca-Fontán1, Rosa Díaz-Campillejo1, Julián Valladares1
1Servicio de Nefrología, Hospital Universitario de Badajoz, Badajoz, España.

Introduction:
Metabolic acidosis (MA) is a common complication of chronic kidney disease (CKD) and is associated with numerous adverse effects, which is why its correction is highly recommended. Oral sodium bicarbonate is the current treatment of choice.
Objectives:
To describe the prevalence of MA in advanced CKD patients and to determine the clinical and biochemical characteristics associated with its successful correction.
Material And Methods:
Retrospective, observational cohort study in adult patients with CKD stage 4-5. The inclusion criteria were: not being treated with alkali therapy at the time of inclusion, and to have at least three consecutive glomerular filtration rate (GFR) measurements and biochemical parameters during a minimum follow-up period of 3 months. Incident patients with serum bicarbonate<22 mEq/l were included in the follow-up study and treated with oral sodium bicarbonate. Correction was considered successful when more than half of the samples and the mean bicarbonate levels during individual follow-up were≥22 mEq/l.
Results:
The study group consisted of 969 patients (age 65±14 years, 507 males) with a mean GFR of 14.8±4.5ml/min/1.73 m2. At baseline, 530 patients (55%) had serum bicarbonate<22mEq/l. They were treated with sodium bicarbonate and followed for 15 months. Satisfactory correction of MA was only achieved in 133 patients (25%). By multivariate logistic regression analysis, the main characteristics of patients with adequate control of MA were: age (OR=1.03; 95% CI 1.01 - 1.05), baseline GFR (OR=1.07; 1.02 - 1.12), and treatment with proton-pump inhibitors (OR=1.61; 95% CI 1.06 - 2.44). Patients who achieved successful correction of MA showed slower CKD progression (-1.67±3.71 vs -4.36±4.56ml/min/1.73 m2/year, P<.0001), and lower average serum potassium concentration (5.1±0.5 vs 5.3±0.5, P<.0001) than those who did not. However, there were no differences in the hospitalisation or mortality rate.
Conclusion:
MA is a common complication of advanced CKD but difficult to manage with current therapies. Due to the significant potential benefit of controlling MA, new, more effective therapies should be further researched.
More Related Videos


Related Concept Videos
 01:29
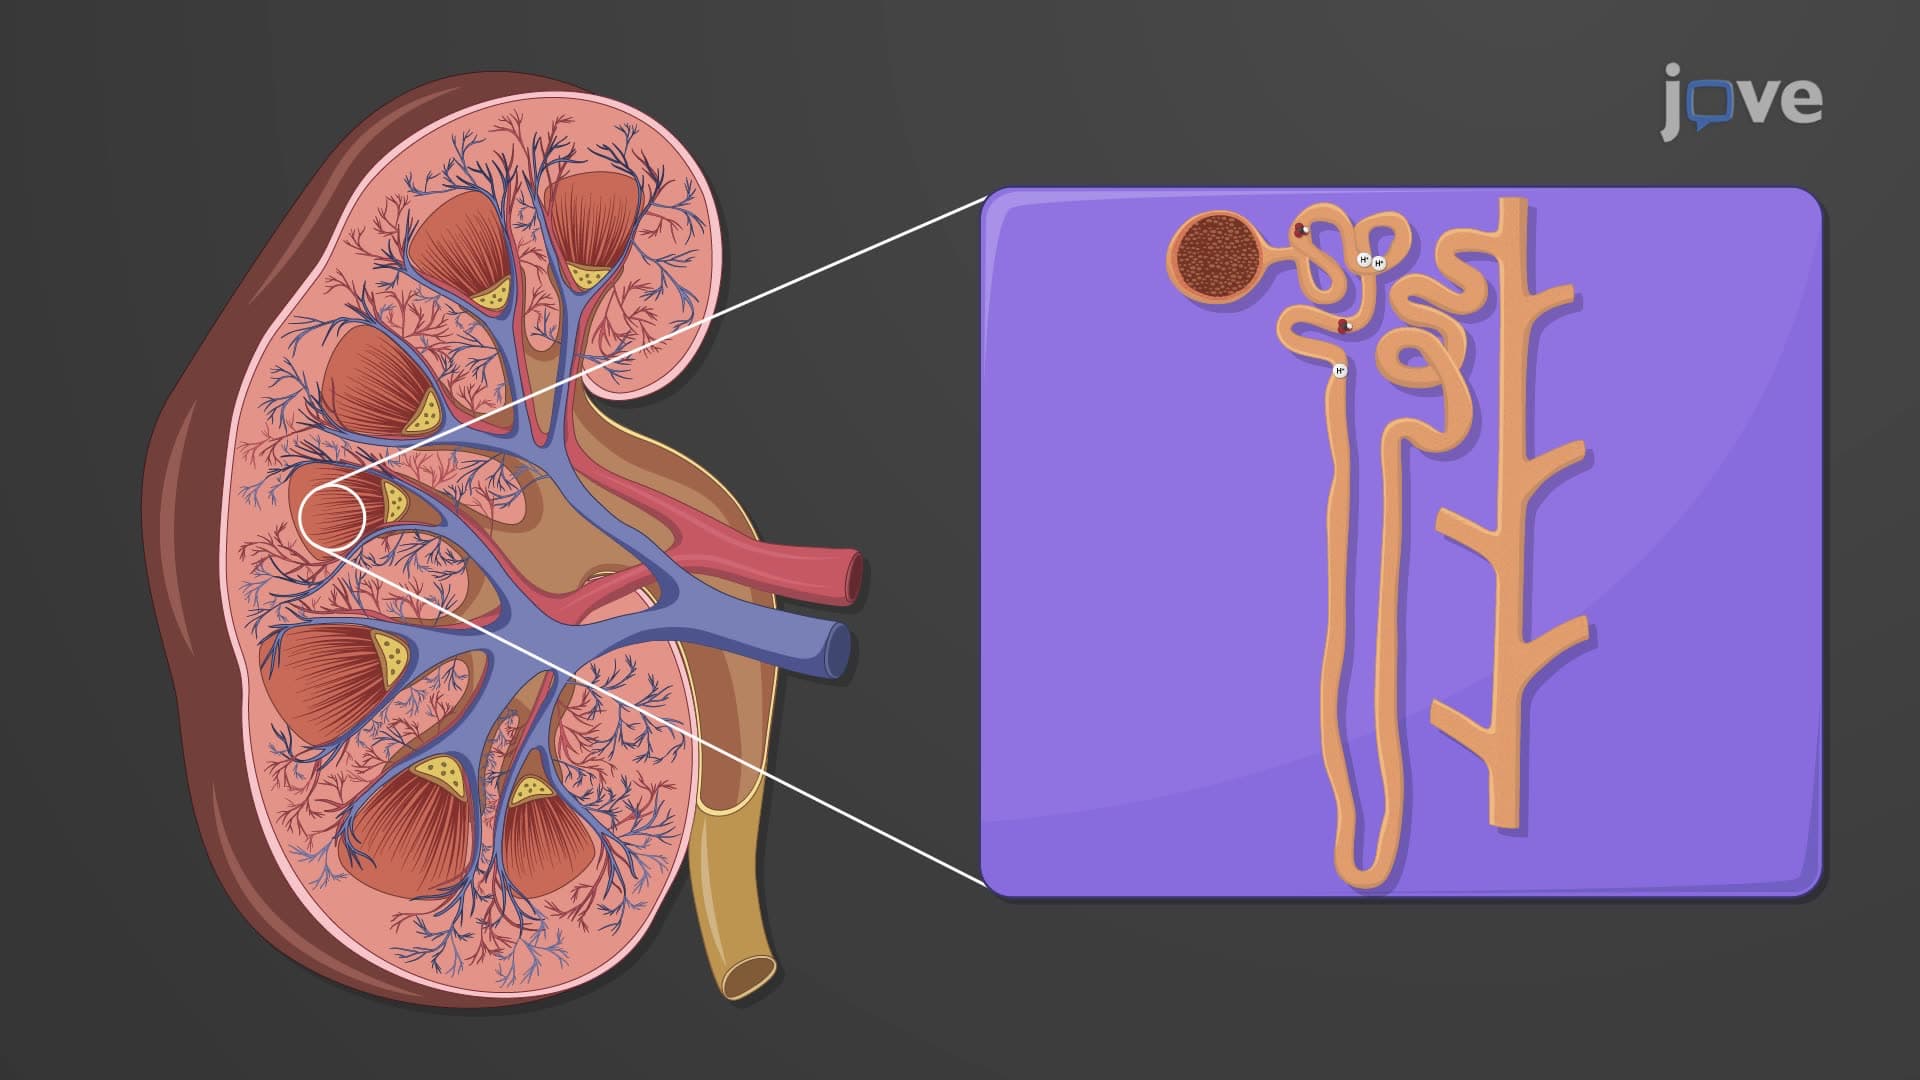
Renal Regulation of Acid-Base Balance
In the kidneys, cells within the proximal convoluted tubules (PCT) and the collecting ducts secrete hydrogen ions (H+) into the tubular fluid. Specifically, in the PCT, Na+/H+ antiporters secrete H+ while reabsorbing Na+.
However, the intercalated cells in...
 01:20
Acute Kidney Injury V: Interprofessional Care
 01:28
Chronic Kidney Disease III: Interprofessional Care
 01:24
Diagnosing Acidosis and Alkalosis
First, the pH level is assessed to determine whether the blood pH is normal (7.35–7.45), low (acidosis), or high (alkalosis).
Next, the PCO2 and...
 01:28
Compensation Mechanisms
Respiratory Compensation
This mechanism addresses metabolic-induced pH imbalances by adjusting breathing rates. Respiratory compensation begins within minutes of detecting a pH...
 01:18
Chronic Kidney Disease IV: Nursing Management