Related Experiment Video
Updated: Dec 31, 2025
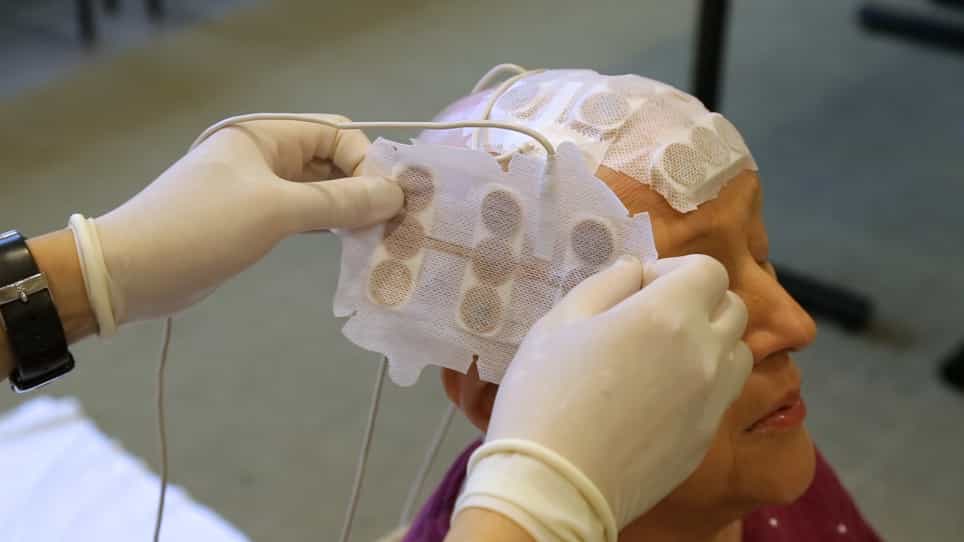

The Clinical Application of Tumor Treating Fields Therapy in Glioblastoma
Published on: April 16, 2019
Optimal adjuvant therapy in elderly glioblastoma: results from a systematic review and network meta-analysis
Babusha Kalra1, Sadhana Kannan2, Tejpal Gupta3
1Department of Radiation Oncology, ACTREC, Tata Memorial Centre, Homi Bhabha National Institute (HBNI), Kharghar, Navi Mumbai, 410210, India.

Background:
There exists lack of consensus worldwide regarding the most optimal adjuvant therapy regimen in elderly patients with newly-diagnosed glioblastoma (GBM).
Purpose:
To identify the most optimal adjuvant therapy regimen in elderly GBM patients through systematic review and network meta-analysis.
Methods:
Prospective trials randomly assigning elderly GBM patients post-operatively to any adjuvant therapy regimen were included. The primary outcome measure was overall survival. Numbers of events, patients at-risk, and censored patients for survival were estimated from Kaplan-Meier survival curves in the interval of 0-12 months. The total person-time at risk and the mortality × 100 person-months was also estimated. The relative ranking probability of each treatment and rankograms were used to estimate the hierarchy of each intervention in terms of overall survival. The mean rank values and the surface under the cumulative ranking (SUCRA) curves were also calculated.
Results:
A systematic literature search identified 1278 abstracts, that were screened to retrieve full-text manuscripts of potentially eligible articles. After detailed assessment, data from 1569 patients in 7 randomized controlled trials (RCTs) treated with one of following regimens was extracted and analyzed: normofractionated radiotherapy (RT) delivered over 5.5-6 weeks; moderately hypofractionated RT (2-3 weeks) either alone or in combination with temozolomide or bevacizumab; extremely hypofractionated RT (1-week); temozolomide monotherapy; and best supportive care alone. In terms of overall survival, moderately hypofractionated RT (3-weeks) with concurrent and adjuvant temozolomide emerged as the best and second-best adjuvant therapy option with 81% probability and 99.1% probability respectively. Using SUCRA, the surface area for moderately hypofractionated RT (3-weeks) with concurrent and adjuvant temozolomide reached almost 100%, confirming it as the best intervention. As expected, best supportive care alone was ranked as the worst treatment strategy.
Conclusion:
Moderately hypofractionated RT (3-weeks) with concurrent and adjuvant temozolomide is the most optimal and preferred adjuvant therapeutic regimen in elderly GBM.


Related Concept Videos
 01:27
Pharmacodynamics in Geriatric Patients: Effects of Age
 01:15
Drug Dosing: Geriatric Patients
 01:18
Pharmacokinetics in Geriatric Patients: Effect of Age on Drug Metabolism
 01:22
Pharmacokinetics in Geriatric Patients: Effect of Age on Drug Absorption
 01:00
Pharmacokinetics in Geriatric Patients: Effect of Age on Drug Distribution
 01:27
Open Angle Glaucoma: Treatment
Drugs such as carbonic anhydrase inhibitors, α2- and...