Related Experiment Video
Updated: Dec 31, 2025
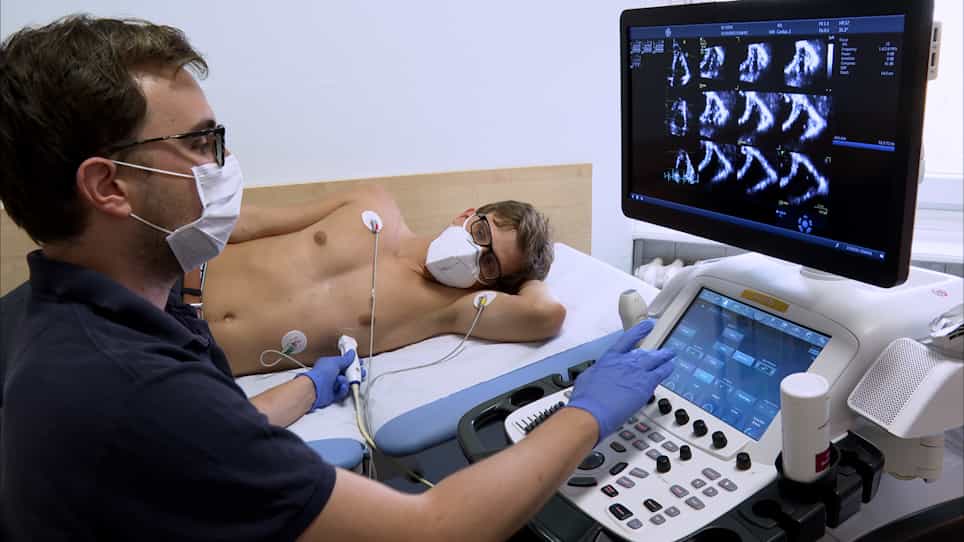

Morphological and Functional Assessment of the Right Ventricle Using 3D Echocardiography
Published on: October 28, 2020
Bridging the gap between hypertrabeculation phenotype, noncompaction phenotype and left ventricular noncompaction
Vittoria Vergani1, Davide Lazzeroni2, Giovanni Peretto3
1Department of Clinical Cardiology, IRCCS San Raffaele Hospital and University.

Insights
Left ventricular noncompaction (LVNC) is a heart condition with excessive trabeculation. This review offers a diagnostic algorithm to differentiate LVNC from benign hypertrabeculation, aiding clinical decision-making.
Area of Science:
- Cardiology
- Cardiovascular Medicine
- Medical Diagnostics
Background:
- Left ventricular noncompaction (LVNC) is a cardiomyopathy defined by excessive cardiac trabeculation and deep recesses.
- While hypertrabeculation is linked to heart failure and arrhythmias, it alone does not confirm LVNC.
- Current diagnostic tools are insufficient to distinguish between asymptomatic hypertrabeculation and actual LVNC.
Purpose of the Study:
- To review existing literature on diagnostic criteria for LVNC.
- To develop a practical diagnostic algorithm for differentiating LVNC phenotypes.
- To aid clinicians in distinguishing between hypertrabeculation, non-compaction phenotype, and LVNC cardiomyopathy.
Main Methods:
- Comprehensive literature review of studies on LVNC diagnostic criteria.
- Analysis of parameters used to predict adverse cardiovascular events in LVNC.
- Development of a simplified diagnostic algorithm based on reviewed criteria.
Main Results:
- Hypertrabeculation alone is not a definitive diagnostic marker for LVNC.
- Existing literature lacks clear consensus on differentiating LVNC from hypertrabeculation.
- An accessible algorithm is proposed to aid in clinical differentiation.
Conclusions:
- A clear distinction between hypertrabeculation and LVNC is crucial for accurate diagnosis and risk stratification.
- The proposed algorithm aims to provide physicians with an effective tool for LVNC diagnosis.
- Further validation of the diagnostic algorithm is warranted to improve patient outcomes.
Abstract:
Left ventricular noncompaction (LVNC) is an increasingly recognised cardiomyopathy characterised by excessive trabeculation and deep intertrabecular recesses in direct communication with the left ventricular cavity. In LVNC, hypertrabeculation has been associated with heart failure, ventricular arrhythmia, and systemic thromboembolism. However, hypertrabeculation alone is not sufficient to define a subject as at risk for such complications and thus should not be sufficient to diagnose LVNC. Despite several studies having investigated parameters to predict adverse cardiovascular events, physicians have no effective tools to differentiate between clinically silent hypertrabeculation and LVNC. The aim of this paper was to review literature on LVNC diagnostic criteria and to provide an easy and accessible diagnostic algorithm to distinguish between hypertrabeculation phenotype, non-compaction phenotype and LVNC cardiomyopathy.
More Related Videos
 03:45
Investigating the Pathogenesis of MYH7 Mutation Gly823Glu in Familial Hypertrophic Cardiomyopathy using a Mouse Model
Published on: August 8, 2022
 08:28
Analysis of Congenital Heart Defects in Mouse Embryos Using Qualitative and Quantitative Histological Methods
Published on: March 10, 2020
Related Concept Videos
 01:29
Cardiomyopathy III: Hypertrophic Cardiomyopathy
 01:29
Cardiomyopathy V: Interprofessional Care
 01:29
Cardiomyopathy IV: Restrictive Cardiomyopathy
 01:30
Cardiomyopathy II: Dilated Cardiomyopathy
 01:25
Cardiomyopathy I: Introduction and Classification
 01:27
Mitral Valve Prolapse I: Introduction