Related Experiment Video
Updated: Dec 31, 2025


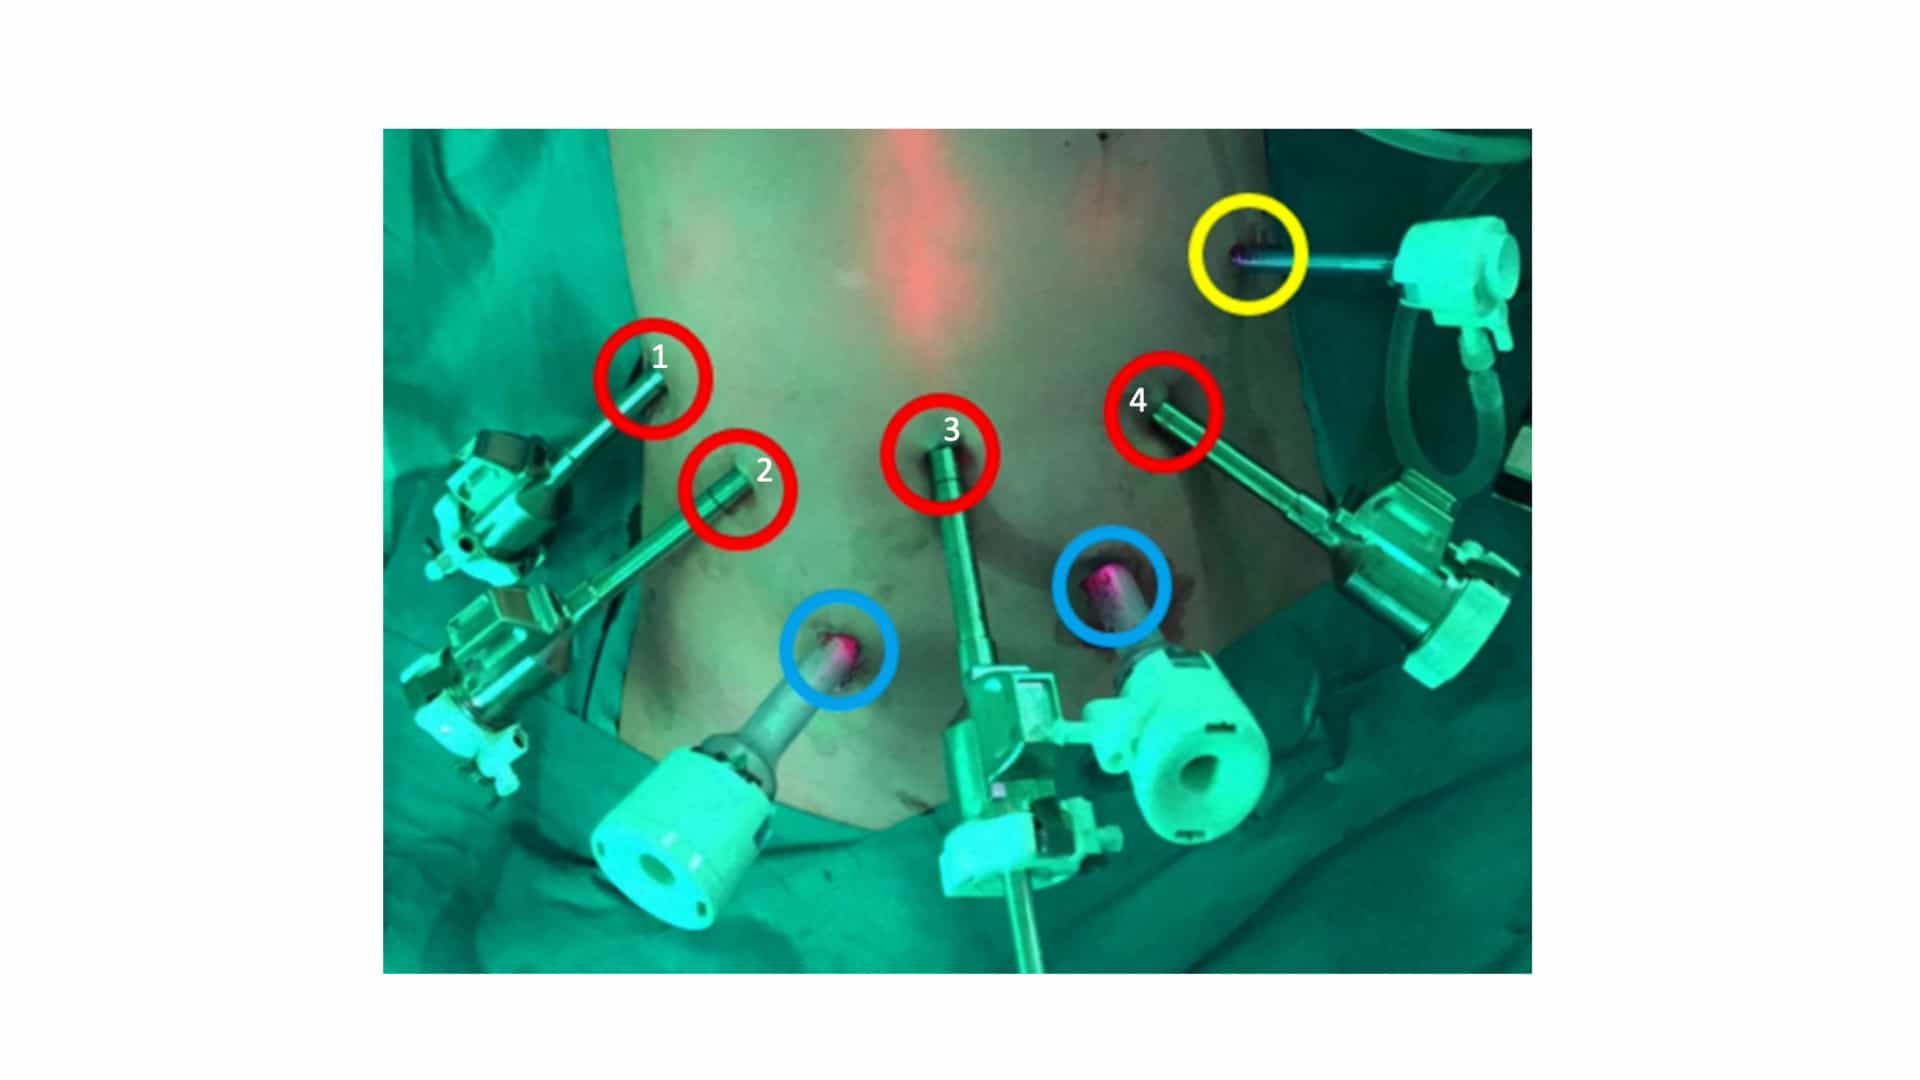
Clinical Application of Single-Surgeon, Three-Port, Laparoscopic Resection for Colorectal Cancer with Natural Orifice Specimen Extraction
Published on: March 24, 2023
Identification of patients eligible for discharge within 48 h of colorectal resection
F Grass1,2, M Hübner2, K L Mathis1
1Division of Colon and Rectal Surgery, Mayo Clinic, Rochester, Minnesota, USA.

Background:
This study aimed to identify patients eligible for a 48-h stay after colorectal resection, to provide guidance for early discharge planning.
Methods:
A bi-institutional retrospective cohort study was undertaken of consecutive patients undergoing major elective colorectal resection for benign or malignant pathology within a comprehensive enhanced recovery pathway between 2011 and 2017. Overall and severe (Clavien-Dindo grade IIIb or above) postoperative complication and readmission rates were compared between patients who were discharged within 48 h and those who had hospital stay of 48 h or more. Multinominal logistic regression analysis was performed to ascertain significant factors associated with a short hospital stay (less than 48 h).
Results:
In total, 686 of 5122 patients (13·4 per cent) were discharged within 48 h. Independent factors favouring a short hospital stay were age below 60 years (odds ratio (OR) 1·34; P = 0·002), ASA grade less than III (OR 1·42; P = 0·003), restrictive fluid management (less than 3000 ml on day of surgery: OR 1·46; P < 0·001), duration of surgery less than 180 min (OR 1·89; P < 0·001), minimally invasive approach (OR 1·92; P < 0·001) and wound contamination grade below III (OR 4·50; P < 0·001), whereas cancer diagnosis (OR 0·55; P < 0·001) and malnutrition (BMI below 18 kg/m2 : OR 0·42; P = 0·008) decreased the likelihood of early discharge. Patients with a 48-h stay had fewer overall (10·8 per cent versus 30·6 per cent in those with a longer stay; P < 0·001) and fewer severe (2·6 versus 10·2 per cent respectively; P < 0·001) complications, and a lower readmission rate (9·0 versus 11·8 per cent; P = 0·035).
Conclusion:
Early discharge of selected patients is safe and does not increase postoperative morbidity or readmission rates. In these patients, outpatient colorectal surgery should be feasible on a large scale with logistical optimization.

Related Concept Videos
 01:26
Endoscopic Procedures IV: Sigmoidoscopy and Laproscopy
Sigmoidoscopy
Sigmoidoscopy is a diagnostic procedure that uses a flexible sigmoidoscope equipped with a light source and camera to examine the rectum and sigmoid colon. The procedure involves inserting the tube through the anus...
 01:29
Appendicitis-II: Diagnostic Studies and Management
Diagnosing Appendicitis
It requires a multifaceted approach, starting with a detailed physical examination to pinpoint the location and nature of the pain and identify any associated symptoms. Laboratory tests play a crucial role. A complete Blood Count (CBC) typically reveals leukocytosis (an increased number of...
 01:25
Endoscopic Procedures II: Colonoscopy
 01:31
Discharge Summary Forms
Here's a detailed look at the key components and guidelines for preparing a discharge summary:
 01:22
Aneurysm IV: Nursing Management