

Characterization of Structural Changes in Arrhythmogenic Right Ventricular Cardiomyopathy With Recurrent Ventricular
David F Briceño1, Jackson J Liang1, Yasuhiro Shirai1
1Electrophysiology Section, Cardiovascular Division, Hospital of the University of Pennsylvania, Philadelphia.

Background:
Data characterizing structural changes of arrhythmogenic right ventricular (RV) cardiomyopathy are limited.
Methods:
Patients presenting with left bundle branch block ventricular tachycardia in the setting of arrhythmogenic RV cardiomyopathy with procedures separated by at least 9 months were included.
Results:
Nineteen consecutive patients (84% males; mean age 39±15 years [range, 20-76 years]) were included. All 19 patients underwent 2 detailed sinus rhythm electroanatomic endocardial voltage maps (average 385±177 points per map; range, 93-847 points). Time interval between the initial and repeat ablation procedures was mean 50±37 months (range, 9-162). No significant progression of voltage was observed (bipolar: 38 cm2 [interquartile range (IQR), 25-54] versus 53 cm2 [IQR, 25-65], P=0.09; unipolar: 116 cm2 [IQR, 61-209] versus 159 cm2 [IQR, 73-204], P=0.36) for the entire study group. There was a significant increase in RV volumes (percentage increase, 28%; 206 mL [IQR, 170-253] versus 263 mL [IQR, 204-294], P<0.001) for the entire study population. Larger scars at baseline but not changes over time were associated with a significant increase in RV volume (bipolar: Spearman ρ, 0.6965, P=0.006; unipolar: Spearman ρ, 0.5743, P=0.03). Most patients with progressive RV dilatation (8/14, 57%) had moderate (2 patients) or severe (6 patients) tricuspid regurgitation recorded at either initial or repeat ablation procedure.
Conclusions:
In patients with arrhythmogenic RV cardiomyopathy presenting with recurrent ventricular tachycardia, >10% increase in RV endocardial surface area of bipolar voltage consistent with scar is uncommon during the intermediate term. Most recurrent ventricular tachycardias are localized to regions of prior defined scar. Voltage indexed scar area at baseline but not changes in scar over time is associated with progressive increase in RV size and is consistent with adverse remodeling but not scar progression. Marked tricuspid regurgitation is frequently present in patients with arrhythmogenic RV cardiomyopathy who have progressive RV dilation.


Related Concept Videos
 01:25
ECG Interpretation of Arrhythmias II: Atrial, Junctional and Ventricular Arrhythmias
 01:30
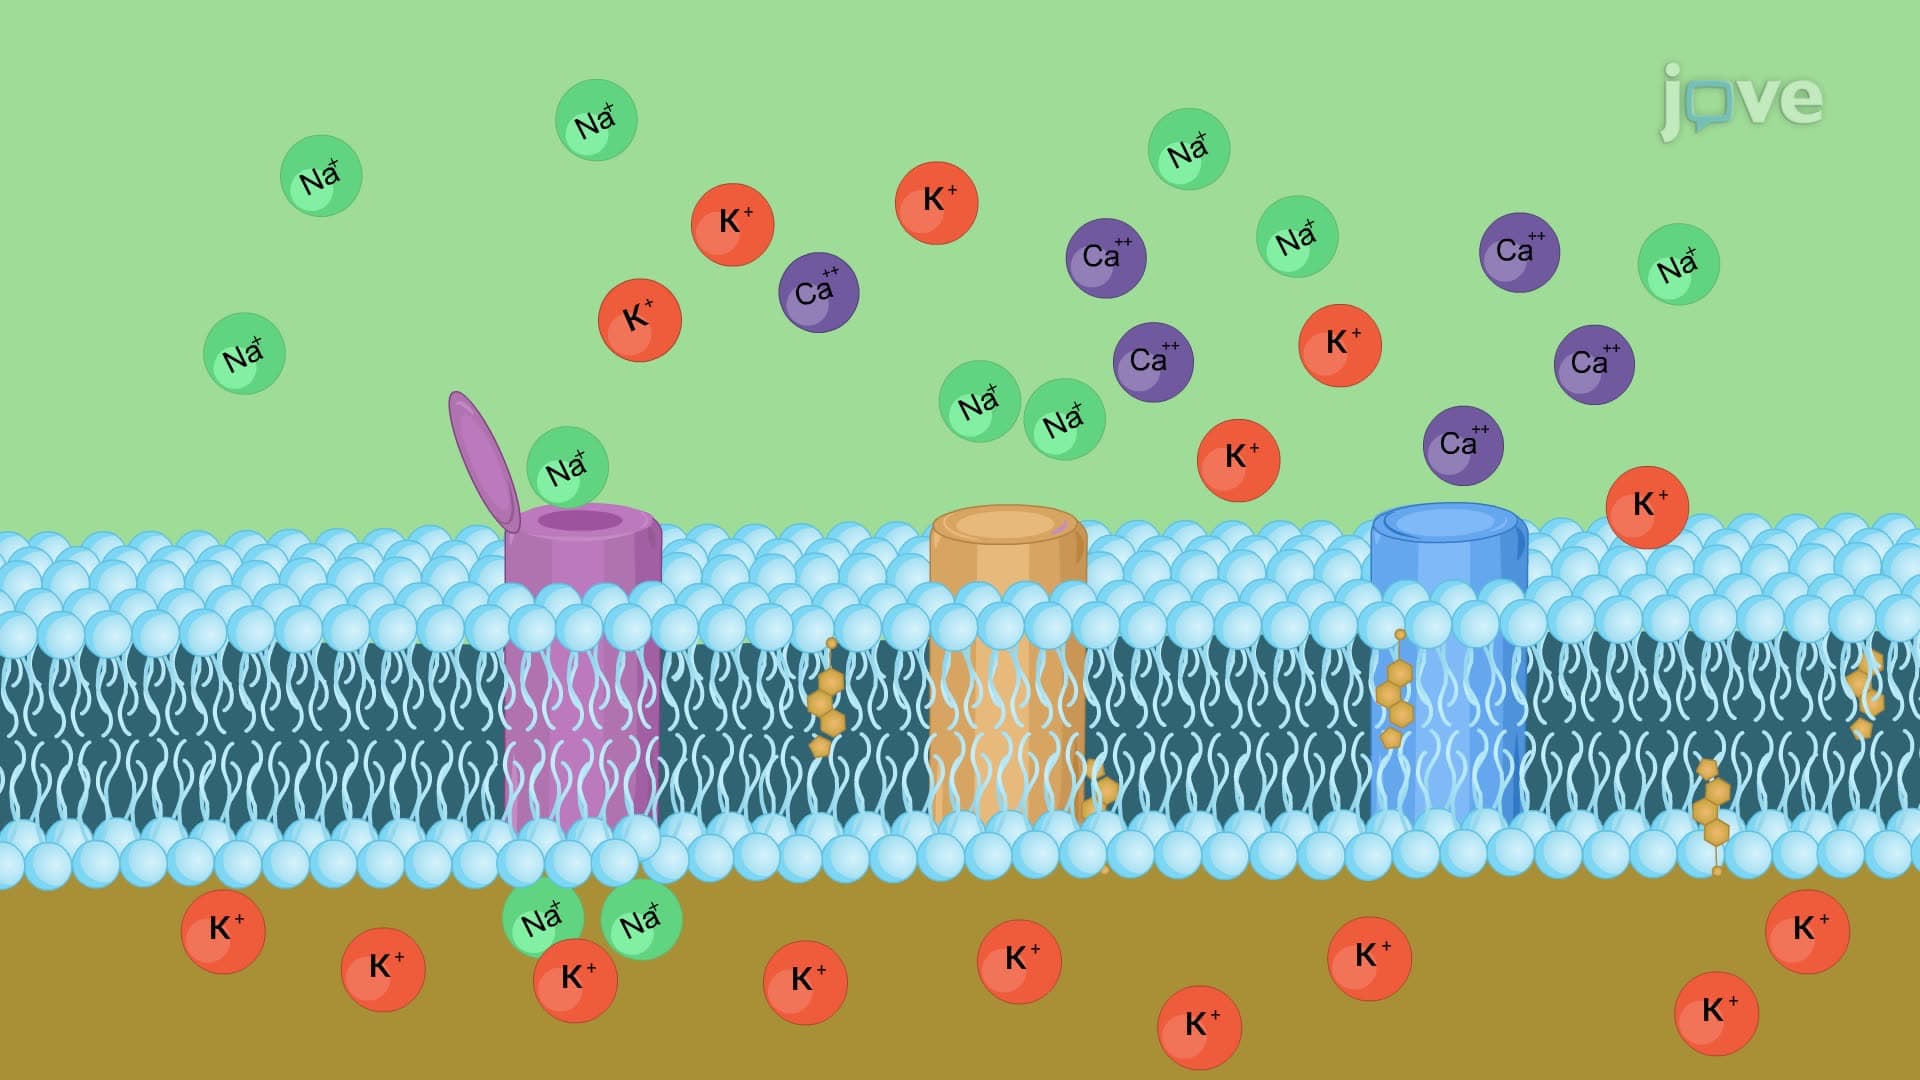
Cardiac Action Potential
The cardiac action potential process involves a series of phases characterized by the movement of ions across the cardiac cell membranes, leading to the depolarization and repolarization of the cardiac myocytes.
Ionic Basis of Cardiac Action Potentials
 01:29
Dysrhythmias III: Characteristics of Dysrhythmias
 01:19
Electrophysiology of Normal Cardiac Rhythm
 01:28
Mechanism of Cardiac Arrhythmias
 01:28
Dysrhythmias II: Classification of Tachyarrhythmias