Related Experiment Video
Updated: Dec 31, 2025

A Rapidly Incremented Tethered-Swimming Maximal Protocol for Cardiorespiratory Assessment of Swimmers
Published on: January 28, 2020
Multilevel allometric modelling of maximum cardiac output, maximum arteriovenous oxygen difference, and peak oxygen
1Children's Health and Exercise Research Centre, University of Exeter, St Lukes Campus, Heavitree Road, Exeter, EX1 2LU, UK. N.Armstrong@exeter.ac.uk.

Purposes:
To investigate longitudinally (1) the contribution of morphological covariates to explaining the development of maximum cardiac output ([Formula: see text] max) and maximum arteriovenous oxygen difference (a-vO2 diff max), (2) sex differences in [Formula: see text] max and a-vO2 diff max once age, maturity status, and morphological covariates have been controlled for, and, (3) the contribution of concurrent changes in morphological and cardiovascular covariates to explaining the sex-specific development of peak oxygen uptake ([Formula: see text]).
Methods:
Fifty-one (32 boys) 11-13-year-olds had their peak [Formula: see text], maximum heart rate (HR max), [Formula: see text] max, and a-vO2 diff max determined during treadmill running on three annual occasions. The data were analysed using multilevel allometric modelling.
Results:
There were no sex differences in HR max which was not significantly (p > 0.05) correlated with age, morphological variables, or peak [Formula: see text]. The best-fit models for [Formula: see text] max and a-vO2 diff max were with fat-free mass (FFM) as covariate with age, maturity status, and haemoglobin concentration not significant (p > 0.05). FFM was the dominant influence on the development of peak [Formula: see text]. With FFM controlled for, the introduction of either [Formula: see text] max or a-vO2 diff max to multilevel models of peak [Formula: see text] resulted in significant (p < 0.05) additional contributions to explaining the sex difference.
Conclusions:
(1) With FFM controlled for, there were no sex differences in [Formula: see text] max or a-vO2 diff max, (2) FFM was the dominant influence on the development of peak [Formula: see text], and (3) with FFM and either [Formula: see text] max or a-vO2 diff max controlled for, there remained an unresolved sex difference of ~ 4% in peak [Formula: see text].
Related Concept Videos
 01:19
Cardiac Output I:Effect of Heart Rate on Cardiac Output
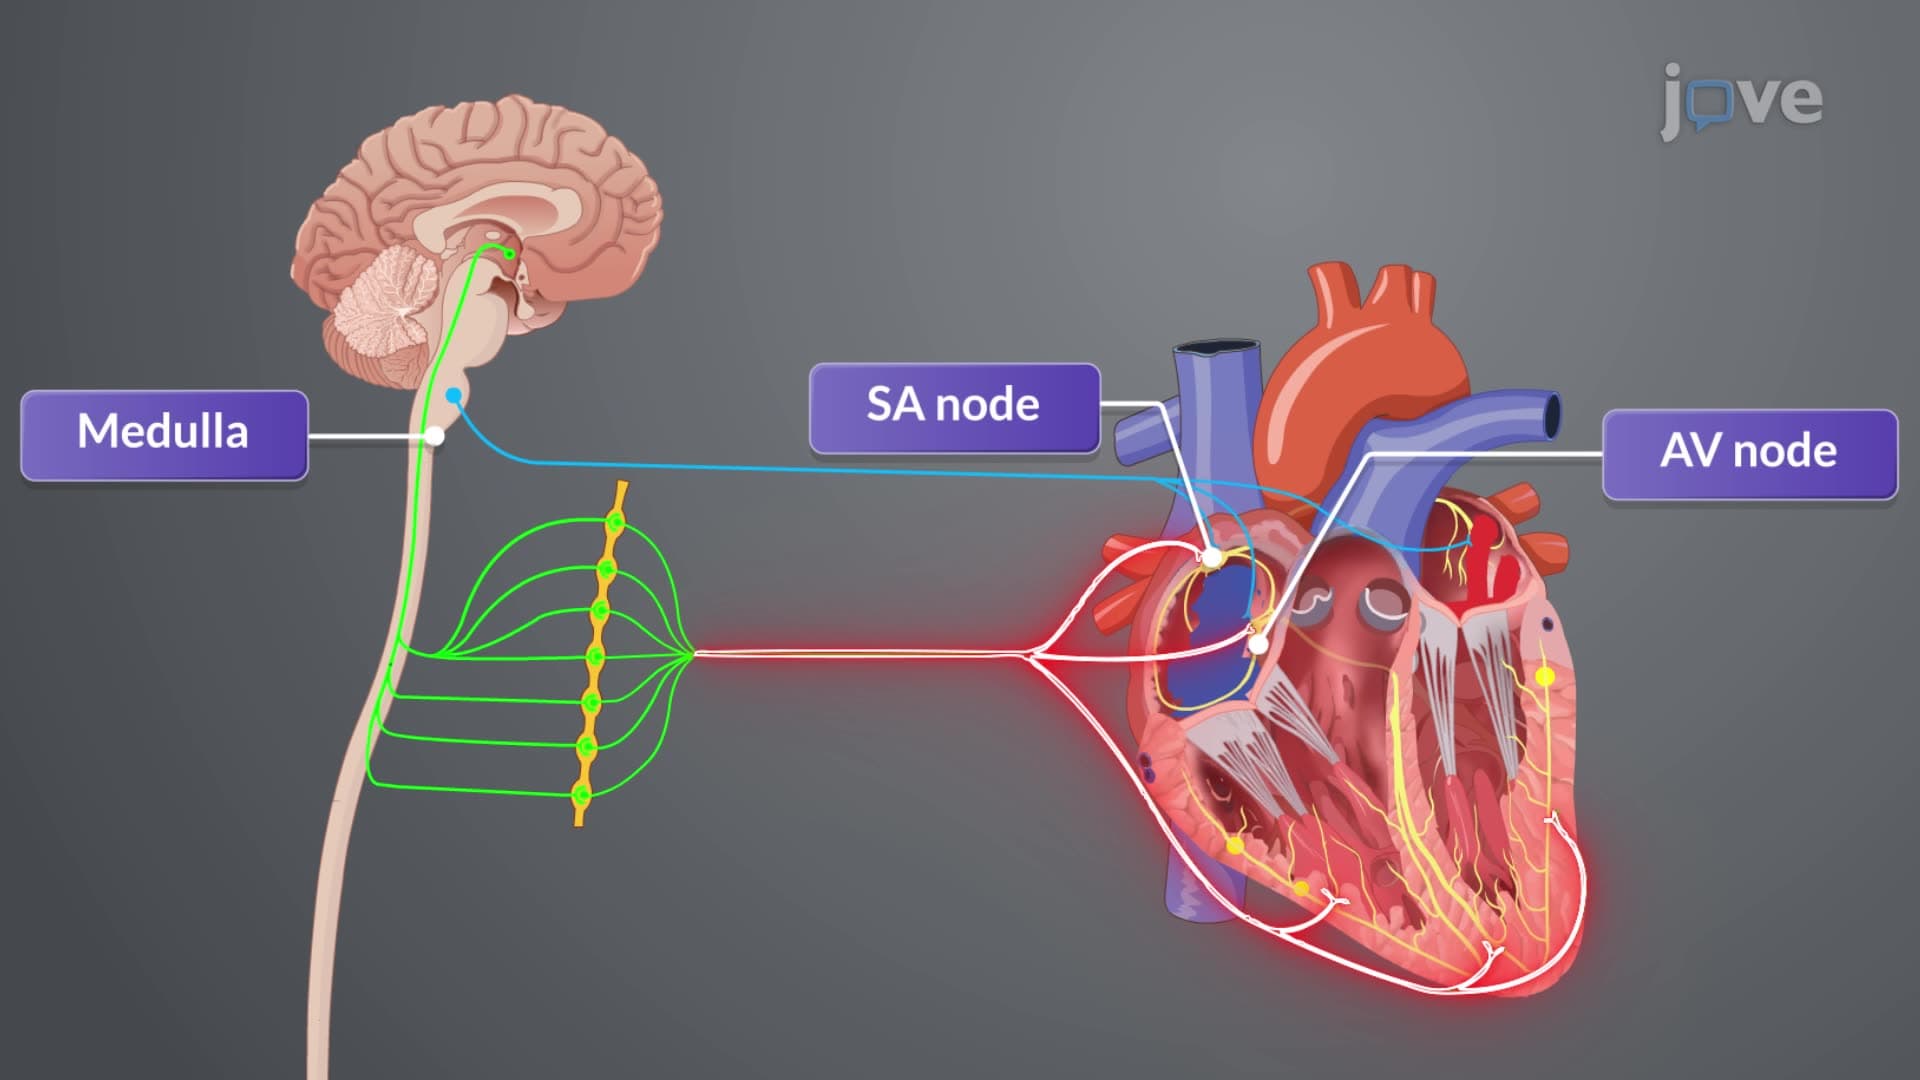
Cardiac output (CO) refers to the total amount of blood ejected by one of the ventricles in liters per minute (L/min). In a resting adult, CO ranges from 5 to 6 L/min, adjusting according to the body's metabolic requirements.
Effect of Heart Rate on Cardiac Output
Cardiac output adapts to metabolic demands during stress, physical activity, or illness. The autonomic nervous system regulates heart rate via the sinoatrial node. The parasympathetic nervous system decreases heart...
 01:17
Exercise and Cardiac Output
Sustained exercise increases the muscles' oxygen demand, which can be...
 01:11
Cardiac Output and Stroke Volume
In an average resting adult male, the typical cardiac...
 01:22
Cardiac Output II: Effect of Stroke Volume on Cardiac Output
Preload
Preload refers to the initial elongation of the cardiac myocytes before contraction and is related to the volume of blood filling the heart at the end of diastole, or end-diastolic volume. The...
 01:29
Oxygen Requirements and Growth Patterns
 01:20
Blood Studies for Cardiovascular System I: Cardiac Biomarkers
The essential diagnostic tools for detecting myocardial necrosis and monitoring individuals suspected of having acute coronary syndrome (ACS) include:
Troponins
Troponins, particularly cardiac troponins I and T, are the most precise and sensitive markers of myocardial injury. They are detectable within 4-6 hours of myocardial injury and remain...