Related Experiment Video
Updated: Dec 27, 2025
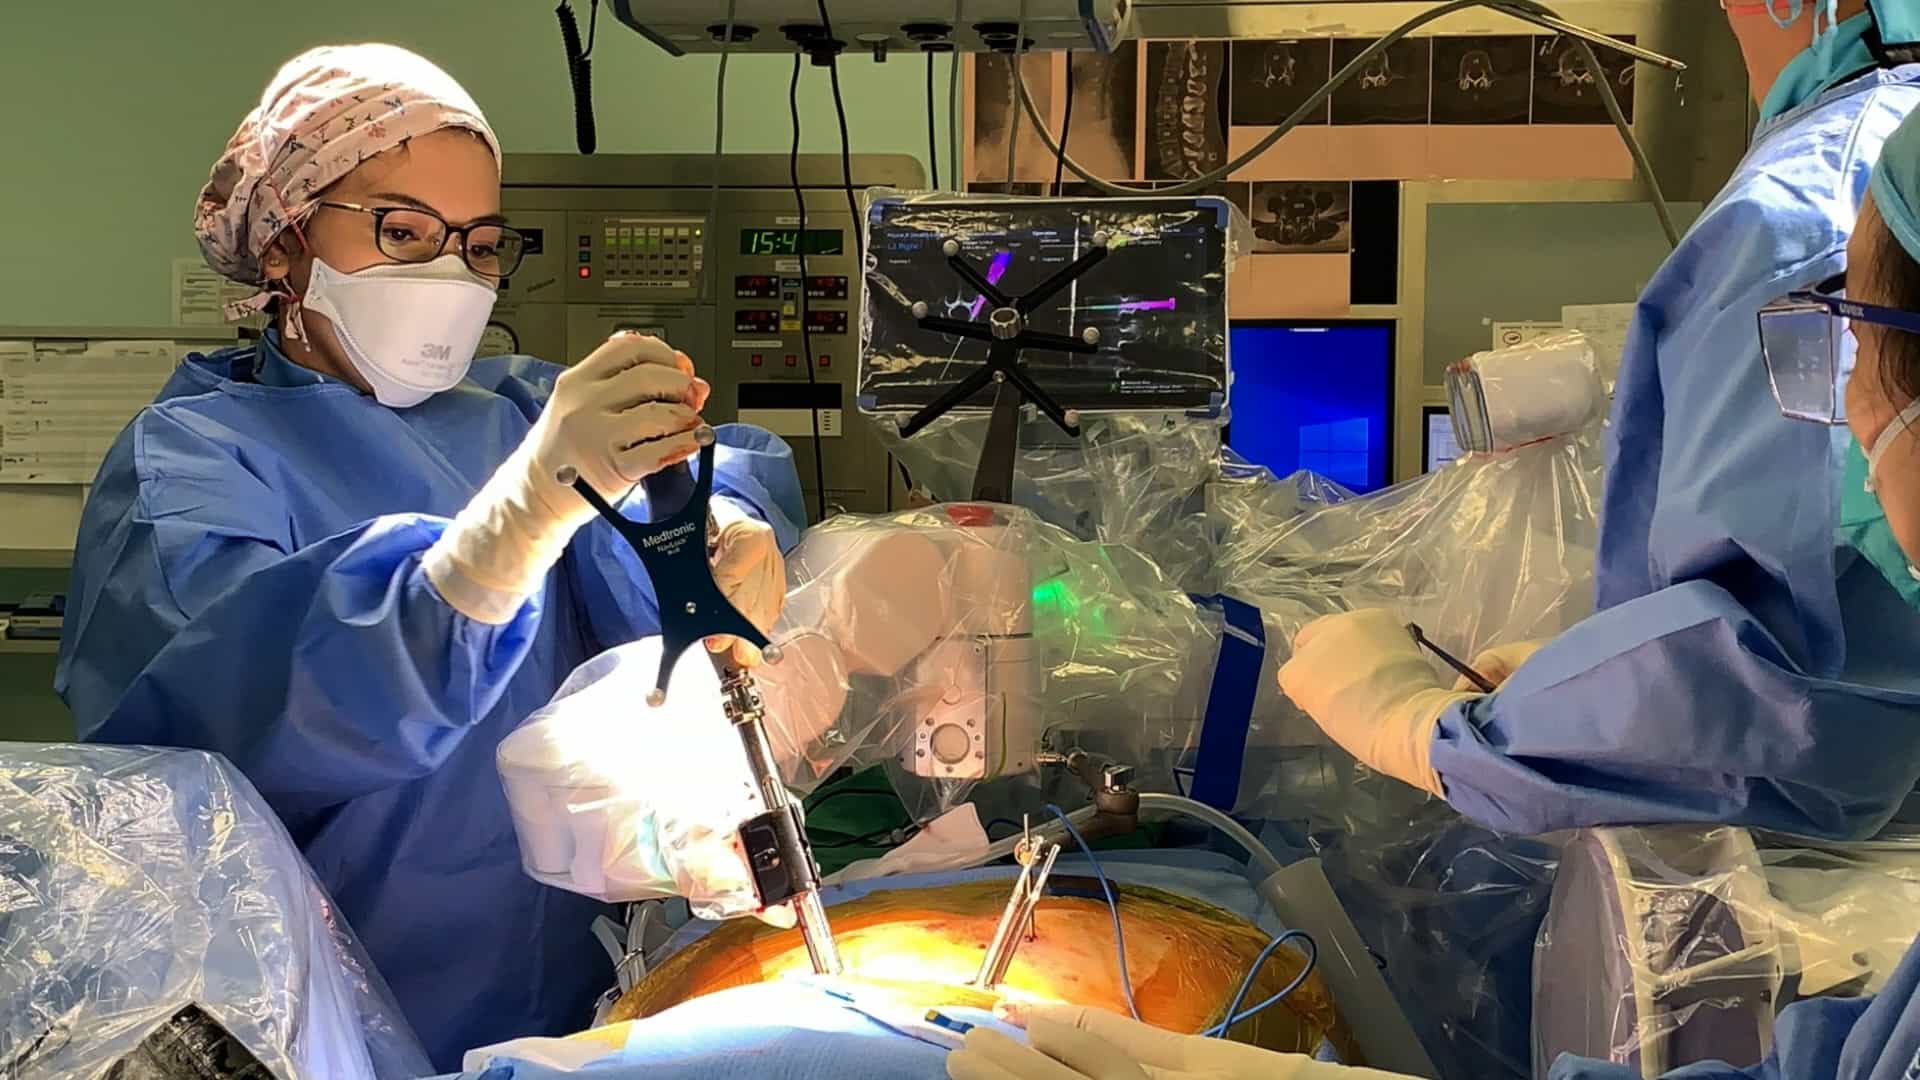
Multilevel Oblique Lumbar Interbody Fusion in Degenerative Lumbar Disc Disease with Instability
Published on: July 25, 2025
Sacral Dysmorphism and Lumbosacral Transitional Vertebrae (LSTV) Review
David M Matson1, Lauren M Maccormick1, Jonathan N Sembrano1
1Department of Orthopaedic Surgery, University of Minnesota, Minneapolis, Minnesota.

Background:
Anatomic variation in the relationship between the lumbar spine and sacrum was first described in the literature nearly a century ago and continues to play an important role in spine deformity, low back pain (LBP), and pelvic trauma. This review will focus on the clinical and surgical implications of abnormal lumbosacral anatomy in the context of sacroiliac joint (SIJ) disease, spine deformity, and pelvic trauma.
Methods:
A PubMed search using the keywords "lumbosacral transitional vertebrae," "LSTV," "transitional lumbosacral vertebrae," "TLSV," and "sacral dysmorphism" was performed. The articles presented here were evaluated by the authors.
Clinical Significance:
The prevalence of LSTV varies widely in the literature from 3.9-% to 35.6% in the spine literature, and sacral dysmorphism is described in upwards of 50% of the population in the trauma literature. The relationship between LSTV and LBP is well established. While there is no agreed-on etiology, the source of pain is multifactorial and may be related to abnormal biomechanics and alignment, disc degeneration, and arthritic changes.
Surgical Implications:
Understanding abnormal lumbosacral anatomy is crucial for preoperative planning of SIJ fusion, spine deformity, and pelvic trauma surgery. LSTV can alter spinopelvic parameters crucial in planning spine deformity correction. Traditional safe zones for sacroiliac screw placement do not apply in the first sacral segment in sacral dysmorphism and risk iatrogenic nerve injury.
Conclusions:
LSTV and sacral dysmorphism are common anatomic variants found in the general population. Abnormal lumbosacral anatomy plays a significant role in clinical evaluation of LBP and surgical planning in SIJ fusion, spine deformity, and pelvic trauma. Further studies evaluating the influence of abnormal lumbosacral anatomy on LBP and surgical technique would help guide treatment for these patients.
More Related Videos
 07:44
Evaluation of Patients' Posture and Gait Profile After Lumbar Fusion Surgery by Video Rasterstereography and Treadmill Gait Analysis
Published on: March 23, 2019
 10:09
Transtubular Endoscopic Posterolateral Decompression for L5-S1 Lumbar Lateral Disc Herniation
Published on: October 14, 2022
Related Concept Videos
 01:16
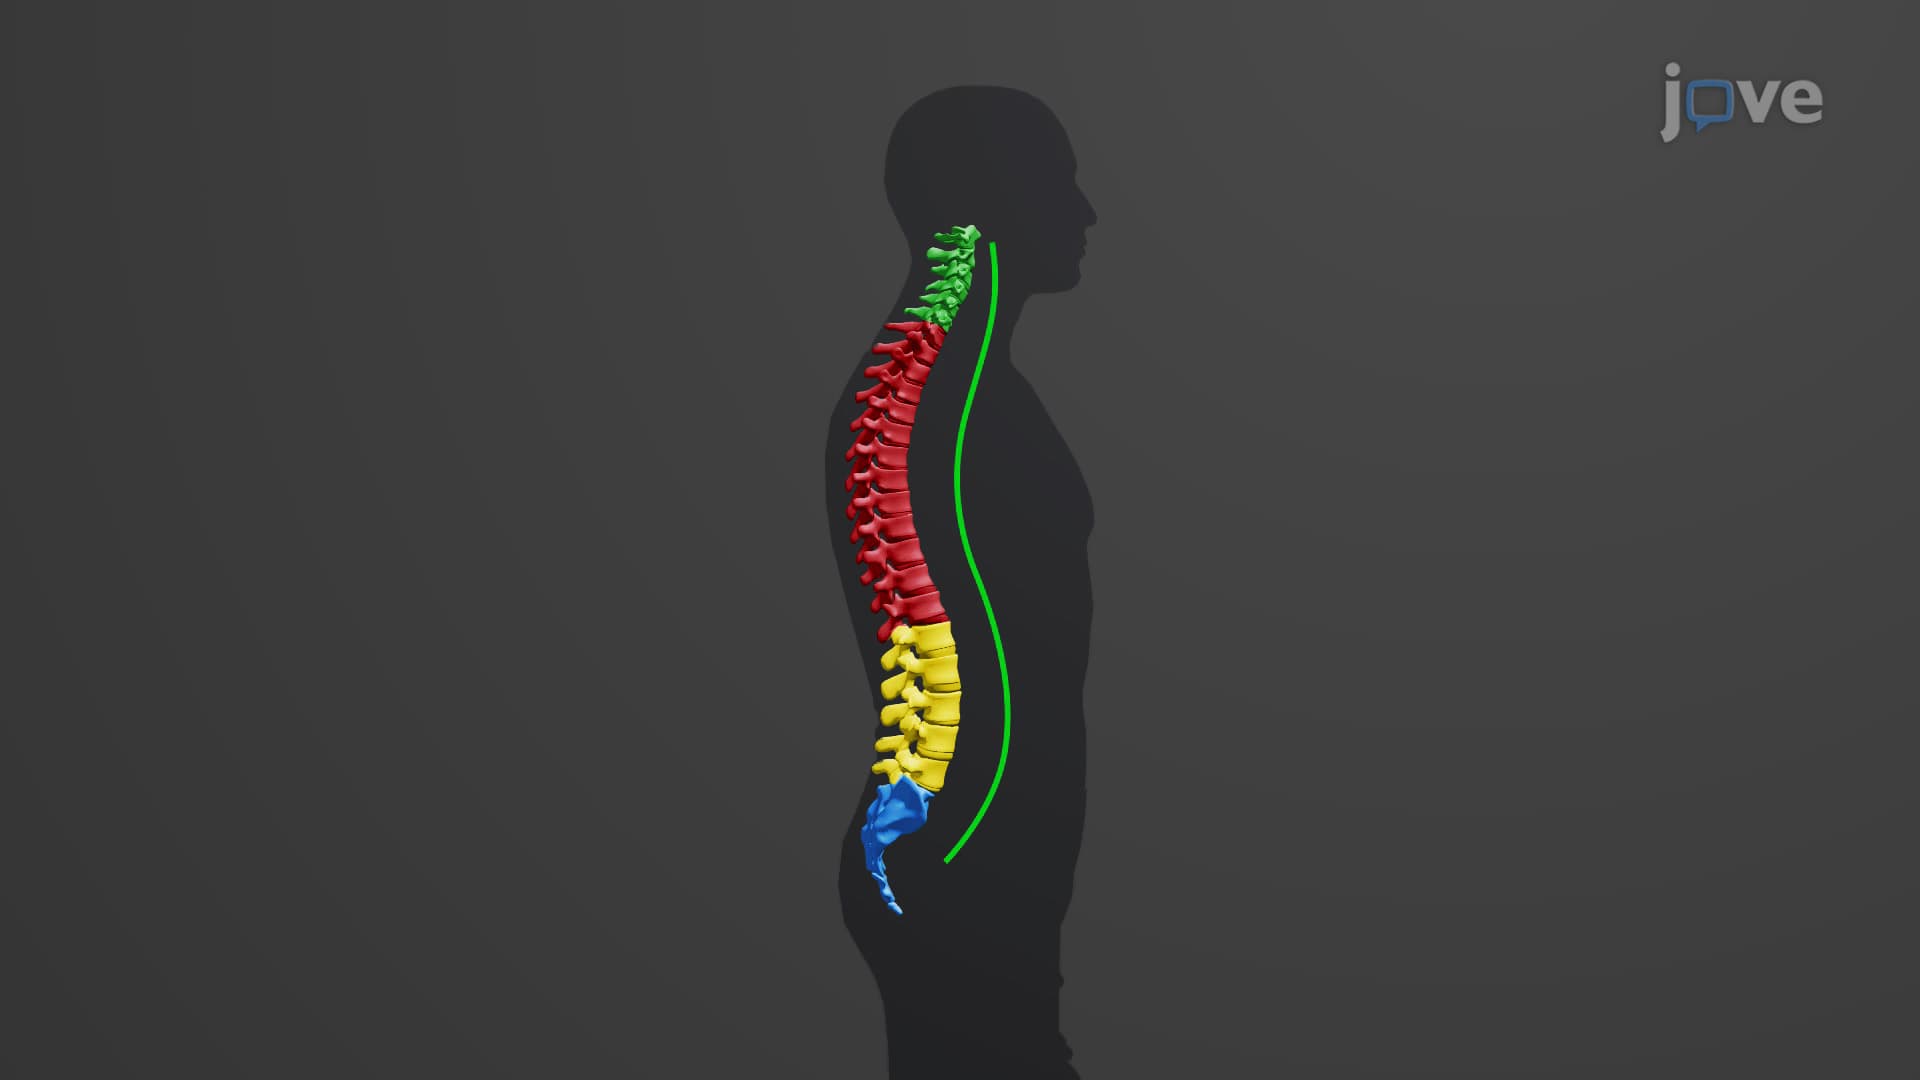
Vertebral Column: Regions and Curvature
Regions of the Vertebral Column
In an adult, the spine is subdivided into five regions: the cervical, the thoracic, the lumbar, the sacral, and the coccygeal region. The spine initially develops as a series of 33 vertebrae; after 20 years of age, the nine bones in the sacral region, five sacral, and four coccygeal bones fuse to form...
 01:30
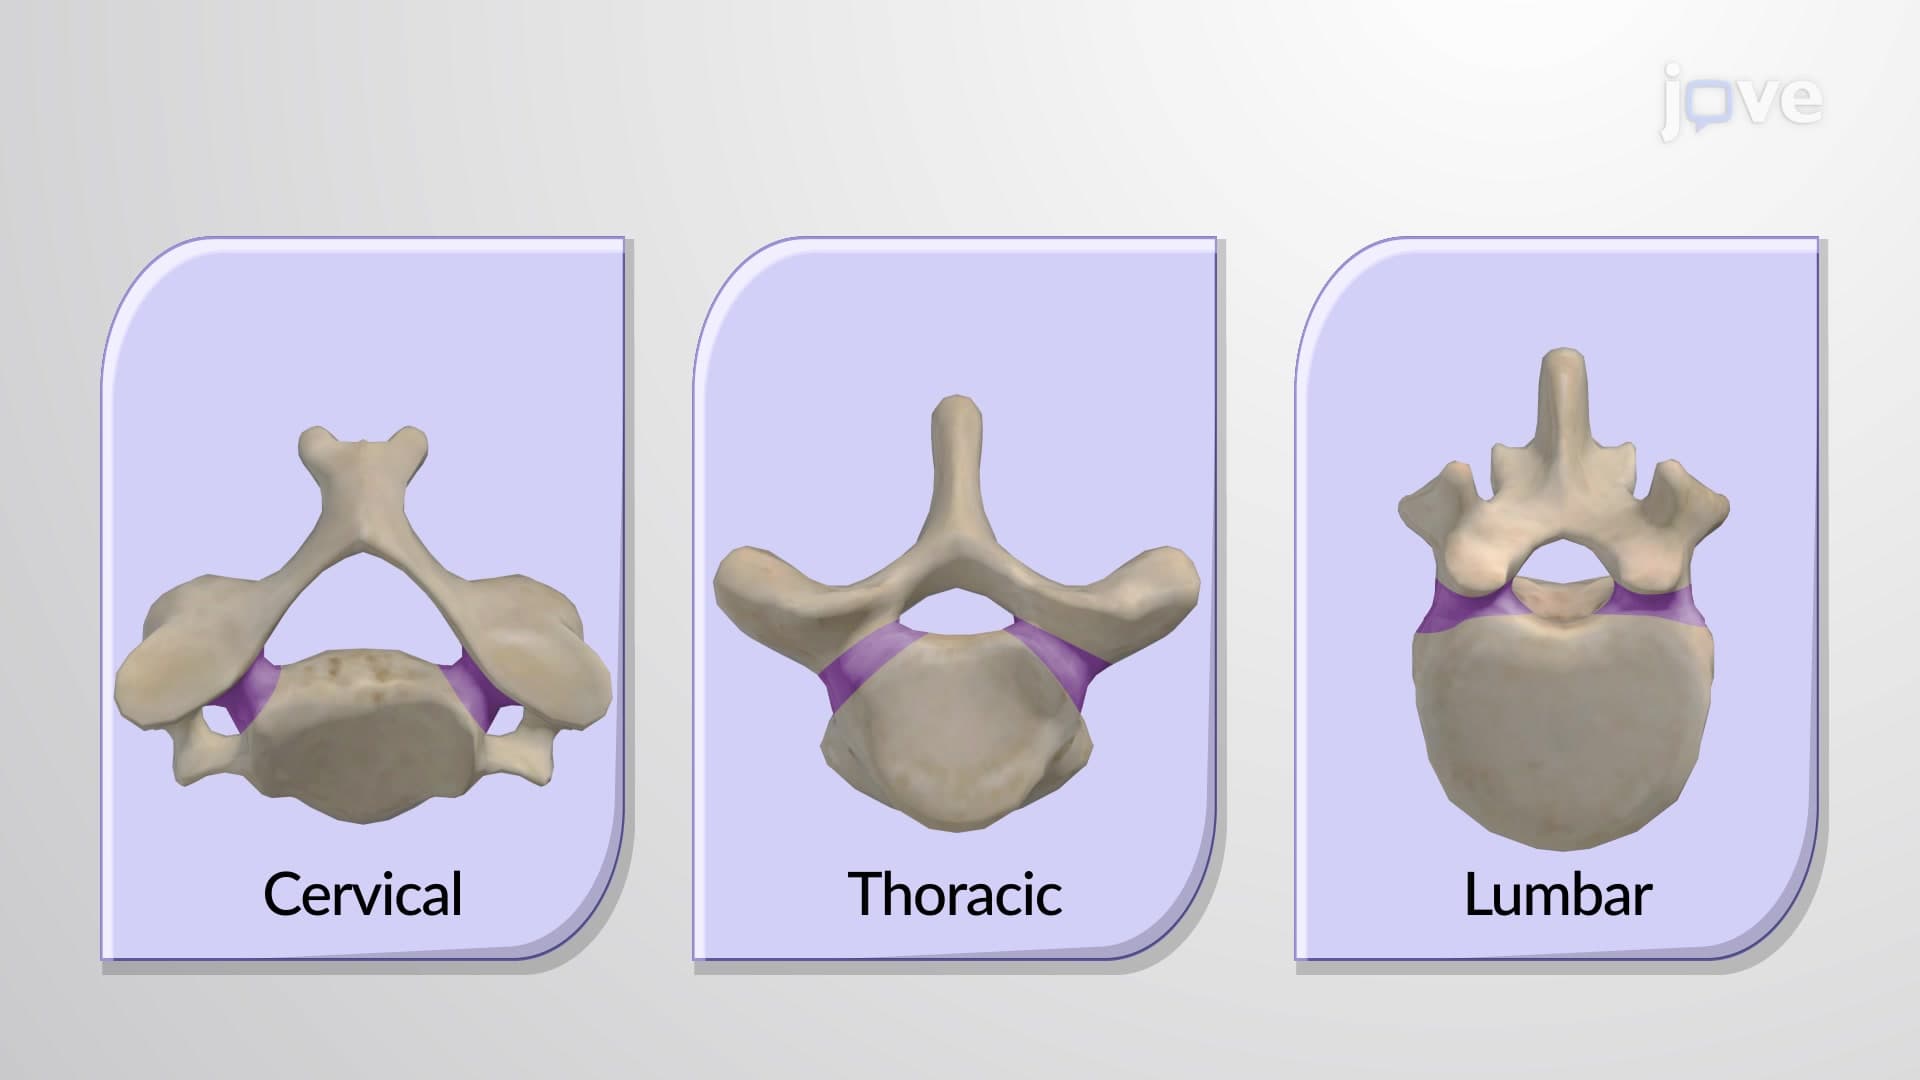
General Structure of a Vertebra
 01:15
Spinal Cord: Gross Anatomy