Related Experiment Video
Updated: Dec 26, 2025


Laparoscopic Choledochal Cyst Excision and Roux-en-Y Choledochojejunostomy in Adults
Published on: February 28, 2025
Choledochal cyst mimicker-When small bowel length matters
Ammiel Arra1, Nigel Bascombe2, Barrie Landreth-Smith3
1Department of Surgery, San Fernando General Hospital, San Fernando, Trinidad and Tobago.

Objective:
Due to the risk of malignancy, the established management of choledochal cysts mandates bile duct excision and biliary reconstruction. While the reconstructive procedure of choice for most surgeons has traditionally been hepatico-jejunostomy, this may not be feasible in selected cases due to immobility or inadequacy of the jejunum. The following case will outline the management of a 32-year-old woman with short bowel syndrome, who was diagnosed with choledocholithiasis and a type 1 choledochal cyst.
Method And Materials:
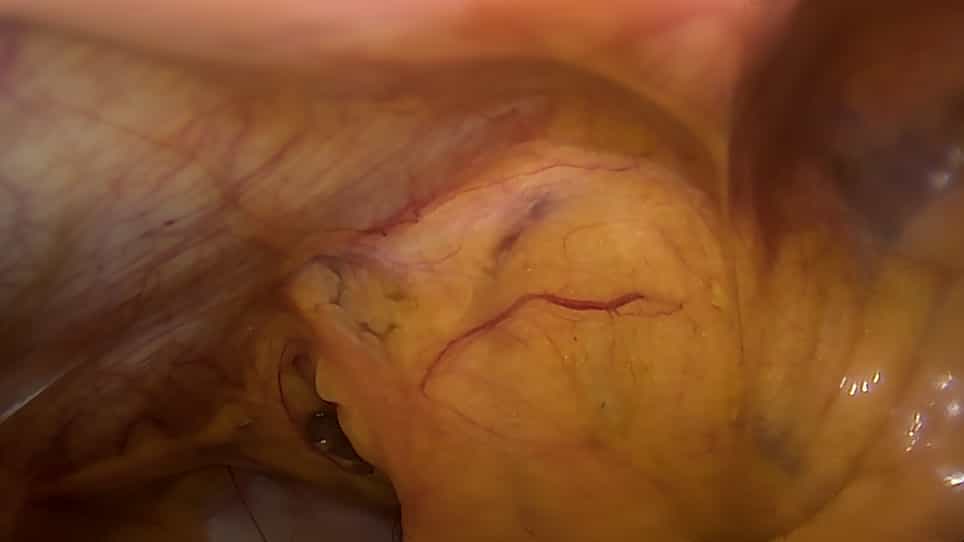
As a child, our patient suffered midgut volvulus secondary to malrotation which resulted in extensive bowel resection and developed short bowel syndrome. She presented with recurrent bouts of cholangitis. Imaging of her biliary tree confirmed common duct stones extending into the branched hepatic ducts, as well as a fusiform dilatation of the common bile duct, that appeared consistent with a type 1 choledochal cyst. Laparoscopic excision of the cyst with reconstruction using a hepatico-duodenostomy was planned.
Results:
The patient underwent successful laparoscopic cholecystectomy, CBD clearance with excision of the bile duct and reconstruction with hepatico-duodenostomy. Recovery was uneventful and she is asymptomatic on subsequent follow-up. Histology is consistent with a markedly dilated bile duct rather than a choledochal cyst.
Conclusions:
This case illustrates the dilemma of diagnosis and treatment of a dilated bile duct mimicking a choledochal cyst in the setting of short bowel syndrome and the feasibility of a laparoscopic approach in such cases. Also, it demonstrates that hepatico-duodenostomy may be a safe alternative in cases with limited material for conduit.

Related Concept Videos
 01:17
Gallbladder
The gallbladder's anatomy consists of three regions: the fundus, body, and neck. Extending from the neck, the cystic duct joins...
 01:25
Assessment of the Rectum and Anus
Rectal Inspection
Begin by inspecting the perianal and anal areas for color, texture, rashes,...
 01:17
Chronic Bowel Disorders: Introduction
Irritable Bowel Syndrome (IBS) is a common disorder affecting the gastrointestinal tract. The distinctive feature is recurrent abdominal pain associated with altered bowel movements, manifesting as constipation, diarrhea, or fluctuating between both. The...
 01:21
Inflammatory Bowel Disease V: Surgical Management
Here are some common surgical interventions for IBD:
 01:22
Appendicitis-I: Introduction
Etiology: Appendicitis can arise from various causes, primarily rooted in the obstruction of the appendix lumen. Factors contributing to this obstruction include fecal accumulation, lymphoid hyperplasia and, in...
 01:24
Chronic Pancreatitis I: Introduction
Pancreatitis is the inflammation of the pancreas, which occurs when the immune system becomes active and causes swelling, pain, and disruptions in organ function. Pancreatitis can manifest as either an acute or chronic condition.
Acute pancreatitis arises suddenly and lasts for a brief duration, while chronic pancreatitis is a long-term affliction...