Related Experiment Video
Updated: Dec 25, 2025


Author Spotlight: Integrating Mechanical and Biological Analysis in Tendinopathy Research
Published on: March 1, 2024
Achilles Tendinopathy: Pathophysiology, Epidemiology, Diagnosis, Treatment, Prevention, and Screening

Abstract:
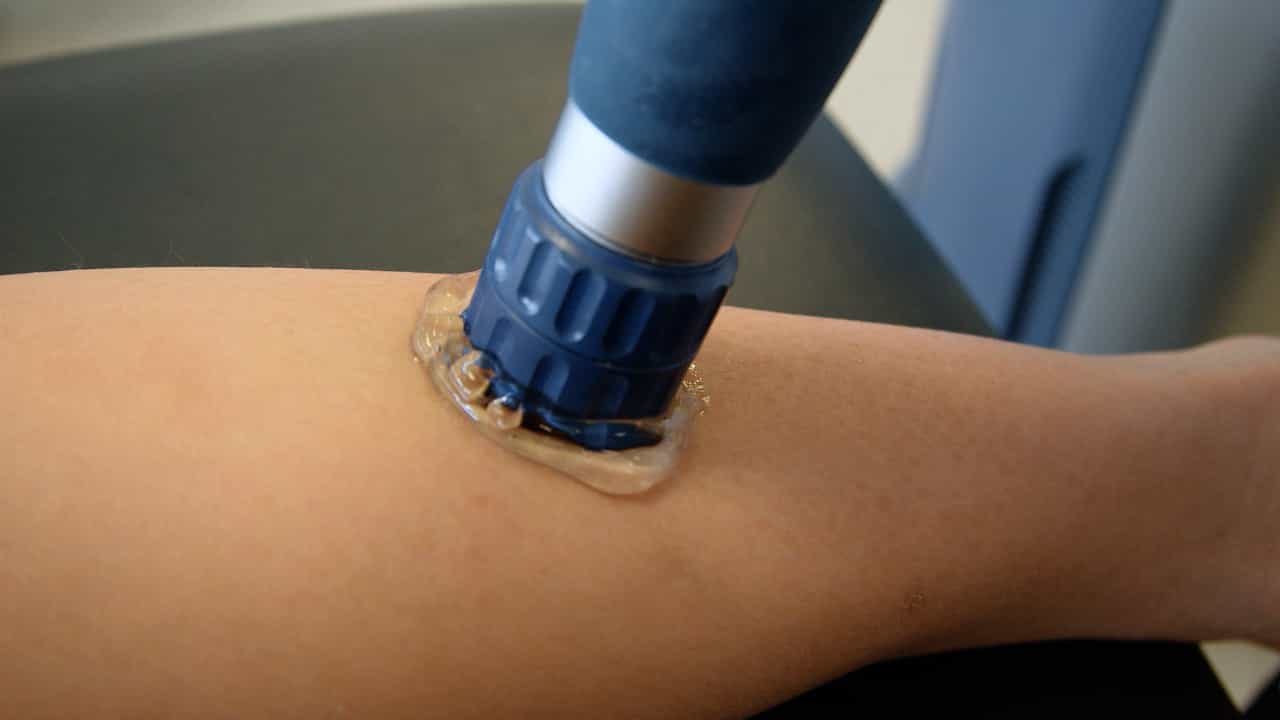
Achilles tendinopathy (AT) is a clinical term describing a nonrupture injury of the Achilles tendon where the patient presents with pain, swelling, and reduced performance and symptoms exacerbated by physical activity. About 52% of runners experience AT in their lifetime and in the United States military the rate of clinically diagnosed AT cases was 5/1000 person-yr in 2015. The pathophysiology can be viewed on a continuum proceeding from reactive tendinopathy where tenocytes proliferate, protein production increases, and the tendon thickens; to tendon disrepair in which tenocytes and protein production increase further and there is focal collagen fiber disruption; to degenerative tendinopathy involving cell death, large areas of collagen disorganization, and areas filled with vessels and nerves. Inflammation may be present, especially in the early phases. Some evidence suggests AT pain may be due to neovascularization and the ingrowth of new nerve fibers in association with this process. Prospective studies indicate that risk factors include female sex, black race, higher body mass index, prior tendinopathy or fracture, higher alcohol consumption, lower plantar flexion strength, greater weekly volume of running, more years of running, use of spiked or shock absorbing shoes, training in cold weather, use of oral contraceptives and/ or hormone replacement therapy, reduced or excessive ankle dorsiflexion range of motion, and consumption of antibiotics in the fluoroquinolone class. At least 10 simple clinical tests are available for the diagnosis of AT, but based on accuracy and reproducibility, patient self-reports of morning stiffness and/or pain in the tendon area, pain on palpation of the tendon, and detection of Achilles tendon thickening appear to be the most useful. Both ultrasound and magnetic resonance imaging (MRI) are useful in assisting in diagnosis with MRI providing slightly better sensitivity and specificity. Conservative treatments that have been researched include: (1) nonsteroidal anti-inflammatory medication, (2) eccentric exercise, (3) stretching, (4) orthotics, (5) bracing, (6) glyceryl trinitrate patches, (7) injection therapies (corticosteroids, hyaluronic acid, platelet-rich plasma injections), (8) shock wave therapy, and (9) low-level laser therapy. Nonsteroidal anti-inflammatory medication and corticosteroid injections may provide short-term relief but do not appear effective in the longer term. Eccentric exercise and shock wave therapies are treatments with the highest evidence- based effectiveness. Prevention strategies have not been well researched, but in specific populations balance training (soccer players) and shock-absorbing insoles (military recruits) may be effective. Ultrasound scans might be useful in predicting future AT occurrences.
More Related Videos
Related Concept Videos
 01:26
Peripheral Artery Disease IV: Nursing Management
 01:28
Disorders of the Skeletal Muscle
Musculoskeletal disorders
Musculoskeletal disorders involve injuries and conditions affecting the skeletal muscles and associated connective tissues. These disorders can arise from acute biomechanical stresses or chronic overuse and can occur across different age groups. Common injuries include sprains, fractures, and muscular strains, often resulting from...
 01:21
Peripheral Arterial Disease II: Clinical Manifestations and Diagnostic Evaluation
 01:23
Peripheral Artery Disease V: Postoperative Nursing Management