Related Experiment Video
Updated: Aug 15, 2026


Cardiac Catheterization in Mice to Measure the Pressure Volume Relationship: Investigating the Bowditch Effect
Published on: June 14, 2015

Insights
This review highlights hemodynamic factors influencing left ventricular pressure-volume relations and the benefits of afterload reduction in heart failure. It also discusses methods for measuring ischemic myocardium, emphasizing ultrasonic crystals for improved accuracy.
Area of Science:
- Cardiovascular Physiology
- Cardiac Mechanics
- Myocardial Ischemia Research
Background:
- Renewed interest in coronary artery disease and heart failure management.
- Previous studies focused on mathematical models of left ventricular pressure-volume relations.
- Limited understanding of hemodynamic influences on diastolic function.
Purpose of the Study:
- To review conceptual approaches to left ventricular diastolic pressure-volume relations.
- To emphasize the role of afterload in cardiac function and heart failure.
- To discuss methods for measuring regionally ischemic myocardium.
Main Methods:
- Conceptual review of hemodynamic factors affecting left ventricular pressure-volume relationships.
- Analysis of afterload's impact on cardiac function, particularly in heart failure.
- Review of techniques for measuring local mechanical performance of ischemic myocardium, including ultrasonic crystals.
Main Results:
- Hemodynamic factors acutely alter the left ventricular pressure-volume relationship.
- Afterload reduction with vasodilators provides significant hemodynamic benefits in heart failure.
- Ultrasonic crystals offer improved measurement of myocardial mechanics compared to older methods.
Conclusions:
- Hemodynamic factors, including right ventricular pressure, significantly influence left ventricular diastolic function.
- Afterload reduction is a key therapeutic strategy in heart failure, though optimal measurement remains debated.
- Accurate assessment of myocardial mechanical performance is crucial for preserving ischemic tissue.
Abstract:
The studies reported here were selected because of renewed interest in these areas, particularly as they relate to the evaluation and management of patients with coronary artery disease and heart failure. The first section emphasized a new conceptual approach to changes in the diastolic pressure-volume relation of the left ventricle. Although previous studies have concentrated on mathematical models which describe wall stress and stiffness as derived from the pressure-volume relationship, this review emphasizes that hemodynamic factors are very important in acutely altering the pressure-volume relationship of the left ventricle. This is partly due to alterations in right ventricular pressure, which subsequently influence the left ventricular pressure-volume relationship. In addition, recent studies have pointed out that compliance indices measured at low end-diastolic pressures differ from the indices measured at high end-diastolic pressures, so that limited information from one portion of the curve may not be generalized to describe the entire curve. The section on afterload emphasized the importance of this factor in influencing cardiac function, particularly in the presence of heart failure. In patients with both acute and chronic heart failure, vasodilator drugs which reduce ventricular afterload have produced substantial hemodynamic benefit by reducing the filling pressures of the right and left ventricles and increasing forward cardiac output. This hemodynamic improvement in response to afterload reduction is predictable from the different quantitative descriptions of ventricular afterload. Nevertheless, it is still unclear which method best describes afterload. Although wall stress, impedance, vascular resistance, and aortic pressure have all been utilized as a measure of afterload, each has some shortcomings which may limit its applicability. The final section reviewed approaches to the measurement of regionally ischemic myocardium. Since current studies have emphasized the importance of identifying and preserving ischemic, but viable, myocardium, this section has reviewed techniques for measuring local mechanical performance. Previous studies with the Walton-Brodie strain gauge and epicardial length gauge did not appear to be as satisfactory as more recent measurements with ultrasonic crystals, which can simultaneously measure wall thickness and segment length. These methods form the basis for ongoing experiments designed to evaluate approaches for preserving ischemic myocardium in the setting of experimental myocardial infarction.
Related Concept Videos
 01:13
The Cardiac Cycle
The Process
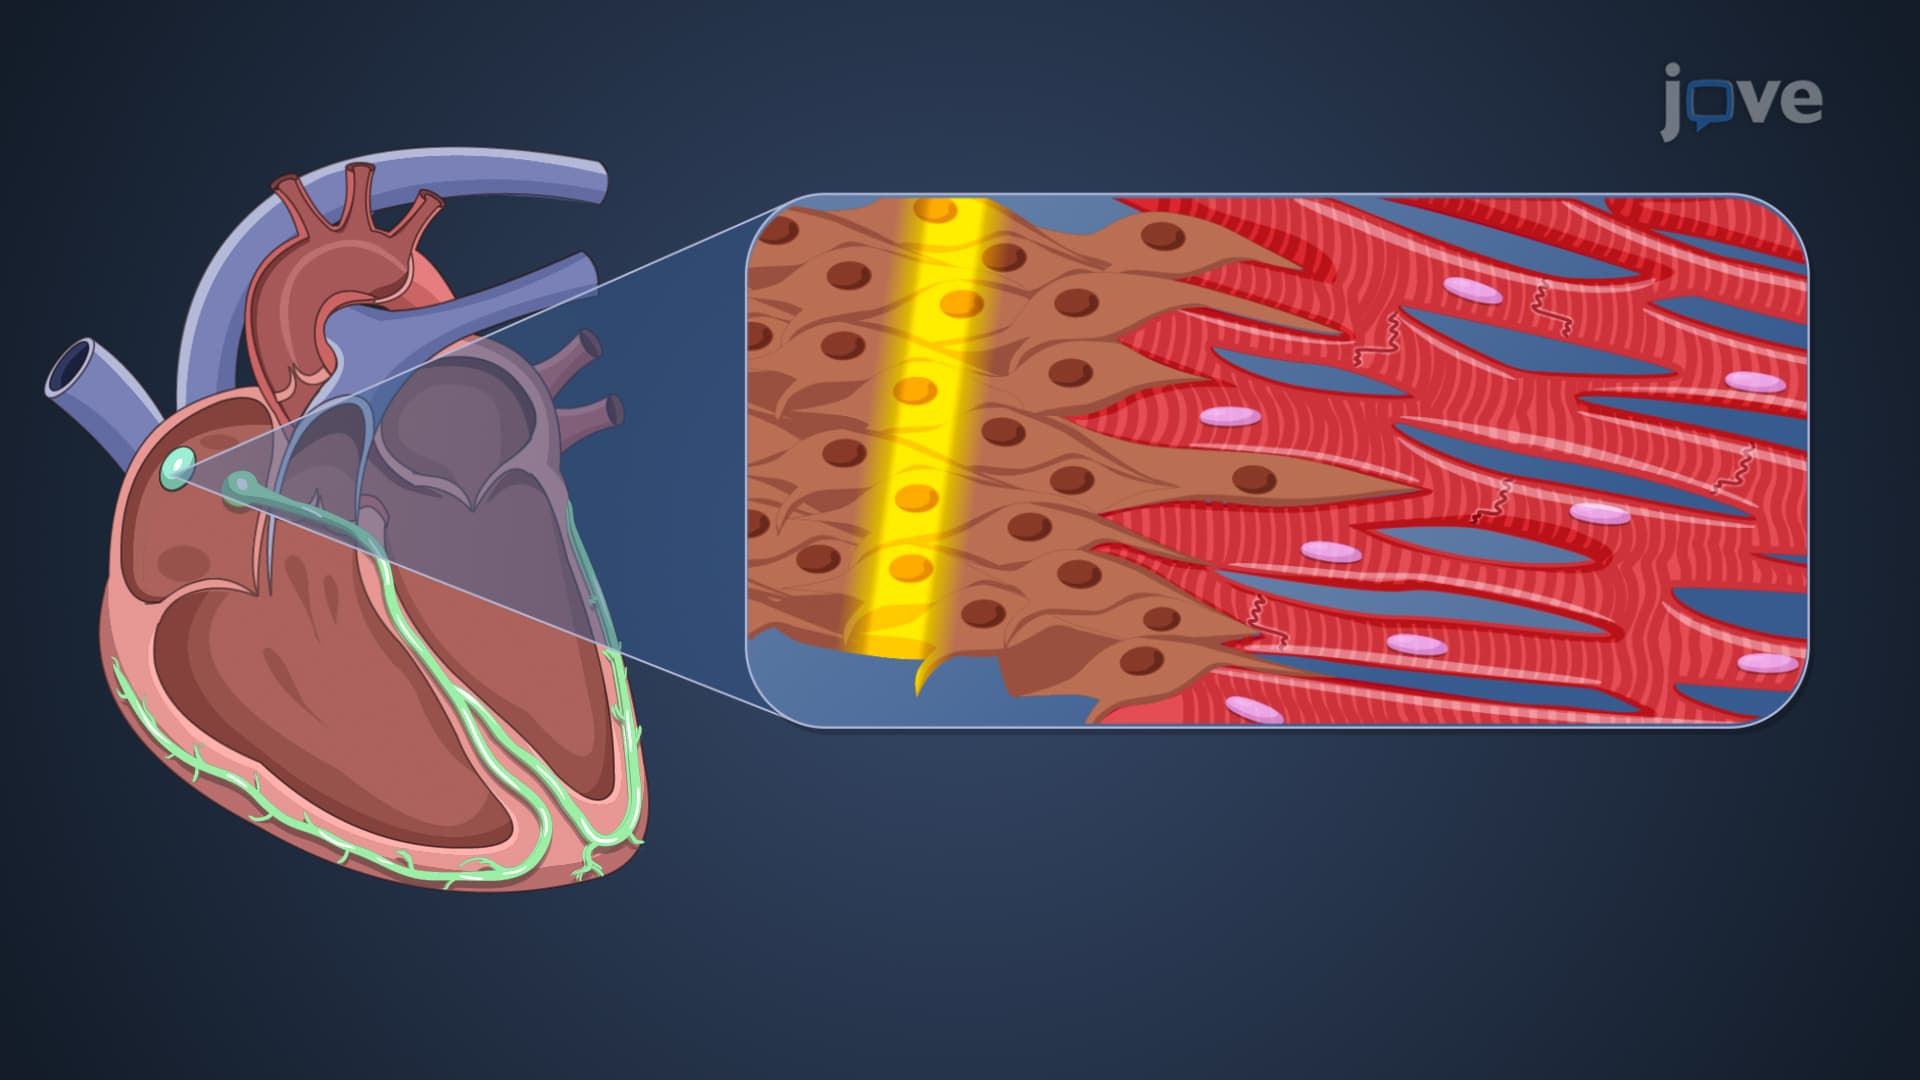
Electrical signals—sent from the sinoatrial (SA) node in the right atrial wall to the atrioventricular (AV) node between the right atrium and right ventricle—cause both atria to simultaneously contract. When the signal reaches the AV node, it pauses for approximately a tenth of a second, allowing the atria to contract and empty blood into the...
 01:19
Electrophysiology of Normal Cardiac Rhythm
 01:29
Pathophysiology of Cardiac Performance
 01:29
Cardiac Cycle
During the cardiac cycle, blood flow through the heart is regulated entirely by changing pressure gradients. This sequence of events begins with the heart in a state of total relaxation, known as mid-to-late diastole, during which blood passively flows from...
 01:26
Imbalances in Cardiac Output
CHF can occur due to the failure of either side of the heart. Left-side failure leads to pulmonary congestion—the right side continues to send blood...
 01:18
Physiology of the Heart: The Cardiac Cycle
Diastole: The Relaxation Phase
During diastole, all four heart chambers relax. The atrioventricular (AV) valves open, and the semilunar valves close. This phase sees the lowest chamber pressures, promoting ventricular filling. Venous blood enters the heart through the...