Related Experiment Video
Updated: Dec 24, 2025
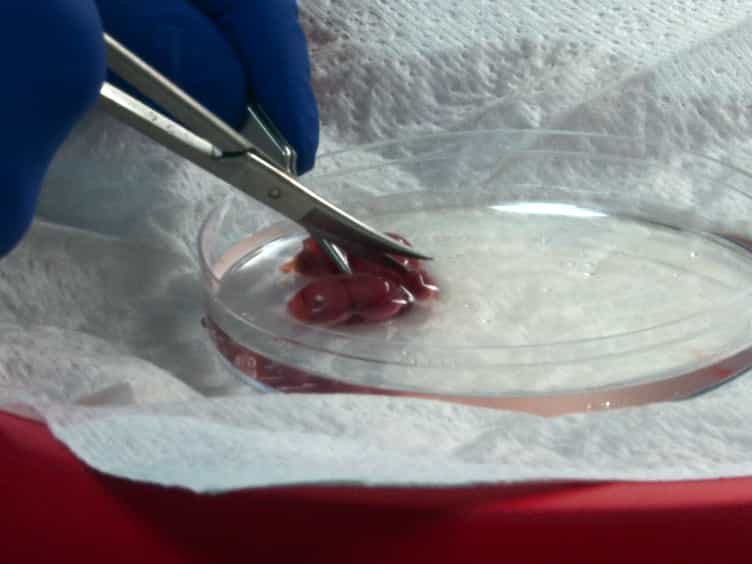

Method of Studying Palatal Fusion using Static Organ Culture
Published on: September 19, 2015
A task-shifted speech therapy program for cleft palate patients in rural Nepal: Evaluating impact and associated
Michael M Lindeborg1, Pramila Shakya2, Bhawani Pradhan2
1Department of Otolaryngology, Massachusetts Eye and Ear, Boston, MA, USA; Department of Global Health and Social Medicine, Harvard Medical School, Boston, MA, USA.

Introduction:
Though access to surgical care for cleft lip/palate has expanded in low- and middle-income countries (LMICs), post-palatoplasty speech therapy is often lacking due to limited healthcare infrastructure and personnel. This mixed-methods study seeks to: 1) evaluate the impact of task-shifted speech therapy on a standardized speech score; 2) describe the experiences of families with post-operative cleft care and associated barriers; and 3) understand how to optimize cleft care by exploring the experiences of children who had nominal improvements after task-shifted speech therapy.
Methods:
A convergent parallel mixed-methods study was conducted in Nepal. Standardized speech scores were compared by a blinded speech-language pathologist before and after the speech intervention. Semi-structured interviews (SSIs) and focus groups with families evaluated cleft care experiences and barriers. Qualitative and quantitative data were merged and analyzed.
Results:
Thirty-nine post-palatoplasty children with speech deficits (ages 3-18) underwent task-shifted speech therapy, and demonstrated significant improvements in composite speech scores targeted by exercises (p<0.0001) and weakness (p=0.0002), with improvements in misarticulation (p=0.07) and glottal stop (p=0.05) that trended towards significance. Forty-seven SSIs demonstrated that the greatest barriers to follow-up were family responsibilities (62%), travel/distance (53%), and work (34%). In five focus groups, families expressed a desire to improve their child's speech and seek formal speech therapy. The speech intervention was found to be beneficial because of the compassionate staff, free lodging/food, and ability to socialize with other cleft patients and families. After merging quantitative and qualitative data, we noted that younger children between 3 and 5 years old and families who traveled greater distances for healthcare access benefited less from the speech therapy intervention.
Conclusions:
Task-shifted speech therapy has the potential to improve cleft lip/palate speech in LMICs. Multiple biosocial issues limit access to appropriate post-operative care.


