Related Experiment Video
Updated: Dec 23, 2025
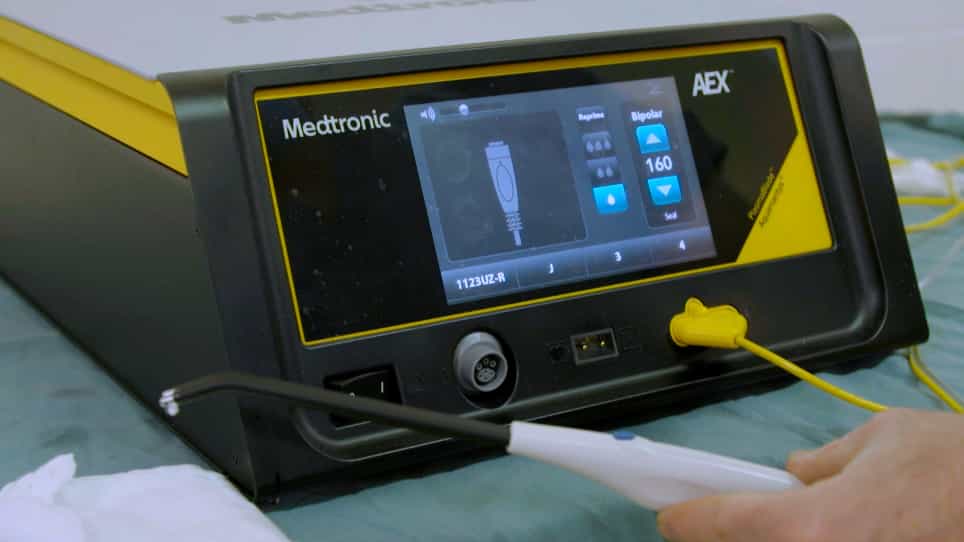

A Saline/Bipolar Radiofrequency Energy Device As an Adjunct for Hemostasis in Solid Organ Injury/Trauma
Published on: July 28, 2020
Closing the gap in care of blunt solid organ injury in children
Nicholas Yung1, Daniel Solomon, Kevin Schuster
1From the Department of General Surgery (N.Y., D.S., K.S., E.C.-L.), Department of Pediatric Surgery (D.S., E.C.-L.), Yale University School of Medicine; and Department of General Surgery, Trauma and Surgical Critical Care (K.S.), New Haven, Connecticut.

Insights
Pediatric trauma centers (PTCs) manage blunt solid organ injuries with less surgery and shorter hospital stays than adult (ATC) or dual trauma centers (DTC). Guidelines emphasize physiology over injury grade, but disparities persist.
Area of Science:
- Trauma Surgery
- Pediatric Surgery
- Surgical Outcomes
Background:
- Pediatric blunt solid organ injuries historically show higher nonoperative management rates and shorter lengths of stay (LOS) in pediatric trauma centers (PTCs) compared to adult (ATCs) or dual trauma centers (DTCs).
- Recent guidelines emphasize physiologic parameters over injury grade to guide clinical decisions, aiming to improve resource allocation and reduce LOS.
Purpose of the Study:
- To evaluate the influence of updated clinical guidelines on the management and outcomes of pediatric blunt solid organ injuries across different trauma center types.
- To assess trends in operative intervention rates and length of stay (LOS) following the implementation of evidence-based guidelines.
Main Methods:
- A retrospective analysis of the National Trauma Data Bank (2007-2016) identified pediatric patients (<19 years) with isolated spleen or liver injuries.
- Statistical methods including linear regression, odds ratio (OR), and chi-squared tests were employed to compare operative rates and LOS between trauma center types and injury grades.
Main Results:
- Across 55,036 identified injuries, ATCs and DTCs had significantly higher odds of operative intervention compared to PTCs (OR 4.43 and 2.88, respectively).
- Mean LOS decreased across all center types, with significant reductions observed in ATCs (1.52 days) and PTCs (1.31 days).
- While ATCs showed LOS improvements across multiple injury grades, PTCs did not demonstrate a correlation between LOS and injury grade.
Conclusions:
- Despite guideline shifts towards nonoperative management, significant disparities in operative intervention rates persist between ATCs and PTCs for pediatric blunt solid organ injuries.
- All trauma center types appear to have challenges in adhering to consensus guidelines for accelerated discharge pathways, indicating a need for further optimization of care management.
Introduction:
Cross-sectional data of pediatric blunt solid organ injury demonstrates higher rates of nonoperative management and shorter lengths of stay (LOSs) in pediatric trauma centers (PTCs) versus adult trauma centers (ATCs) or dual trauma centers (DTCs). Recent iterations of guidelines (McVay 2008, J Pediatr Surg 2008;43(6):1072-1076 J Trauma Acute Care Surg 2015;79(4):683-693) have emphasized physiologic parameters rather than injury grade in clinical decision making, improving resource allocation and decreasing LOS. We sought to evaluate how these guidelines have influenced care.
Methods:
The National Trauma Data Bank (2007-2016) was queried for isolated spleen and liver injuries in patients younger than 19 years. Linear regression, odds ratio (OR), and χ test were used to determine significance between operative intervention or LOS among different trauma center types and grade of injury.
Result:
A total of 55,036 blunt spleen or liver injuries were identified. Although operative rates decreased in ATCs over time (p = 0.037), patients treated at ATCs or DTCs continued to demonstrate higher ORs of operative intervention (OR, 4.43 and 2.88, respectively) compared with PTCs. Mean LOS decreased by 1.52 (p < 0.001), 0.49 (p = 0.26), and 1.31 (p = 0.05) days at ATC, DTC, and PTC to 6.43, 6.68, and 5.16 days. Improvement in LOS for ATCs was distributed across injury Grades I, II, and IV, while there was no correlation among PTCs for injury grade.
Conclusion:
Despite more than a decade of guidelines in pediatric solid organ injury supporting nonoperative management and accelerated discharge pathways based on physiologic parameters, rates of operative intervention remain much higher in ATCs versus PTCs, and all centers appear to fall short of consensus guidelines for discharge.
Level Of Evidence:
Care management study, level IV.


Related Concept Videos
 01:20
Acute Kidney Injury V: Interprofessional Care
 01:26
Flail Chest-II
Assessment:
1. Clinical Evaluation:
History:
 01:27
Fractures: Bone Repair
Minor fractures with no bone displacement are treated by immobilizing the fractured bone using a cast or splint. However, in the case of fractures with displaced bones, the broken bones are repositioned before immobilization to ensure successful healing without deformation and loss of function. The realignment of fractured bone ends is performed through a process called reduction. If the...
 01:22
Acute Kidney Injury I: Introduction
 01:28
Kidney Transplant I: Introduction
 01:30
Acute Kidney Injury IV: Diagnostic Studies and Prevention