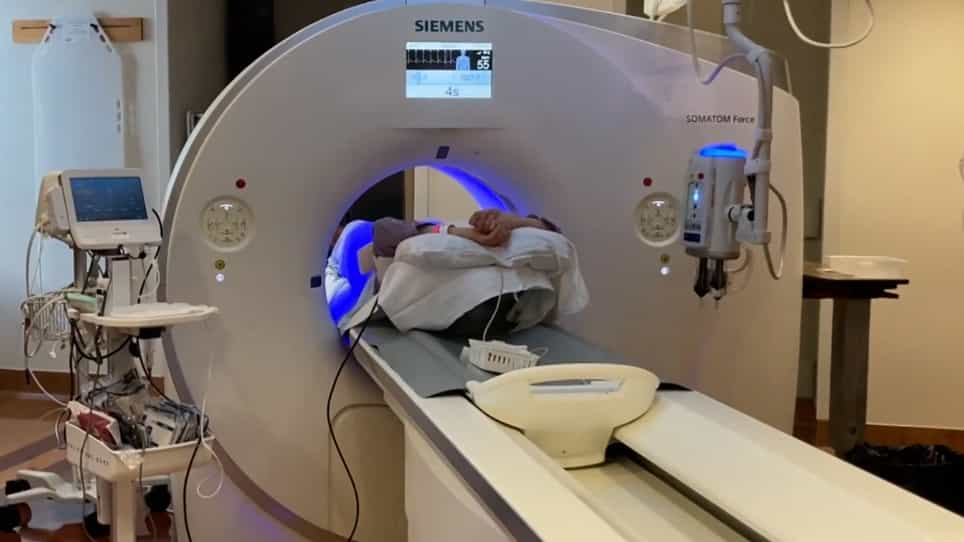
Retrospectively ECG-gated helical vs. non-ECG-synchronized high-pitch CTA of the aortic root for TAVI planning
Barbora Horehledova1,2, Casper Mihl1,2, Ellen Boswijk1,2
1Department of Radiology and Nuclear Medicine, Maastricht University Medical Center, Maastricht, The Netherlands.

Insights
Optimal imaging for transcatheter aortic valve implantation (TAVI) is crucial. Systolic imaging is necessary for accurate aortic annulus measurements, impacting prosthesis size selection in nearly half of TAVI candidates.
Area of Science:
- Cardiovascular imaging
- Interventional cardiology
- Radiology
Background:
- Multidetector computed tomography (MDCT) is vital for pre-transcatheter aortic valve implantation (TAVI) assessment.
- Optimal pre-TAVI imaging protocols lack consensus, potentially causing discrepancies in aortic annulus measurements and prosthesis selection.
Purpose of the Study:
- To evaluate differences in aortic annulus measurements using systolic, diastolic, and non-ECG-synchronized imaging.
- To assess the impact of imaging methods on TAVI prosthesis size selection.
Main Methods:
- Retrospective analysis of 50 TAVI candidates using ECG-gated CT angiography and non-ECG-synchronized CT.
- Aortic root dimensions assessed across the cardiac cycle (0-100% R-R interval) and on non-ECG-synchronized scans.
- Comparison of measurements using ANOVA and Bland-Altman analysis.
Main Results:
- Max-systolic measurements were significantly larger than end-diastolic and non-ECG-synchronized measurements (p<0.001).
- Prosthesis size selection varied across methods in 48-62% of patients.
- Significant and clinically relevant discrepancies were observed between imaging strategies.
Conclusions:
- Systematic differences in aortic annular dimensions based on imaging timing are clinically significant.
- Imaging strategy impacts prosthesis selection in a substantial portion of TAVI candidates.
- Systolic imaging is essential for accurate assessment of maximal annular dimensions and minimum annulus-coronary ostia distances for optimal TAVI prosthesis selection.
Background:
Multidetector computed tomography (MDCT) plays a key role in patient assessment prior to transcatheter aortic valve implantation (TAVI). However, to date no consensus has been established on what is the optimal pre-procedural imaging protocol. Variability in pre-TAVI acquisition protocols may lead to discrepancies in aortic annulus measurements and may potentially influence prosthesis size selection.
Purpose:
The current study evaluates the magnitude of differences in aortic annulus measurements using max-systolic, end-diastolic, and non-ECG-synchronized imaging, as well as the impact of method on prosthesis size selection.
Material And Methods:
Fifty consecutive TAVI-candidates, who underwent retrospectively-ECG-gated CT angiography (CTA) of the aortic root, directly followed by non-ECG-synchronized high-pitch CT of the entire aorta, were retrospectively included. Aortic root dimensions were assessed at each 10% increment of the R-R interval (0-100%) and on the non-ECG-synchronized scan. Dimensional changes within the cardiac cycle were evaluated using a 1-way repeated ANOVA. Agreement in measurements between max-systole, end-diastole and non-ECG-synchronized scans was assessed with Bland-Altman analysis.
Results:
Maximal dimensions of the aortic root structures and minimum annulus-coronary ostia distances were measured during systole. Max-systolic measurements were significantly and substantially larger than end-diastolic (p<0.001) and non-ECG-synchronized measurements (p<0.001). Due to these discrepancies, the three methods resulted in the same prosthesis size selection in only 48-62% of patients.
Conclusions:
The systematic differences between max-systolic, end-diastolic and non-ECG-synchronized measurements for relevant aortic annular dimensions are both statistically significant and clinically relevant. Imaging strategy impacts prosthesis size selection in nearly half the TAVI-candidates. End-diastolic and non-ECG-synchronized imaging does not provide optimal information for prosthesis size selection. Systolic image acquisition is necessary for assessment of maximal annular dimensions and minimum annulus-coronary ostia distances.
More Related Videos
 09:57
Four-Dimensional Computed Tomography-Guided Valve Sizing for Transcatheter Pulmonary Valve Replacement
Published on: January 20, 2022
 06:59
Improved Registration of 3D CT Angiography with X-ray Fluoroscopy for Image Fusion During Transcatheter Aortic Valve Implantation
Published on: June 3, 2018
Related Concept Videos
 01:22
Aortic Regurgitation II: Clinical Features and Diagnostic Tests
 01:28
Imaging Studies for Cardiovascular System V: CT