Related Experiment Video
Updated: Dec 21, 2025
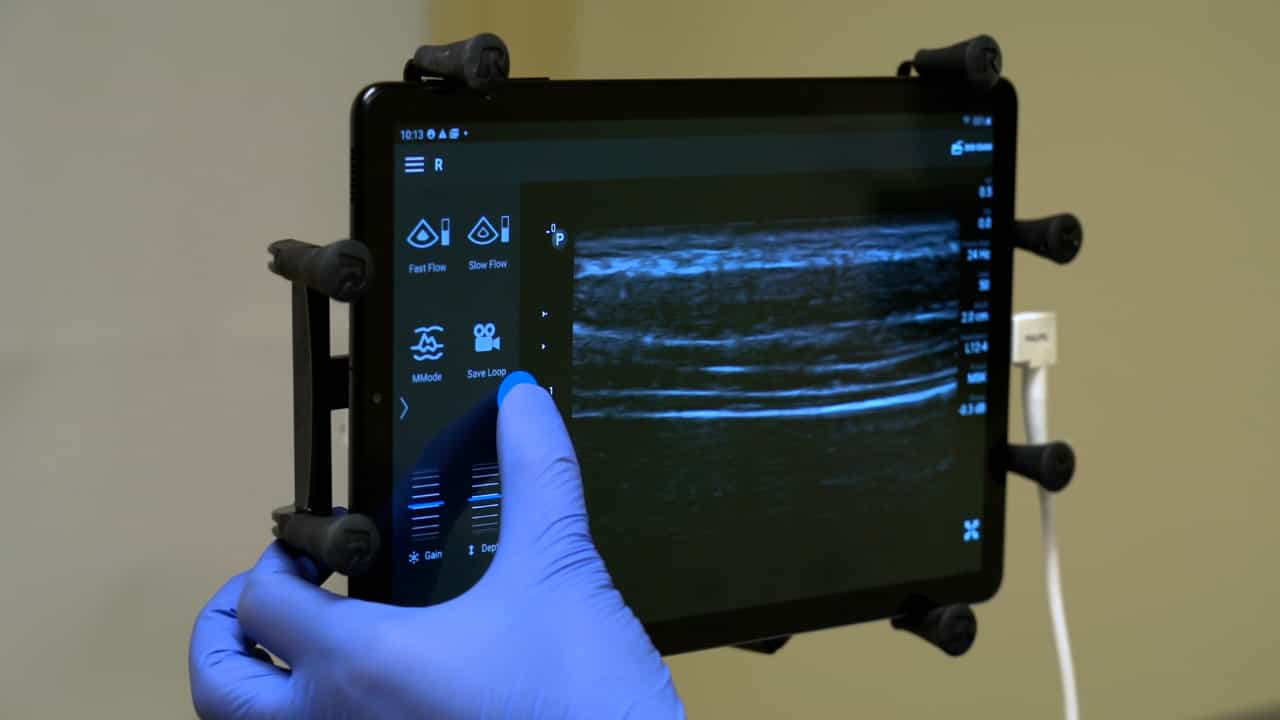
Author Spotlight: Unraveling the Impact of Mechanical Ventilation on Diaphragm Function and Patient Outcomes
Published on: November 3, 2023
Diaphragm Atrophy During Pediatric Acute Respiratory Failure Is Associated With Prolonged Noninvasive Ventilation
Christie L Glau1, Thomas W Conlon, Adam S Himebauch
1All authors: Department of Anesthesiology and Critical Care Medicine, Children's Hospital of Philadelphia, Perelman School of Medicine at the University of Pennsylvania, Philadelphia, PA.

Objectives:
Diaphragm atrophy is evident during invasive ventilation for pediatric acute respiratory failure, but with unknown significance. We hypothesized that diaphragm atrophy in pediatric acute respiratory failure is associated with prolonged noninvasive positive pressure ventilation following extubation.
Design:
Prospective observational study.
Setting:
Single-center academic PICU.
Patients:
Invasively ventilated children with acute respiratory failure.
Interventions:
Diaphragm ultrasound was performed within 36 hours after intubation and repeated within 48 hours preceding extubation. Rapid shallow breathing index at 15 and 30 minutes of a spontaneous breathing trial and negative inspiratory force were collected in a subset of patients concurrently with the ultrasound measurements.
Measurements And Main Results:
Diaphragm thickness at end-expiration was measured to assess for diaphragm atrophy during mechanical ventilation. Percentage change in diaphragm thickness at end-expiration was defined as baseline diaphragm thickness at end-expiration minus final, preextubation diaphragm thickness at end-expiration divided by baseline diaphragm thickness at end-expiration. The primary outcome measure was duration of noninvasive positive pressure ventilation following extubation with prolonged use defined as noninvasive positive pressure ventilation use for greater than 24 hours postextubation. Among 56 children, 47 (median age, 15.5 mo; interquartile range, 6-53 mo) had diaphragm thickness at end-expiration measured within 48 hours prior to extubation. Fourteen (30%) had prolonged noninvasive positive pressure ventilation use with median duration 110 hours (interquartile range, 52-130 hr). The median percentage change of diaphragm thickness at end-expiration from baseline among those with and without prolonged noninvasive positive pressure ventilation use was -20% (interquartile range, -32% to -10%) versus -7% (interquartile range, -21% to 0%) (p = 0.04).
Conclusions:
Diaphragm atrophy is associated with prolonged postextubation noninvasive positive pressure ventilation in children with acute respiratory failure. Serial bedside diaphragm ultrasound may identify children at risk for prolonged noninvasive positive pressure ventilation use after extubation.


Related Concept Videos
 01:17
Pulmonary Cycle: Exhalation
 01:30
Acute Respiratory Failure-III
 01:21
Acute Respiratory Failure-II
The underlying physiological abnormalities that contribute to hypoxemic respiratory failure include:
 01:29
Acute Respiratory Failure-V
Ensure that patients are monitored continuously for their response to therapy, including changes in...
 01:23
Acute Respiratory Failure-IV
 01:24
Endotracheal Tube Extubation
Procedure
Extubation removes the endotracheal tube (ETT) from the patient on mechanical ventilation. It requires a well-coordinated, multidisciplinary approach involving physicians, nurses, respiratory therapists, and other healthcare professionals....