Related Experiment Video
Updated: Dec 21, 2025


Modeling Encephalopathy of Prematurity Using Prenatal Hypoxia-ischemia with Intra-amniotic Lipopolysaccharide in Rats
Published on: November 20, 2015
The Association Between Isolated Maternal Hypothyroxinemia in Early Pregnancy and Preterm Birth
Xi Yang1, Yamei Yu2, Chen Zhang1,3,4
1The International Peace Maternity and Child Health Hospital, School of Medicine, Shanghai Jiao Tong University, Shanghai, China.

The association between isolated maternal hypothyroxinemia (IMH) during pregnancy and preterm birth (PTB), especially for subtypes of PTB, is unclear. This study aimed at determining the association between IMH diagnosed in early pregnancy and PTB, with further investigation into various subtypes of PTB. This study included 41,911 pregnant women (963 with IMH and 40,948 euthyroid women) who underwent first-trimester prenatal screening at the International Peace Maternity and Child Health Hospital (IPMCH) in Shanghai, China between January 2013 and December 2016. PTB was defined as birth before 37 weeks of gestation. PTB was further classified into three clinically relevant groups to investigate the clinical heterogeneity of PTB: (a) preterm birth with premature rupture of membranes (PROM-PTB); (b) spontaneous preterm birth with intact membranes (S-PTB); and (c) medically-induced preterm birth (MI-PTB). The overall and sex-specific effect of IMH on PTB and various subtypes of PTB were estimated by using logistic regression in crude and adjusted models. Pregnant women with IMH had an increased risk of PTB (odds ratio [OR]: 1.32 [95% confidence interval; CI: 1.02-1.70], p = 0.03) compared with women with euthyroid function. The increased risk of PTB is mainly driven by S-PTB (OR: 1.57 [CI: 1.11-2.24], p = 0.01), while women with early pregnancy IMH had no statistically significant increased risk of PROM-PTB and MI-PTB. The effect of IMH on PTB was modified by fetal sex (p-values for interaction = 0.04). More prominent effects were observed in women carrying a female fetus, while no statistically significant effects were found in women carrying a male fetus. This study revealed that pregnant women with IMH in early pregnancy have a higher risk of PTB compared with euthyroid women. The effect of IMH on PTB is mainly driven by S-PTB and is modified by fetal sex.
The association between isolated maternal hypothyroxinemia (IMH) during pregnancy and preterm birth (PTB), especially for subtypes of PTB, is unclear. This study aimed at determining the association between IMH diagnosed in early pregnancy and PTB, with further investigation into various subtypes of PTB. This study included 41,911 pregnant women (963 with IMH and 40,948 euthyroid women) who underwent first-trimester prenatal screening at the International Peace Maternity and Child Health Hospital (IPMCH) in Shanghai, China between January 2013 and December 2016. PTB was defined as birth before 37 weeks of gestation. PTB was further classified into three clinically relevant groups to investigate the clinical heterogeneity of PTB: (a) preterm birth with premature rupture of membranes (PROM-PTB); (b) spontaneous preterm birth with intact membranes (S-PTB); and (c) medically-induced preterm birth (MI-PTB). The overall and sex-specific effect of IMH on PTB and various subtypes of PTB were estimated by using logistic regression in crude and adjusted models. Pregnant women with IMH had an increased risk of PTB (odds ratio [OR]: 1.32 [95% confidence interval; CI: 1.02-1.70], p = 0.03) compared with women with euthyroid function. The increased risk of PTB is mainly driven by S-PTB (OR: 1.57 [CI: 1.11-2.24], p = 0.01), while women with early pregnancy IMH had no statistically significant increased risk of PROM-PTB and MI-PTB. The effect of IMH on PTB was modified by fetal sex (p-values for interaction = 0.04). More prominent effects were observed in women carrying a female fetus, while no statistically significant effects were found in women carrying a male fetus. This study revealed that pregnant women with IMH in early pregnancy have a higher risk of PTB compared with euthyroid women. The effect of IMH on PTB is mainly driven by S-PTB and is modified by fetal sex.

Related Concept Videos
 01:07
Teratogenicity
 01:20
Pathophysiology of Diabetes
Type 1 diabetes is characterized by autoimmune-mediated destruction of pancreatic β cells, with environmental factors potentially triggering this process in genetically susceptible individuals. Despite many not having a family history, certain genes increase susceptibility,...
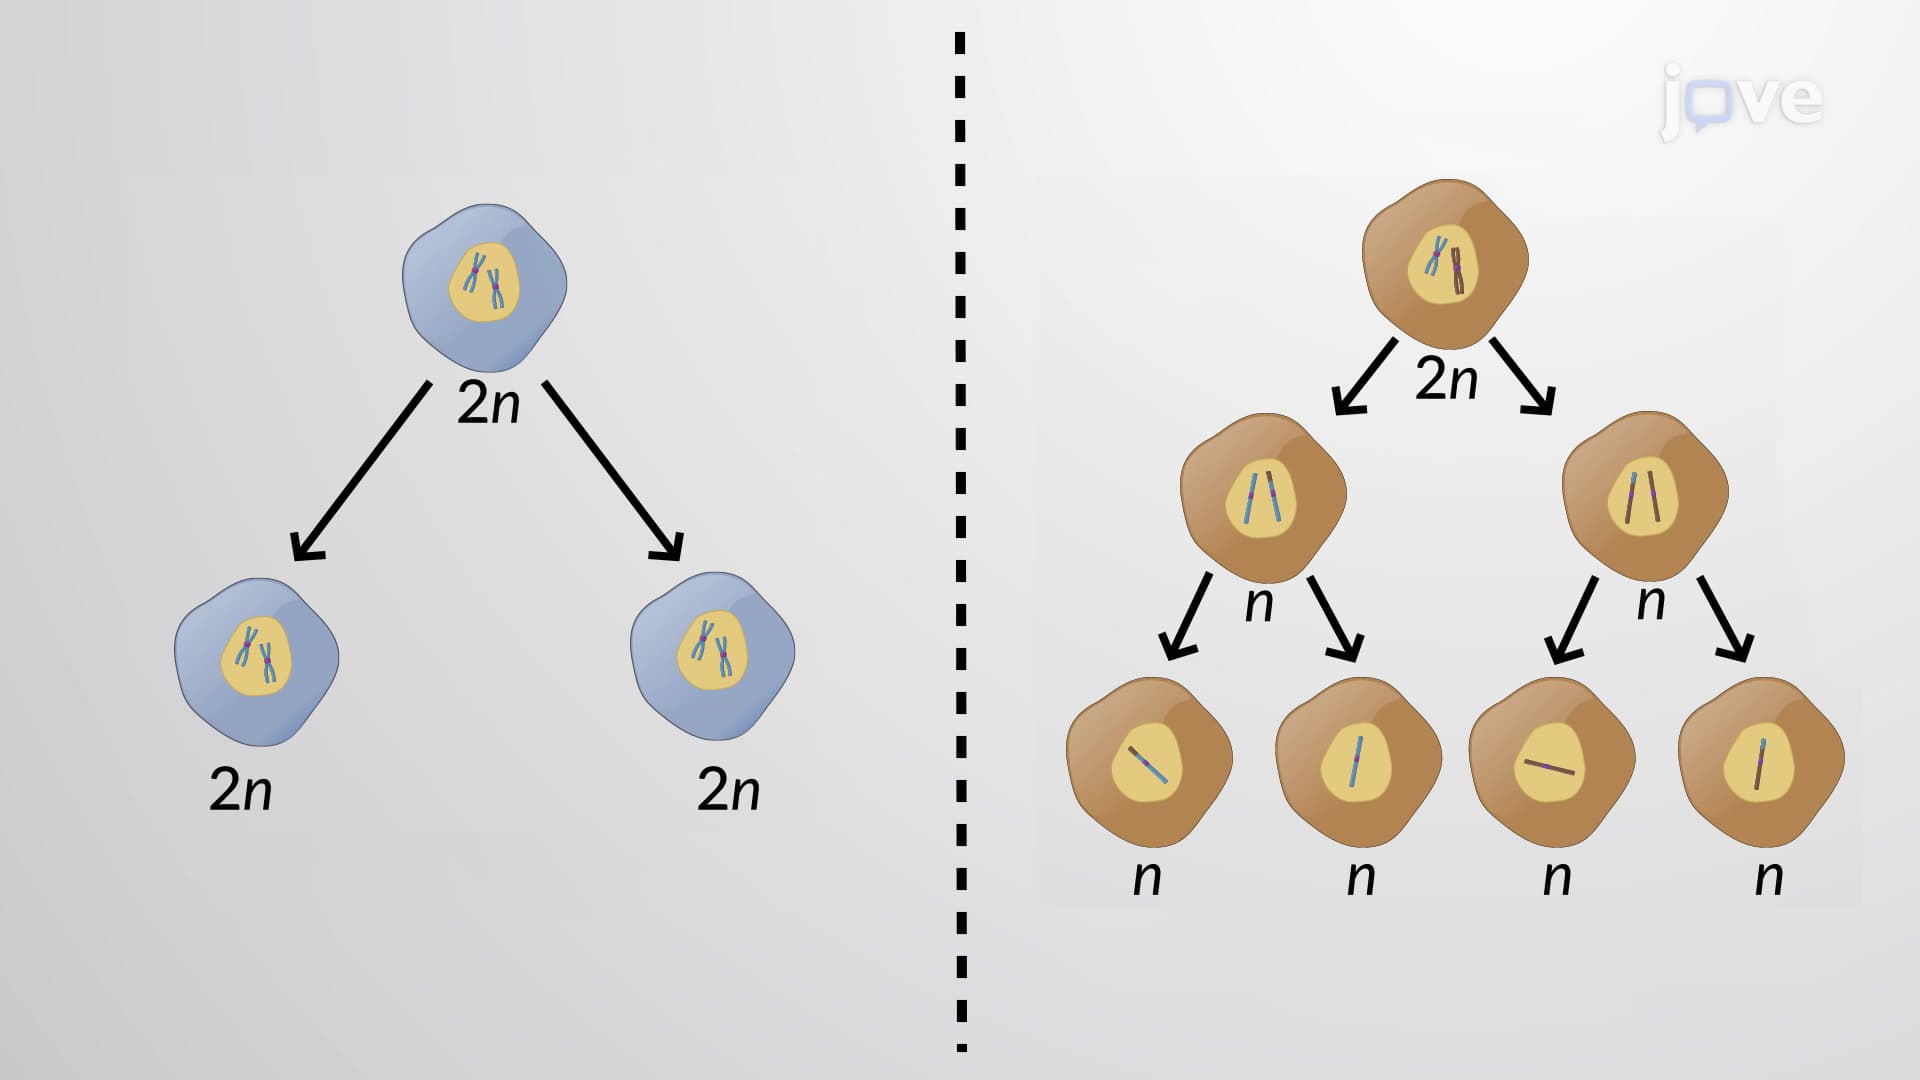 02:57
Meiosis vs. Mitosis
Before the start of mitosis and meiosis I, the cell synthesizes DNA, resulting in two homologous copies of each chromosome. DNA synthesis is...
 01:22
Development of Immunocompetence
The initial cells that migrate from the fetal thymus settle within the skin and epithelial tissues lining the mouth, digestive tract, and in females, the uterus and vagina. These cells, including skin-based dendritic cells, serve as antigen-presenting cells, playing a key role in T cell activation.
Subsequent T...
 01:20
Synthesis and Regulation of Thyroid Hormones
Upon reaching the thyroid gland, TSH stimulates the follicular cells' active uptake of iodide ions from the blood. The ions diffuse to the apical surface of the cells and are oxidized to iodine. The...
 01:52
Regression Toward the Mean