Related Experiment Video
Updated: Dec 20, 2025
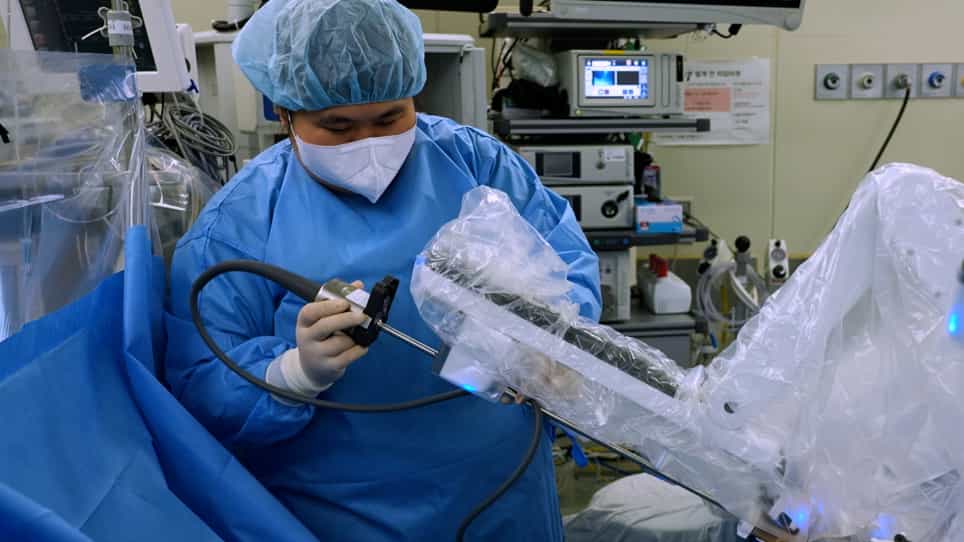

Robot-Assisted Kidney Transplantation
Published on: July 19, 2021
Use of retrograde pyelogram to plan for miniature open incision in pediatric pyeloplasty
Amr K Salama1, Konrad M Szymanski2, Jessica Casey2
1Division of Pediatric Urology, Riley Hospital for Children at IU Health, 705 Riley Hospital Dr., Suite 4230, Indianapolis, IN, 46202, USA; Division of Pediatric Urology, Urology Department at Alexandria School of Medicine, Alexandria University, Egypt.

Introduction:
As robotic-assisted surgery becomes increasingly utilized for pediatric ureteropelvic junction (UPJ) obstruction, open surgeons have countered by using muscle-splitting, miniature (≤2 cm) incisions. To prepare for this type of incision during pyeloplasty, it is necessary to define the exact location of the UPJ. The use of retrograde pyelogram (RPG) at the time of pyeloplasty helps the surgeon to identify the exact location of UPJ, and thus be able to use a muscle-splitting, miniature incision for open pyeloplasty.
Objective:
We hypothesize that when performing a muscle-splitting, miniature incision open approach; preoperative RPG frequently changes the traditional pyeloplasty flank incision at the tip of the 11th or 12th rib.
Materials & Methods:
A retrospective review of open pyeloplasties performed by a single surgeon at our institution from 7/1/2010 to 12/31/2018 was performed to determine rate of use of RPG, open pyeloplasty incision location and to determine what factors are predictive of incisional site.
Results:
114 of 122 (93.4%) patients with 115 renal units had pyeloplasties with preoperative RPG performed. Of the 8 procedures without RPG, two had a pelvic kidney diagnosed prior to surgery, two had narrow ureteric orifices that were difficult to cannulate, and four had associated reflux. In 31/115 (27%) pyeloplasties the incision was changed from a standard incision position at the 11th or 12th rib to an alternative incision (i.e. extended muscle-transecting incision at the tip of the 11th or 12th rib, or to an alternate incision site including Gibson, McBurney's incision, or low anterior abdominal incision). 84/115 (73.0%) had a miniature (<2 cm) incision at the tip of the 11th or 12th rib. Grade IV hydronephrosis was a significant predictor for changing the traditional incision site (p = 0.02). Preoperative nephrostomy tube insertion was also associated with an increased likelihood of having an alternate incision (p = 0.04). Incision site was not significantly affected by age of the patient at surgery, patient sex, size of the affected kidney, T1/2 times of <30 min, split function of <30%, kidney length differential, or laterality.
Conclusion:
The consistent use of RPG prior to pyeloplasty helps surgeons to plan for a small muscle-splitting, miniature open incisions. In our experience, 27% of pyeloplasties required alternative incision sites based on the results of pre-operative RPG.
More Related Videos
 06:39
Technical Modification of the Terminal Ureter During Total Transperitoneal Laparoscopic Nephroureterectomy for Upper Urinary Tract Urothelial Carcinoma
Published on: November 22, 2019
 05:34
A Mouse Model to Evaluate the Long-Term Structural and Functional Outcomes after the Reversal of Prolonged Unilateral Ureteric Obstruction
Published on: July 18, 2025
Related Concept Videos
 01:22
Imaging Studies V: Intravenous Urography and Retrograde Pyelography
 01:26
Kidney Transplant II: Surgical Procedure
 01:28
Acute Pyelonephritis II: Diagnostic Studies and Management