Related Experiment Video
Updated: Dec 18, 2025
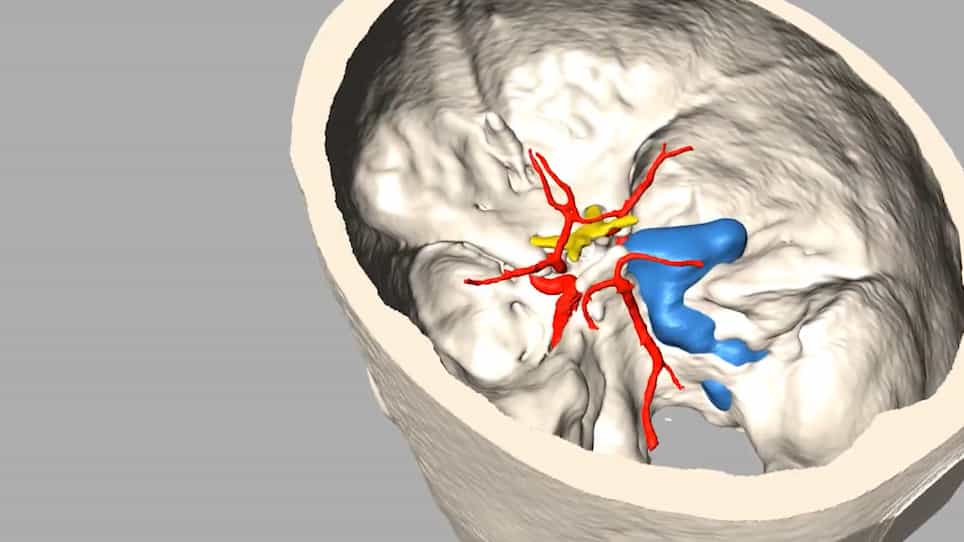

Multicolor 3D Printing of Complex Intracranial Tumors in Neurosurgery
Published on: January 11, 2020
Skull Base Chordomas and Chondrosarcomas
Natalia Kremenevski1, Sven-Martin Schlaffer2, Roland Coras3
1Department of Neurosurgery, University of Erlangen-Nürnberg, Erlangen, Germany, natalia.kremenevskaja@uk-erlangen.de.

Abstract:
Skull base chordomas account for less than 0.2% and chondrosarcomas for less than 0.15% of all intracranial tumors. Although their clinical and imaging presentations are similar, they derive from different origins. Chordomas arise from embryonic remnants of the primitive notochord and chondrosarcomas from primitive mesenchymal cells or from the embryonic rest of the cranial cartilaginous matrix. Both entities are characterized by infiltration and destruction of the surrounding bone and soft tissue and a high locoregional recurrence rate. Chondrosarcomas, when treated with similar complex strategies, display a much better prognosis than chordomas. The overall survival is approximately 65% for chordomas and 80% for chondrosarcomas at 5 years and 30 and 50%, respectively, at 10 years. Chordomas are divided into the following 3 histological types: classical (conventional), chondroid, and dedifferentiated. Chondrosarcomas have conventional, mesenchymal, clear cell, and dedifferentiated subgroups. Both tumor entities often present with nonspecific symptoms, and headaches are the most reported initial symptom. Computed tomography and magnetic resonance imaging are required to determine the tumor localization and the extent of tumor growth. The treatment philosophy is to maximize tumor resection, minimize morbidity, and preserve function. Neurosurgical approaches commonly used for the resection of intracranial chordomas and chondrosarcomas are transsphenoidal, transbasal, cranio-orbitozygomatic, transzygomatic extended middle fossa, transcondylar, and transmaxillary approaches. Chordomas and chondrosarcomas are not sensitive to chemotherapy and there are no approved drugs for their treatment. The present treatment concept is a combination of surgical resection with a maximal excision and preserving patients' quality of life by adjuvant radiotherapy for both chordomas and chondrosarcomas.

Related Concept Videos
 01:22
Sutures of the Skull
Sutures are immobile joints between adjacent bones of the skull. The narrow gap between the bones is filled with dense, fibrous connective tissue that unites the bones. The long sutures located between the skull bones are not straight but instead follow irregular, tightly twisting paths. These twisting lines tightly...
 01:14
Cranial Bones: Superior and Posterior View
The frontal bone is the single bone that forms the forehead. At its anterior midline, between the eyebrows, there is a slight depression called the glabella. The frontal bone also forms the supraorbital margin of the orbit. Near the middle of this margin is the supraorbital foramen, the opening that provides passage for a sensory nerve to the forehead. The frontal bone is thickened just above each supraorbital margin,...
 01:24
Bone Formation by Endochondral Ossification
 01:08
Overview of the Skull
The cranial vault surrounds and protects the brain and houses the middle and inner ear structures. This cavity is bounded superiorly by the rounded top of the skull, which...
 01:09
Overview of the Axial Skeleton
The axial skeleton of the...
 01:19
Cranial and Spinal Meninges
Cranial Meninges
These meningeal layers cover the cranium. The dura mater is the outermost layer of cranial meninges. It is a thick and durable membrane of dense...