Related Experiment Video
Updated: Dec 18, 2025


Laparoscopic Repair of Para-Esophageal Hernia Using Absorbable Biosynthetic Mesh
Published on: September 11, 2021
Laparoscopic repair of Morgagni hernia in children
Ali İhsan Anadolulu1, Gonca Gerçel2, Osman Hakan Kocaman3
1Mehmet Akif İnan Training and Research Hospital Clinic of Pediatric Surgery, Şanlıurfa, Turkey.

Insights
Laparoscopic repair of Morgagni hernia is a safe and effective treatment. Leaving the hernia sac during this minimally invasive surgery did not lead to complications or recurrence.
Area of Science:
- Pediatric Surgery
- Thoracic Surgery
- Minimally Invasive Surgery
Background:
- Morgagni hernia is a rare congenital diaphragmatic hernia.
- Laparoscopic repair offers potential benefits over open surgery.
Purpose of the Study:
- To evaluate the outcomes of laparoscopic Morgagni hernia repair.
- To assess the safety and efficacy of leaving the hernia sac intact.
Main Methods:
- Retrospective review of patients undergoing laparoscopic Morgagni hernia repair (2016-2019).
- Analysis of patient demographics, clinical presentation, surgical technique, and follow-up data.
Main Results:
- All patients were male, with a mean age of 4.1 years.
- Common presentations included respiratory infections and vomiting; 38% had Down's Syndrome.
- No complications or recurrence were observed during a mean follow-up of 19.2 months after primary repair without hernia sac removal.
Conclusions:
- Minimally invasive repair of Morgagni hernia is efficient and safe, offering fast recovery and better cosmetic results.
- Leaving the hernia sac during laparoscopic repair appears to have no impact on early or late complications.
- This approach may prevent complications associated with unnecessary dissection.
Aim:
We aimed to present our laparoscopic treatment experience in Morgagni hernia repair.
Methods:
The patients who underwent laparoscopic surgery with diagnosis of Morgagni hernia between 2016 and 2019 were evaluated retrospectively.
Results:
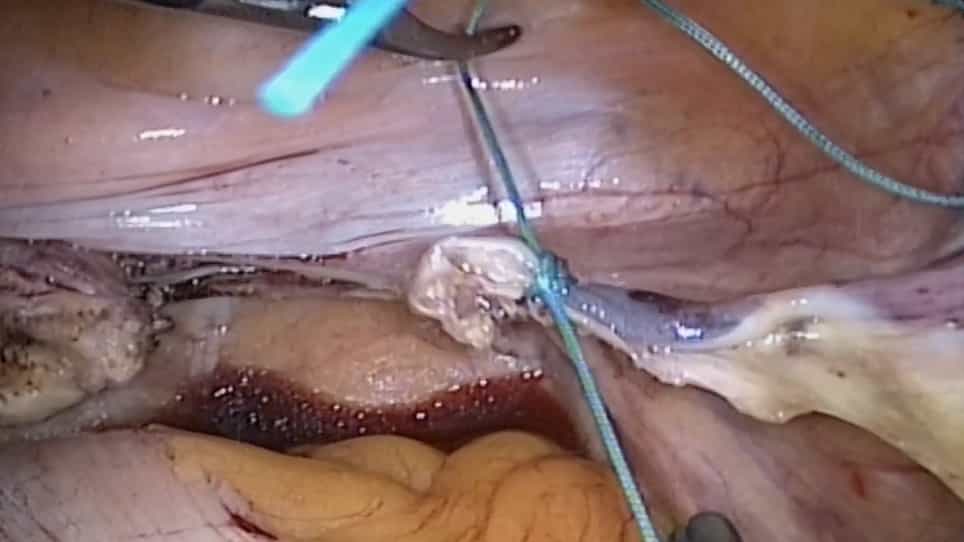
Their mean age at diagnosis was 4,1 ± 2,6 years (1 year-13 years). All patients were male. The presenting complaints were respiratory tract infection in 3 patients and vomiting in 3. Two patients were diagnosed incidentally. Associated Down's Syndrome was detected in 3 (38%) cases. The defect was left-sided in 7 (87.5%) patients and bilateral in 1 (12,5%). Omentum was herniated in 2 patients, colon and omentum were in 6 and colon, omentum and stomach were in one. All patients underwent primary repair extracorporeally by removing sutures from single incision, without removal of the hernia sac. There were no complications or recurrence in the mean 19,2 ± 15,8 months (6-42 months) follow-up period.
Conclusions:
Minimal invasive repair of Morgagni hernia is efficient and safe. It should be the first choice because of fast recovery and better cosmetic results. In this series, it was seen that leaving the hernia sac had no effect on early and late complications. Leaving the hernia sac may prevent potential complications due to unnecessary dissection.