Related Experiment Video
Updated: Dec 18, 2025
Patient Directed Recording of a Bipolar Three-Lead Electrocardiogram using a Smartwatch with ECG Function
Published on: December 11, 2019
The prevalence and correlates of T-wave inversion in lead III in non-obese men
Cihan Sengul1, Cayan Cakir1, Suleyman Barutcu1
1Department of Cardiology, University of Health Sciences, Van Education and Research Hospital, Van, Turkey.

Background:
T-wave inversion in lead III was linked to displacement of the base of the heart due to abdominal adipose tissue in early electrocardiography (ECG) trials. The observation of T-wave inversion in lead III in some of the pathological and physiological conditions other than obesity suggests the possibilities of different mechanisms. We aimed to investigate the prevalence and correlates of T-wave inversion in lead III in non-obese men.
Method:
A total of 1240 men underwent ECG, blood pressure measurement, hepatic ultrasonography, and biochemical tests from January 2019 to December 2019. We excluded 220 subjects due to predetermined criteria. The eligible 105 non-obese men with T-wave inversion in lead III and 915 non-obese men without T-wave inversion in lead III were compared with each other in terms of clinical, demographic and laboratory parameters.
Results:
The mean age was 27.9 years with a range of 20 to 46 years. The prevalence of T-wave inversion in lead III was 10.3%. Body mass index (BMI), blood urea nitrogen, creatinine, alanine aminotransferase, hematocrit, and the percentage of non-alcoholic fatty liver disease (NAFLD) were significantly higher in Group with T-wave inversion while alkaline phosphatase was significantly higher in Group without T-wave inversion. In multivariable analysis, NAFLD was the best independent correlate of inverted T-wave in lead III (β = 6.215, p < 0.0001). BMI (β = 1.448, p < 0.001) and hematocrit (β = 1.179, p = 0.021) were the other independent correlates of T-wave inversion in lead III.
Conclusion:
We demonstrated the association of T-wave inversion in lead III with NAFLD, BMI, and hematocrit in non-obese men.
More Related Videos
 18:11
A Research Method For Detecting Transient Myocardial Ischemia In Patients With Suspected Acute Coronary Syndrome Using Continuous ST-segment Analysis
Published on: December 28, 2012
 14:19
Primary Outcome Assessment in a Pig Model of Acute Myocardial Infarction
Published on: October 14, 2016
Related Concept Videos
 01:30
Acute Coronary Syndrome III: Diagnostic Studies
 01:29
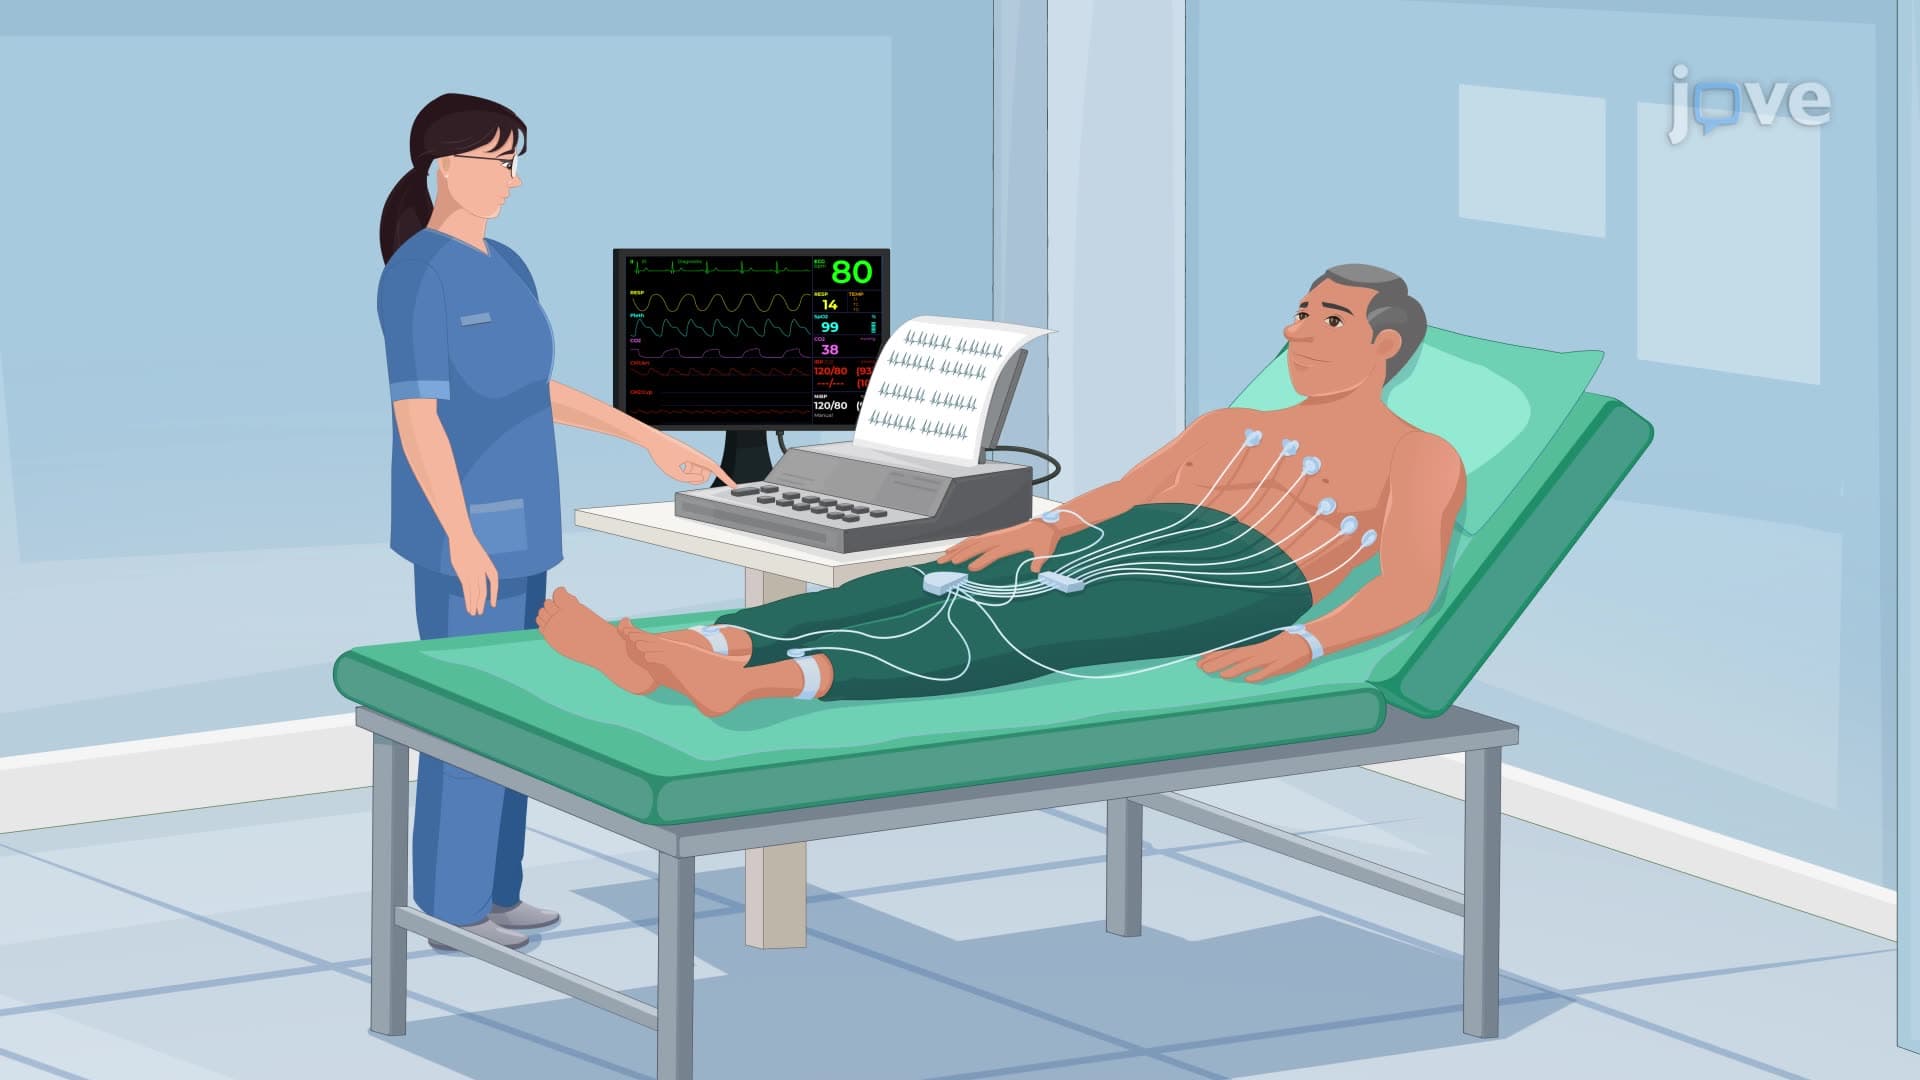
Electrocardiogram
Three major waveforms are present in a typical ECG recording: the P wave, the QRS complex, and...
 01:30
Coronary Artery Disease III: Clinical Manifestations
 01:25
Correlation between ECG and Cardiac Cycle
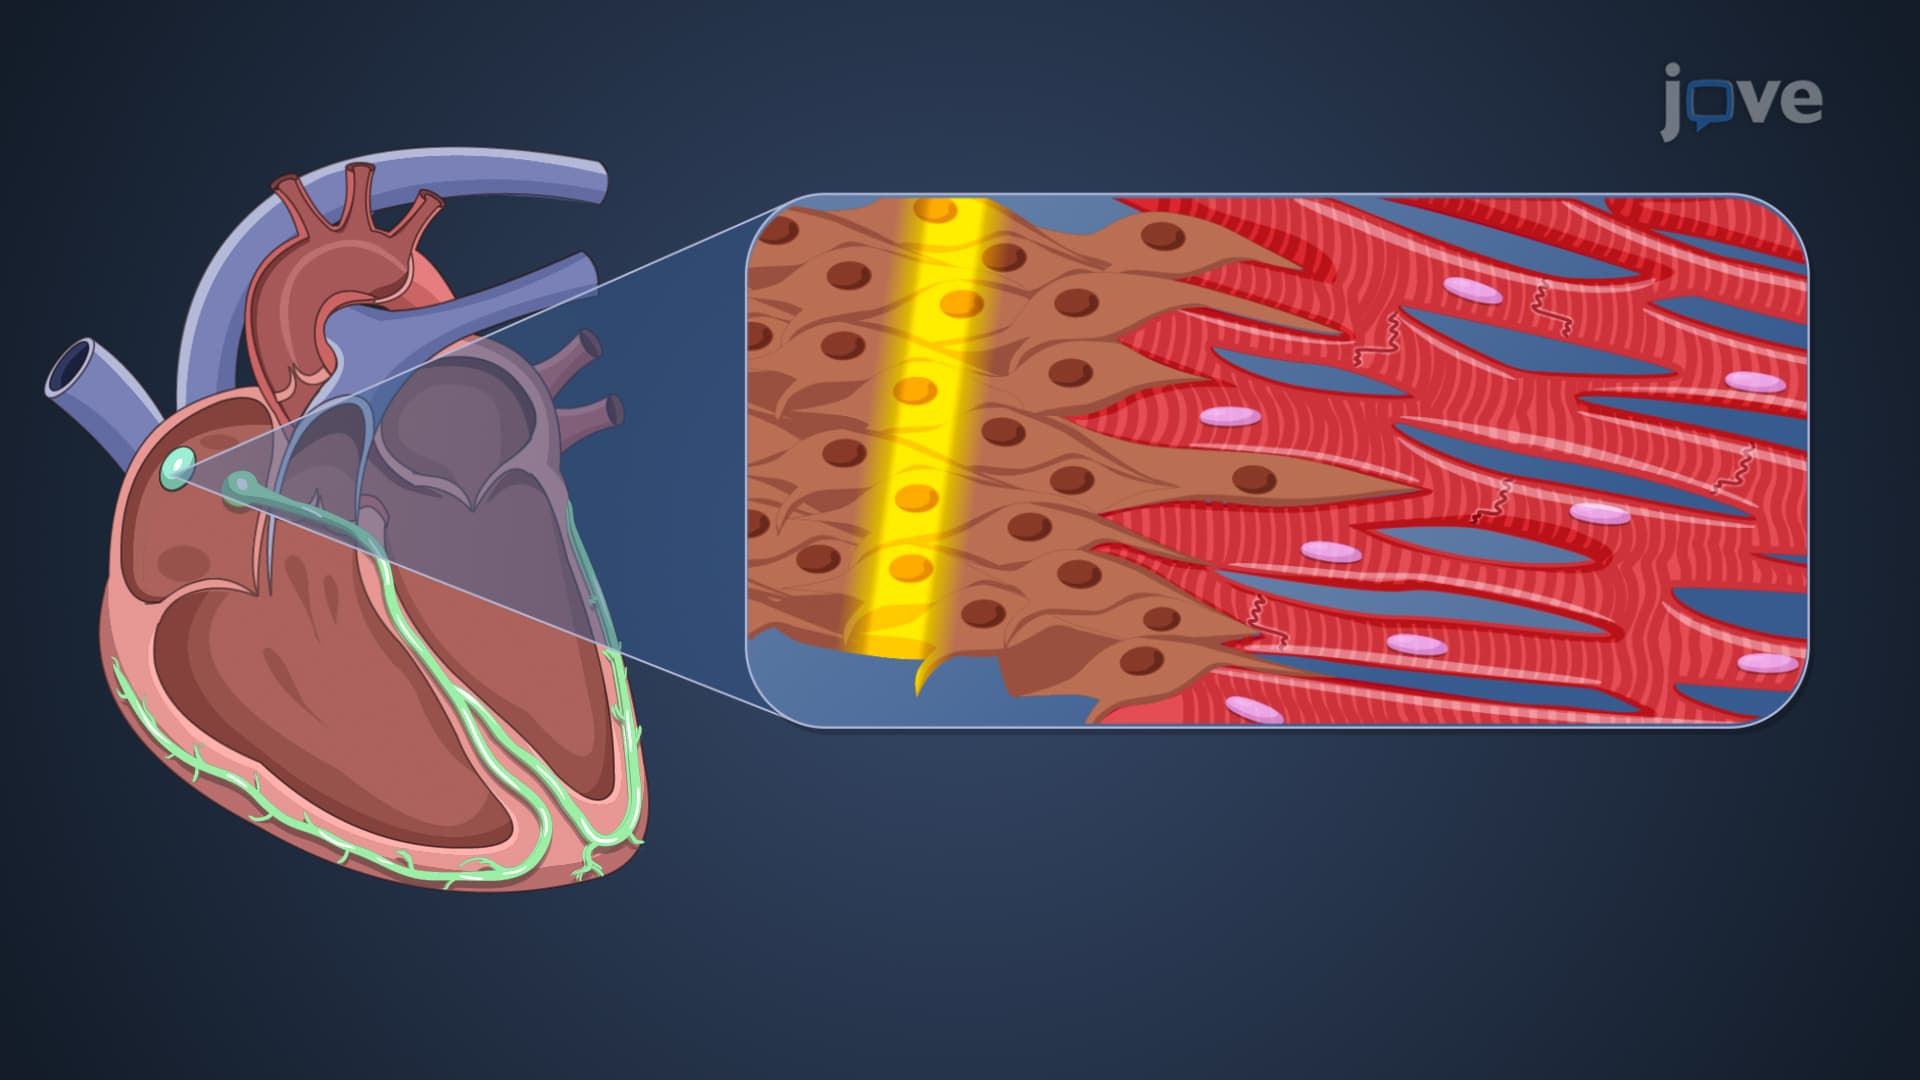
A cardiac action potential originates in the SA node and spreads throughout the atria and the AV node in approximately 0.03 seconds. This results in the P wave in an ECG and triggers atrial contraction. The action potential is then briefly slowed at the AV node, allowing the atria to contract and fill the ventricles with blood before...
 01:19
Electrophysiology of Normal Cardiac Rhythm
 01:29
Dysrhythmias III: Characteristics of Dysrhythmias