Related Experiment Video
Updated: Dec 15, 2025
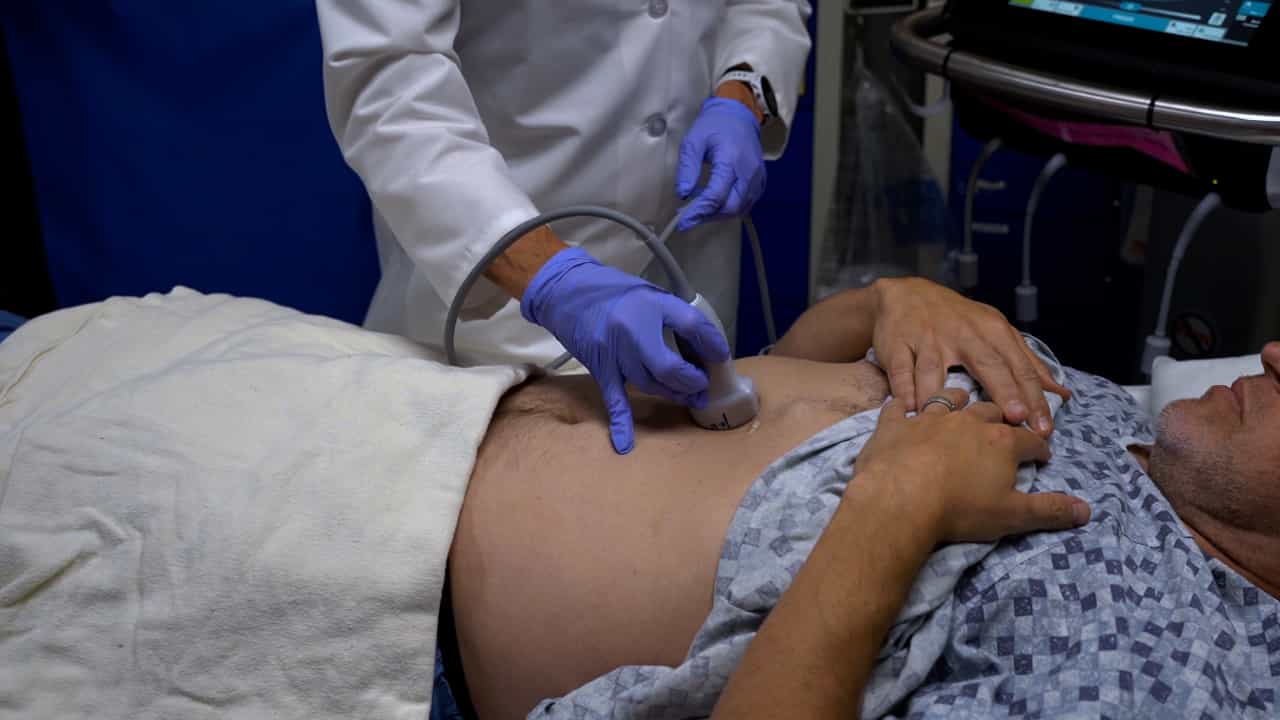

Author Spotlight: Point-of-Care Ultrasound for Gastric Content Assessment and Risk Stratification in Perioperative Care
Published on: September 22, 2023
Gastrin Staining in Inflamed Stomach Biopsies Labeled as "Antral" Rarely Detects Atrophic Gastritis
Andrew L J Dunn1, Michael G Drage1, Christa L Whitney-Miller1
1Department of Pathology and Laboratory Medicine, University of Rochester Medical Center, Rochester, NY.

Objectives:
Autoimmune metaplastic atrophic gastritis (AMAG) is an underrecognized entity, especially in its early stage. This study assessed whether the use of gastrin immunohistochemistry would increase sensitivity for diagnosing early AMAG.
Methods:
Three-hundred gastric biopsies were prospectively stained for gastrin by immunohistochemistry. Inclusion criteria included well-oriented gastric mucosa with mucus glands and minimal plasma cell infiltrate not suspected to represent pyloric metaplasia. Patient age, sex, designated location of biopsy, presence or absence of intestinal metaplasia, and clinical information were not criteria. Any case with absence of gastrin-positive endocrine cells reflexed to chromogranin immunohistochemistry. Maloriented biopsies or cases with current Helicobacter infection were excluded.
Results:
The 298-patient study cohort comprised 222 females (mean age, 47 years; range, 16-80 years) and 76 males (mean age, 49 years; range, 7-80 years). Biopsies were designated as "antral/antral nodules" (61%), and the rest were labeled "gastric/random stomach" (39%). Nine cases (3%) exhibited absence of gastrin-positive endocrine cells; one of those showed endocrine cell hyperplasia by chromogranin staining.
Conclusions:
Pathologists should be aware of the histologic features of early AMAG and meticulously analyze tissue regardless of specimen labeling. Gastrin immunostain is a supplemental diagnostic tool when encountering inflamed antral-appearing specimens.


Related Concept Videos
 01:27
Gastritis-I: Introduction and Types
Acute gastritis presents as a sudden inflammation triggered by various stressors to the stomach lining, such as exposure to corrosive agents, local irritants like aspirin and other NSAIDs, alcohol consumption, radiation therapy, physical trauma, severe burns, sepsis,...
 01:17
Gastritis-II: Pathophysiology
In acute gastritis, the gastric mucosa becomes swollen and red and undergoes superficial erosion. Superficial ulceration may lead to bleeding.
In chronic gastritis, persistent or repeated insults lead to chronic inflammatory changes and, eventually, thinning or atrophy of the gastric tissue.
Gastritis can stem from various causes, each...
 01:28
Peptic Ulcer Disease III: Clinical Manifestations and Diagnostic Studies
Few clinical manifestations differentiate gastric ulcers from duodenal ulcers. Distinctions in the location, timing, and pain relief are crucial for healthcare providers in differentiating between gastric and duodenal ulcers during clinical assessments.
 01:23
Gastritis III: Clinical Manifestations and Management
Clinical manifestations of acute gastritis
The patient with acute gastritis may have a rapid onset of symptoms, such as epigastric pain or discomfort, dyspepsia, anorexia, hiccups, or nausea and vomiting, which can last from a few hours to a few days. Erosive or hemorrhagic gastritis may cause bleeding, which may manifest as blood in vomit or as...
 01:22
Pathophysiology of Peptic Ulcer Disease: Injurious Factors
In the antrum region, G cells secrete the gastrin hormone that binds to gastrin-cholecystokinin-B (CCK2) receptors on parietal and enterochromaffin-like (ECL) cells in the fundic glands. Simultaneously, the vagus nerve releases acetylcholine, which binds...
 01:26
Stomach Histology