Related Experiment Video
Updated: Dec 13, 2025
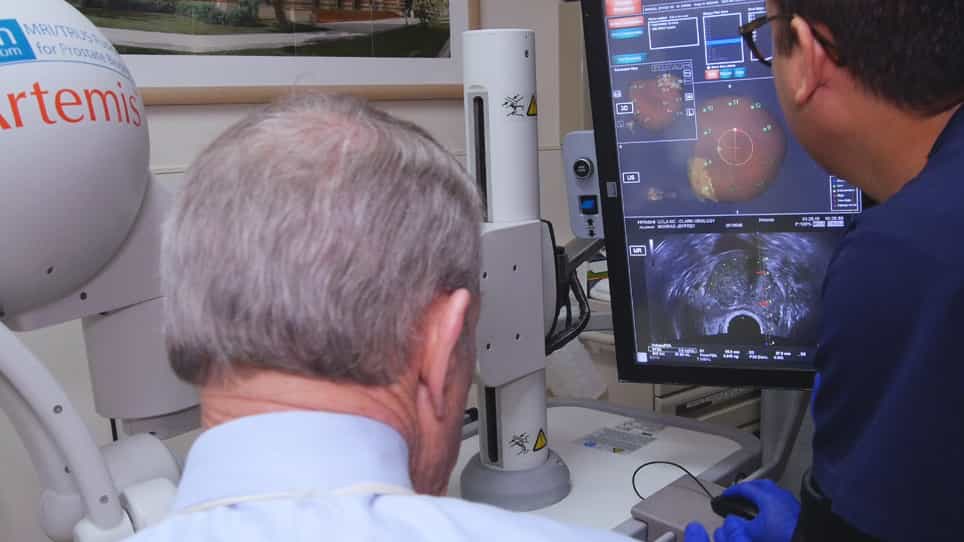

Use of MRI-ultrasound Fusion to Achieve Targeted Prostate Biopsy
Published on: April 9, 2019
Dosimetric evaluation of MRI-to-ultrasound automated image registration algorithms for prostate brachytherapy
Amani Shaaer1, Moti Paudel2, Melanie Davidson2
1Department of physics, Ryerson University, Toronto, Ontario, Canada; Biomedical Physics Department, King Faisal Specialist Hospital & Research Centre, Riyadh, Saudi Arabia.

Purpose:
Identifying dominant intraprostatic lesions (DILs) on transrectal ultrasound (TRUS) images during prostate high-dose-rate brachytherapy treatment planning remains a significant challenge. Multiparametric MRI (mpMRI) is the tool of choice for DIL identification; however, the geometry of the prostate on mpMRI and on the TRUS may differ significantly, requiring image registration. This study assesses the dosimetric impact attributed to differences in DIL contours generated using commonly available MRI to TRUS automated registration: rigid, semi-rigid, and deformable image registration, respectively.
Methods And Materials:
Ten patients, each with mpMRI and TRUS data sets, were included in this study. Five radiation oncologists with expertise in TRUS-based high-dose-rate brachytherapy were asked cognitively to transfer the DIL from the mpMRI images of each patient to the TRUS image. The contours were analyzed for concordance using simultaneous truth and performance level estimation (STAPLE) algorithm. The impact of DIL contour differences due to registration variability was evaluated by comparing the STAPLE-DIL dosimetry from the reference (STAPLE) plan with that from the evaluation plans (manual and automated registration) for each patient. The dosimetric impact of the automatic registration approach was also validated using a margin expansion that normalizes the volume of the autoregistered DILs to the volumes of the STAPLE-DILs. Dose metrics including D90, Dmean, V150, and V200 to the prostate and DIL were reported. For urethra and rectum, D10 and V80 were reported.
Results:
Significant differences in DIL coverage between reference and evaluation plans were found regardless of the algorithm methodology. No statistical difference was reported in STAPLE-DIL dosimetry when manual registration was used. A margin of 1.5 ± 0.8 mm, 1.1 ± 0.8 mm, and 2.5 ± 1.6 mm was required to be added for rigid, semi-rigid, and deformable registration, respectively, to mitigate the difference in STAPLE-DIL coverage between the evaluation and reference plans.
Conclusion:
The dosimetric impact of integrating an MRI-delineated DIL into a TRUS-based brachytherapy workflow has been validated in this study. The results show that rigid, semi-rigid, and deformable registration algorithms lead to a significant undercoverage of the DIL D90 and Dmean. A margin of at least 1.5 ± 0.8 mm, 1.1 ± 0.8 mm, and 2.5 ± 1.6 mm is required to be added to the rigid, semi-rigid, and deformable DIL registration to be suitable for DIL-boosting during prostate brachytherapy.
More Related Videos
 06:08
A Cognitive Fusion-guided Prostate Biopsy Using Multiparametric Magnetic Resonance Imaging and Transrectal Ultrasound
Published on: March 21, 2025
 07:57
Positron Emission Tomography-based Dose Painting Radiation Therapy in a Glioblastoma Rat Model using the Small Animal Radiation Research Platform
Published on: March 24, 2022
